📋 Executive Summary
Drug-induced nephrotoxicity represents one of the most common causes of acute kidney injury in clinical practice, accounting for 15-25% of all AKI cases. Understanding the unique characteristics of medication-induced kidney injury is essential for early detection, appropriate prevention, and optimal management.
Visual reference
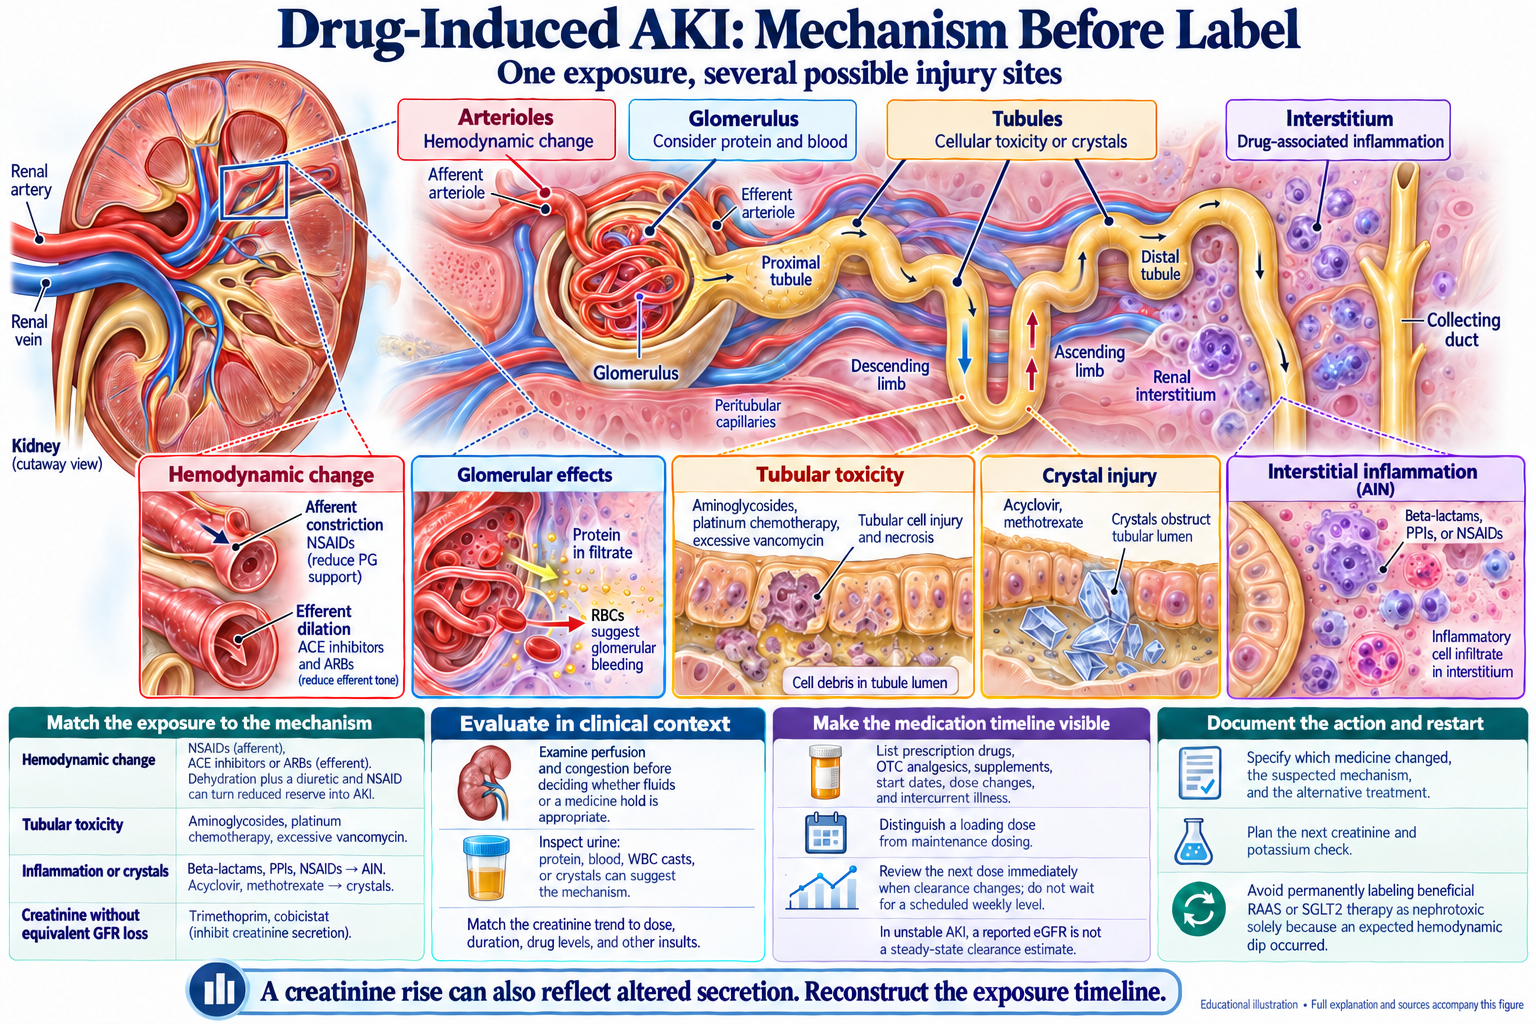
Browse the visual reference library · Download lesson Markdown
🔬 KDIGO 2026 draft Drug Classification Framework
Classifying drugs by kidney function markers and damage biomarkers (Figure 11)
| Damage Marker (−) | Damage Marker (+) | |
|---|---|---|
| Function Marker (−) |
Neither dysfunction nor damage Examples: Trimethoprim, Cimetidine → Benign SCr rise, no real injury |
Damage without dysfunction Examples: Aminoglycosides, Acyclovir, VEGF inhibitors → Tubular injury detectable by biomarkers before SCr rises |
| Function Marker (+) |
Dysfunction without damage Examples: ACEi, ARB → Hemodynamic effect on GFR, not structural injury |
Dysfunction AND damage Examples: NSAIDs → Both hemodynamic and structural injury |
This framework from KDIGO 2026 draft (Figure 11) classifies drugs by whether they affect kidney function markers (SCr, GFR) and/or damage biomarkers (NGAL, KIM-1, TIMP-2×IGFBP7). This distinction is clinically critical:
- Trimethoprim raises creatinine by blocking tubular secretion — NOT real injury (no damage marker elevation)
- ACEi/ARB reduce GFR hemodynamically — dysfunction without damage (appropriate in many patients)
- Aminoglycosides cause tubular damage detectable by biomarkers BEFORE creatinine rises — damage without dysfunction initially
- NSAIDs cause both hemodynamic GFR reduction AND structural damage
🏥 Nephrotoxin Stewardship
KDIGO 2026 draft Rec 4.2.1 (1C) Multimodal drug and nephrotoxin stewardship recommended
💊 Drug Management Strategies
- (a) Discontinue offending agent
- (b) Substitute less nephrotoxic alternative
- (c) Dose-reduce for dose-dependent effects
🖥️ Clinical Decision Support
- CDSS endorsed as effective tools (PP 4.3.2)
- Electronic alerts for nephrotoxin exposure
- Automated dose adjustment recommendations
👩⚕️ Pharmacist-Led Reconciliation
- Medication reconciliation for hospitalized patients with or at risk of AKI
- Surveillance for pharmacokinetic/pharmacodynamic drug-drug interactions (PP 4.2.3)
🛡️ Prevention Measures
- IV hydration for prevention of drug-induced crystalline nephropathies (PP 4.2.4)
- Therapeutic drug monitoring for narrow-margin drugs (vancomycin, aminoglycosides, calcineurin inhibitors)
💊 Drug Classes by Nephrotoxicity Risk & Mechanism
Overview of major drug classes with their mechanisms, onset timing, and injury patterns
| Drug Class | Primary Mechanism | Typical Onset (Days) | Pattern of Injury | Incidence Rate | Prevention Strategy |
|---|---|---|---|---|---|
| Aminoglycosides | Direct tubular toxicity | 7-10 | Acute tubular necrosis | 10-25% | Extended-interval dosing |
| Glycopeptides (Vancomycin) | Oxidative stress, inflammasome activation | 5-10 | Acute tubular necrosis | 5-35% | AUC-guided dosing |
| Beta-Lactams | Hypersensitivity reaction | 10-14 | Acute interstitial nephritis | 1-3% | Early recognition of AIN |
| Polymyxins | Membrane damage | 5-7 | Acute tubular necrosis | 20-60% | Optimal dosing strategies |
| Fluoroquinolones | Hypersensitivity reaction | 7-14 | Acute interstitial nephritis | <1% | Dose adjustment in CKD |
| Sulfonamides (Crystalluria) | Crystal formation | 1-3 | Crystal nephropathy | 1-5% | Adequate hydration, alkalinization |
| Tetracyclines | Direct tubular toxicity | 3-7 | Fanconi syndrome | <1% (modern agents) | Avoid expired formulations |
| Macrolides | Hypersensitivity, drug interactions | 7-14 | Acute interstitial nephritis | <1% | Monitor drug interactions |
| Amphotericin B | Membrane damage | 5-7 | Acute tubular necrosis | 30-80% | Lipid formulations, hydration |
| NSAIDs | Prostaglandin inhibition | Variable | Hemodynamic AKI, AIN | Variable by risk factors | Avoid in high-risk patients |
| PPIs | Immune-mediated hypersensitivity | Days to months | Acute interstitial nephritis | Variable | Appropriate indication, duration |
🧬 Aminoglycosides: Structure-Toxicity Relationship
Key Discovery: Nephrotoxicity directly correlates with positive charge and number of amino groups
| Aminoglycoside | Relative Nephrotoxicity | Number of Amino Groups | Positive Charges | Clinical Notes |
|---|---|---|---|---|
| Neomycin | Highest (5/5) | 6 | +6 | Topical use only due to toxicity |
| Gentamicin | High (4/5) | 5 | +5 | Most commonly used, high efficacy |
| Tobramycin | Moderate to High (3/5) | 5 | +5 | Preferred for Pseudomonas |
| Kanamycin | Moderate (3/5) | 4 | +4 | Limited use due to resistance |
| Amikacin | Moderate (2/5) | 4 | +4 | Reserved for resistant organisms |
| Netilmicin | Low to Moderate (2/5) | 3 | +3 | Less nephrotoxic alternative |
| Streptomycin | Lowest (1/5) | 2 | +2 | Primarily ototoxic, less nephrotoxic |
🔬 Mechanism of Charge-Related Toxicity
Higher positive charge → stronger binding to negatively charged phospholipids in proximal tubular cells
More charges → greater megalin-mediated endocytosis → higher intracellular accumulation
Highly charged molecules accumulate more in lysosomes → greater disruption of cellular function
Greater positive charge → stronger binding to mitochondrial ribosomes → more energy disruption
⚠️ High-Risk Nephrotoxic Drug Combinations
Synergistic nephrotoxicity from commonly used drug combinations
🔥 Vancomycin + Piperacillin-Tazobactam
NNH: 8-10 patients
Timeline: Risk highest in first 7 days
Alternative: Vancomycin + cefepime or meropenem
⚡ Vancomycin + Aminoglycosides
Risk Factors: Higher doses, extended duration
Enhanced uptake: Vancomycin increases aminoglycoside tubular uptake
Monitoring: Daily creatinine, enhanced surveillance
💀 Polymyxins + Vancomycin
Indication: Extensively drug-resistant organisms only
Additive effects: Multiple cellular injury pathways
Consider: Newer agents when available
🚨 "Triple Whammy" Effect
Mechanism: Disrupts all three major renal autoregulation mechanisms
Risk: Rate ratio 1.31 overall, 1.82 in first 30 days
Fatality rate: ~10% when AKI develops
🔬 Mechanisms of Drug-Induced Nephrotoxicity
🔥 Acute Tubular Necrosis (ATN)
🔵 Acute Interstitial Nephritis (AIN)
💎 Crystal Nephropathy
🛡️ Evidence-Based Prevention Strategies
🔍 Risk Assessment
- Baseline kidney function assessment
- Identify high-risk patients
- Review concurrent medications
- Assess volume status
- Consider alternative agents
💊 Optimized Dosing
- Vancomycin: AUC-guided dosing (33-45% ↓ risk)
- Aminoglycosides: Extended-interval dosing (30-50% ↓ risk)
- All drugs: Lowest effective dose, shortest duration
- Adjust for kidney function
- Therapeutic drug monitoring when available
🔬 Enhanced Monitoring
- Daily creatinine in high-risk patients
- Early biomarker detection (NGAL, KIM-1)
- Drug level monitoring
- Electrolyte surveillance
- Urine output tracking
💧 Supportive Care
- Maintain adequate hydration
- Avoid concurrent nephrotoxins
- Optimize hemodynamics
- Correct electrolyte abnormalities
- Consider nephroprotective strategies
⏰ Temporal Patterns of Drug-Induced Nephrotoxicity
Understanding onset timing is crucial for early recognition and intervention
Immediate Onset (Hours to 3 Days)
Drugs: Sulfonamide crystalluria, contrast agents, hemodynamic drugs (NSAIDs in volume-depleted patients)
Mechanism: Crystal formation, acute hemodynamic changes, direct tubular toxicity
Clinical Action: Immediate drug discontinuation, aggressive hydration, alkalinization for crystals
Early Onset (5-7 Days)
Drugs: Polymyxins, Amphotericin B, Vancomycin
Mechanism: Direct membrane damage, oxidative stress, early inflammatory responses
Clinical Action: Dose adjustment, enhance monitoring, consider alternative formulations
Classic Onset (7-10 Days)
Drugs: Aminoglycosides, most ATN-causing agents
Mechanism: Cumulative cellular damage, lysosomal disruption, mitochondrial dysfunction
Clinical Action: Extended-interval dosing, therapeutic drug monitoring, biomarker surveillance
Delayed Onset (10-14 Days)
Drugs: Beta-lactams, PPIs, Fluoroquinolones (AIN pattern)
Mechanism: Immune sensitization, T-cell mediated hypersensitivity
Clinical Action: High index of suspicion, corticosteroids for severe AIN, drug withdrawal
Very Delayed Onset (Weeks to Months)
Drugs: Chronic PPI use, chronic NSAID use, cumulative chemotherapy exposure
Mechanism: Chronic inflammation, repeated subclinical injury, progressive scarring
Clinical Action: Regular monitoring, deprescribing when appropriate, risk-benefit assessment
🎯 Essential Drug Nephrotoxicity Pearls
🧬 Structure-Function
- Aminoglycoside toxicity ∝ positive charge
- Higher charge = greater nephrotoxicity
- Mechanism: enhanced cellular uptake
- Clinical relevance: drug selection matters
⚡ Combination Toxicity
- Vanc + Pip-Tazo: 35-45% AKI risk
- Each additional nephrotoxin: +60% risk
- Synergistic, not just additive
- NNH for combinations: 8-10 patients
⏰ Temporal Patterns
- ATN: 5-10 days (delayed recognition)
- AIN: 10-14 days (immune-mediated)
- Crystals: Hours to days (immediate)
- Early recognition crucial for outcomes
🛡️ Prevention Wins
- AUC-guided vancomycin: -33-45% risk
- Extended-interval aminoglycosides: -30-50%
- Proper hydration prevents crystals
- Risk assessment before prescription
🔬 Mechanisms Matter
- ATN: Direct cellular toxicity
- AIN: T-cell mediated hypersensitivity
- Crystals: Physical obstruction
- Different mechanisms = different treatments
📊 Evidence-Based Care
- Strong RCT evidence for dosing strategies
- Biomarkers improve early detection
- Protocol-driven monitoring reduces AKI
- Electronic alerts help prevention