Visual summary
A complete medication history and a mechanism-based timeline often reveal a reversible contributor to AKI.
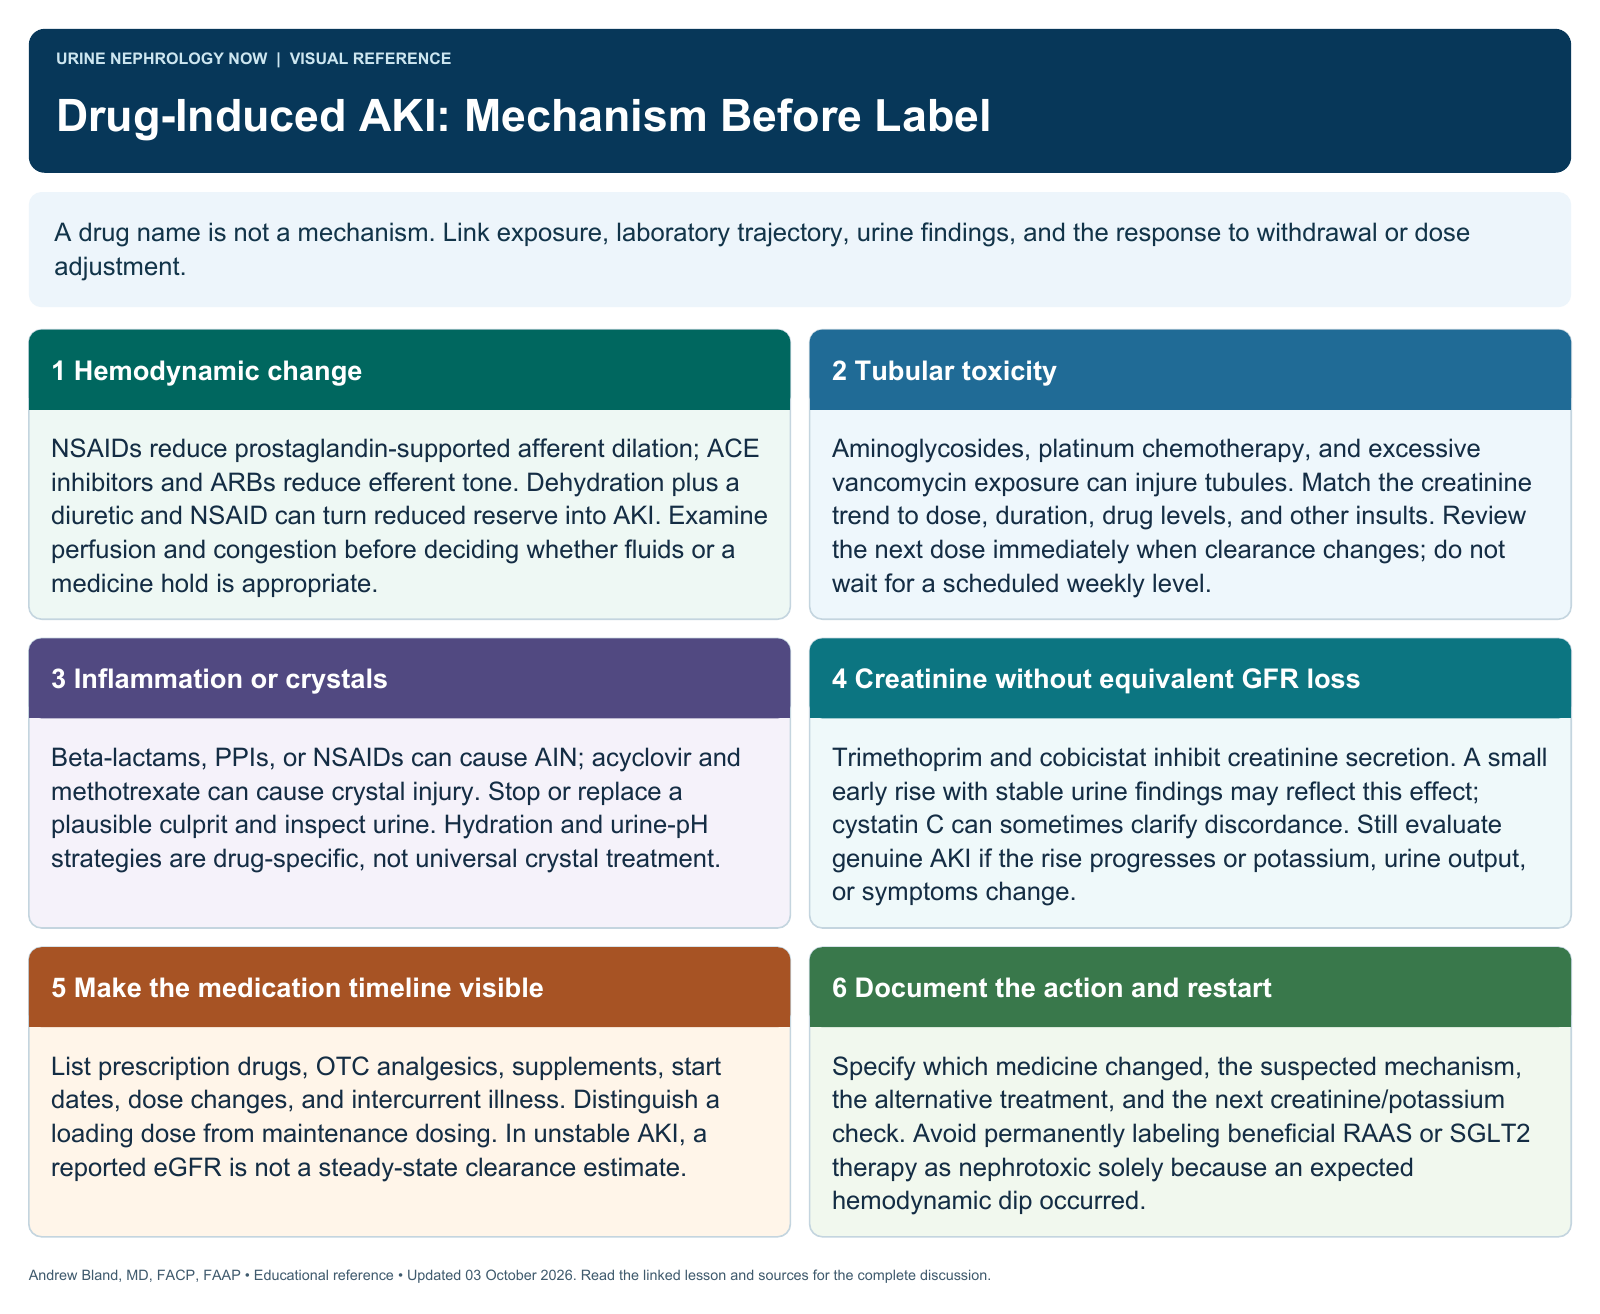
Text version
Several injury pathways
Medications can alter glomerular hemodynamics, directly injure tubules, trigger interstitial inflammation, or precipitate crystals. Some raise creatinine through reduced tubular secretion without reducing filtration; others cause genuine injury.
Recognize the exposure pattern
Look for a new prescription, dose increase, prolonged treatment, interacting drugs, or a dehydrating illness. Include over-the-counter analgesics, acid suppressants, supplements, and recent contrast exposure in the history.
Build a timeline
Compare drug start dates with creatinine, urine output, electrolyte changes, and symptoms. Examine urine and assess volume status. Consider drug concentrations when a validated monitoring strategy exists for that agent.
Reduce preventable harm
Use the appropriate indication, renal dosing, shortest effective course, and laboratory follow-up. Coordinate with pharmacy when kidney function changes rapidly or the patient receives kidney replacement therapy.
Respond to suspected toxicity
Stop or substitute the likely culprit when feasible, support circulation, and treat complications. Infection may still require effective antimicrobial coverage. Document the suspected mechanism and plan for recovery monitoring.
Avoid class-wide assumptions
Risk varies with dose, duration, patient physiology, and coexposures. Association does not prove causation. A creatinine rise during protective therapy needs clinical interpretation before a useful medication is permanently abandoned.
Continue learning
This graphic summarizes a topic. The full educational pages provide the broader discussion and references.