Pre-Case Assessment: Test Your Baseline Knowledge
At what eGFR threshold should anemia evaluation be initiated in patients with CKD?
KDIGO Guideline: Anemia evaluation should be initiated when eGFR falls below sixty milliliters per minute per 1.73 square meters (CKD G3-G5). Anemia becomes increasingly common as kidney function declines. Evaluation includes CBC, iron studies (ferritin, transferrin saturation), vitamin B12, and folate levels.
📚 Reference: CKD Anemia Management
How should the adult hemoglobin target be selected during ESA treatment for CKD anemia?
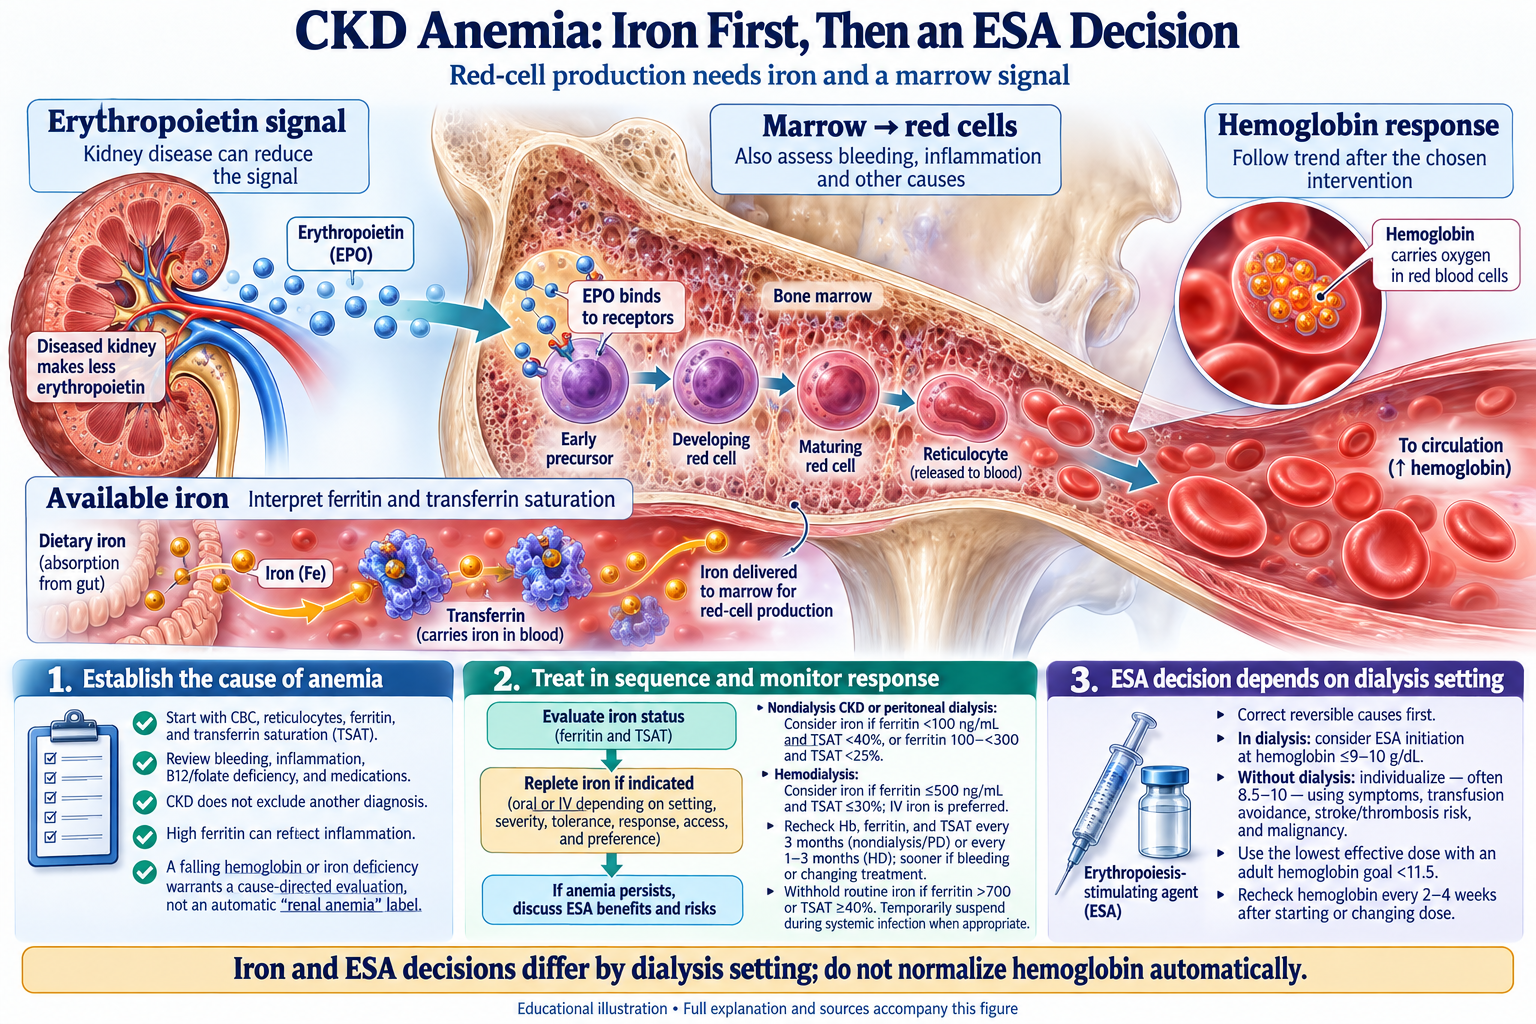
Evidence Base: KDIGO 2026 recommends an adult ESA target below 11.5 g/dL. Choose the target and lowest effective dose around symptoms, transfusion avoidance, cardiovascular/thrombotic risk, and the applicable product label. Initiation in nondialysis CKD is individualized; a single universal hemoglobin trigger or fixed target range is not appropriate.
How should ferritin and TSAT be used when assessing iron availability in CKD anemia?
Iron Parameters: Ferritin and TSAT are interpreted together. Ferritin may rise with inflammation while iron remains poorly available for erythropoiesis. Initiation and withholding criteria guide an iron-treatment decision; they are not universal iron targets or proof that a patient has enough usable iron. Review hemoglobin response, losses, prior iron, and dialysis status.
Case Presentation
Patient: Mrs. Dorothy Williams, 72-year-old woman
Chief Complaint: Increasing fatigue and shortness of breath with exertion
History: Progressive fatigue over three months, now unable to climb stairs without resting. Previously walked one mile daily, now limited to one block. Denies chest pain, palpitations, or syncope. Some mild dyspnea with exertion. No bleeding noted. Good appetite but reports decreased exercise tolerance affecting quality of life.
Past Medical History: CKD G4 (eGFR 22 mL/min/1.73m²) secondary to hypertensive nephrosclerosis, hypertension, coronary artery disease, osteoarthritis
Medications: Lisinopril 20mg daily, amlodipine 10mg daily, atorvastatin 40mg daily, aspirin 81mg daily, furosemide 40mg daily
Social History: Lives independently, retired teacher, no smoking or alcohol
📊 Clinical Assessment Questions
Laboratory results show hemoglobin 8.5 g/dL, MCV 88 fL (normocytic), ferritin 45 ng/mL, TSAT 15%, creatinine 3.2 mg/dL. What is the most likely cause of anemia?
Diagnosis: This patient has anemia of CKD (hemoglobin 8.5 g/dL with eGFR 22) complicated by absolute iron deficiency (ferritin 45 ng/mL, TSAT 15%). CKD G4-G5 causes anemia due to decreased erythropoietin production. Iron deficiency (ferritin less than 100 ng/mL, TSAT less than 20%) must be corrected before considering ESA therapy. The normocytic anemia pattern is typical for CKD. While GI bleeding should be excluded given aspirin use and low iron stores, the clinical picture is most consistent with CKD anemia plus iron deficiency.
What is the most appropriate initial management for this patient's anemia?
Management Principle: Iron deficiency must be corrected before initiating ESA therapy. ESAs require adequate iron availability to stimulate effective erythropoiesis. With ferritin 45 ng/mL and TSAT 15%, this patient has absolute iron deficiency. Oral iron (ferrous sulfate 325mg three times daily) or IV iron (iron sucrose, ferumoxytol, or iron dextran) can be used. For nondialysis CKD, choose oral or IV iron according to the degree of anemia/iron deficiency, desired speed, tolerance, effectiveness, access, cost, and preference; eGFR below 30 alone does not mandate IV therapy. If an adequate oral trial is ineffective after 1–3 months or is not tolerated, switching to IV iron is reasonable. Reassess iron availability and other reversible contributors before ESA decisions. Transfusion reserved for symptomatic severe anemia or cardiovascular instability. Dietary iron alone is insufficient.
After iron repletion (ferritin now 250 ng/mL, TSAT 28%), hemoglobin remains 8.8 g/dL. The patient continues to report fatigue limiting activities. What is the next step?
ESA Initiation: Persistent symptomatic anemia after iron treatment supports an individualized ESA discussion in this nondialysis patient. Reassess other reversible causes and cardiovascular, thrombotic, and malignancy risks; choose the agent and dose using its current label. Keep the adult target below 11.5 g/dL and monitor hemoglobin every 2–4 weeks after initiation or dose changes. Neither ferritin/TSAT nor hemoglobin alone settles the treatment decision.
After starting darbepoetin 60 mcg every two weeks, hemoglobin increases to 12.8 g/dL over three months. What adjustment should be made?
ESA Dose Adjustment: Hemoglobin 12.8 g/dL is above the recommended adult ESA target. Reduce or interrupt treatment according to the specific product label, dialysis status, and rate of rise, with repeat hemoglobin monitoring. Reassess any restart and use the lowest effective dose; do not automatically resume at 11–11.5 g/dL or pursue a normal hemoglobin.
A patient with nondialysis CKD on ESA therapy has ferritin 600 ng/mL, TSAT 18%, and a suboptimal hemoglobin response. What is the best interpretation?
Iron-restricted erythropoiesis: Low TSAT with elevated ferritin can reflect inflammation and limited iron availability, but it does not automatically mandate IV iron. For nondialysis CKD/PD, KDIGO 2026 suggests initiation when ferritin is <100 ng/mL with TSAT <40%, or ferritin 100–<300 with TSAT <25%. Ferritin 600/TSAT 18% is outside these usual initiation criteria. Assess inflammation, blood loss, prior iron, and other causes of ESA hyporesponsiveness; an individualized trial may be considered in selected refractory cases with specialist oversight. Routine iron is generally withheld when ferritin >700 or TSAT ≥40%. KDIGO 2026 anemia guideline.
Which of the following is an absolute contraindication to ESA therapy?
Contraindications: Active malignancy is an absolute contraindication to ESA therapy because ESAs may promote tumor growth and reduce survival in cancer patients. ESAs should not be used in patients receiving chemotherapy for curative intent. Relative contraindications include uncontrolled hypertension (must control BP before starting ESA), history of stroke (increased risk with ESA), and prior thrombotic events. Hypertension and diabetes are not contraindications if well-controlled. Monitor blood pressure closely after ESA initiation as it may worsen hypertension.
What is the most appropriate hemoglobin threshold for transfusion in a stable CKD patient without active bleeding or cardiovascular symptoms?
Transfusion Thresholds: For stable patients without cardiovascular disease or active bleeding, restrictive transfusion strategy with threshold of seven grams per deciliter is recommended. For patients with cardiovascular disease or symptoms (chest pain, dyspnea, tachycardia), threshold may be eight grams per deciliter. Transfusions should be used judiciously in CKD due to risks including iron overload, alloimmunization (problematic for future transplant candidates), infection, and volume overload. ESA therapy and iron supplementation are preferred for chronic anemia management.
A patient on ESA therapy has been stable but now requires increasing ESA doses to maintain target hemoglobin. Which cause of ESA hyporesponsiveness should be evaluated first?
ESA Hyporesponsiveness: Iron deficiency is the most common cause of ESA hyporesponsiveness. Check ferritin and TSAT first. Other common causes include: infection or inflammation (check CRP), blood loss (occult GI bleeding, menstruation), vitamin B12 or folate deficiency, hyperparathyroidism (check PTH), and inadequate dialysis (if on dialysis). Less common causes include pure red cell aplasia (very rare, presents with severe anemia and absent reticulocytes), hemolysis, bone marrow disorders, or aluminum toxicity (rare now). Systematic evaluation of common causes should precede investigation of rare etiologies.
How should the route of iron administration be selected in nondialysis CKD with eGFR below 30 mL/min/1.73 m²?
Route selection: KDIGO 2026 permits oral or IV iron for nondialysis CKD. IV iron may provide more rapid repletion or help after poor tolerance or inadequate response to an oral trial; it also requires infusion access and has formulation-specific risks. Review the degree of anemia/deficiency, prior response, preferences, and cost. If oral iron has insufficient effect after 1–3 months or is poorly tolerated, switching to IV is reasonable. The dialysis-specific preference for IV iron should not be converted into a blanket eGFR <30 rule.
Which cardiovascular risk is MOST associated with targeting hemoglobin levels above 13 g/dL with ESA therapy?
Evidence from Clinical Trials: Higher hemoglobin targets in ESA trials increased cardiovascular or thrombotic harms. Use the lowest effective dose and an individualized adult target below 11.5 g/dL; applicable product labeling may require a lower ceiling. Reassess the indication and risk balance instead of correcting hemoglobin to the normal range.
For a patient with anemia and CKD G5 on hemodialysis, which approach follows KDIGO 2026 iron guidance?
Dialysis Iron Targets: In anemic patients receiving hemodialysis, KDIGO suggests iron initiation when ferritin is ≤500 ng/mL and TSAT is ≤30%, generally using IV iron. Withhold routine iron when ferritin exceeds 700 ng/mL or TSAT reaches 40%; consider suspension during systemic infection. These are treatment decision thresholds, not required ferritin/TSAT targets. Use serial values, hemoglobin response, blood loss, and clinical context.
Which medication can worsen anemia in CKD patients and should be avoided when possible?
PPI Effect on Anemia: Proton pump inhibitors reduce iron absorption by decreasing gastric acid needed to convert ferric iron to absorbable ferrous form. Long-term PPI use can contribute to iron deficiency, especially in CKD patients who already have impaired iron absorption. If PPIs are necessary, consider using lowest effective dose and monitoring iron parameters more closely. May need IV iron if oral iron ineffective. ACE inhibitors can cause mild hemoglobin reduction but should not be discontinued as renal benefits outweigh this effect. Calcium channel blockers and statins do not significantly affect hemoglobin.
📝 Case Summary & Clinical Pearls
🔑 Key Clinical Pearls:
Iron First, Then ESA: Address iron deficiency and other reversible causes before an ESA decision. Use dialysis-specific initiation criteria, the hemoglobin response, and the clinical context rather than a fixed ferritin target for everyone.
Individualize the ESA Target: Keep the adult target below 11.5 g/dL, follow the product label, and use the lowest effective dose. Reassess symptoms, transfusion needs, and cardiovascular/thrombotic risk.
Watch for Functional Iron Deficiency: High ferritin with low TSAT may reflect iron-restricted erythropoiesis. It does not automatically require IV iron; assess inflammation, prior iron, ongoing losses, and the cause of an inadequate ESA response.
Select the Iron Route: In nondialysis CKD, choose oral or IV iron using severity, desired speed, tolerance, response, access, and preference. An eGFR below 30 alone does not determine the route.
Transfuse Judiciously: Reserve transfusions for hemoglobin less than seven grams per deciliter in stable patients. ESA and iron are preferred for chronic management.