Pre-Case Assessment: Test Your Baseline Knowledge
What is the KDIGO recommended target range for serum phosphorus in patients with CKD G3-G5?
KDIGO Guidance: Target phosphorus toward normal range (2.5-4.5 mg/dL) for CKD G3-G5. Avoid overly aggressive phosphorus lowering which may cause hypophosphatemia. Focus on preventing hyperphosphatemia through dietary restriction and phosphate binders when needed.
📚 Reference: CKD-MBD Management
At what eGFR threshold should PTH monitoring begin in CKD patients?
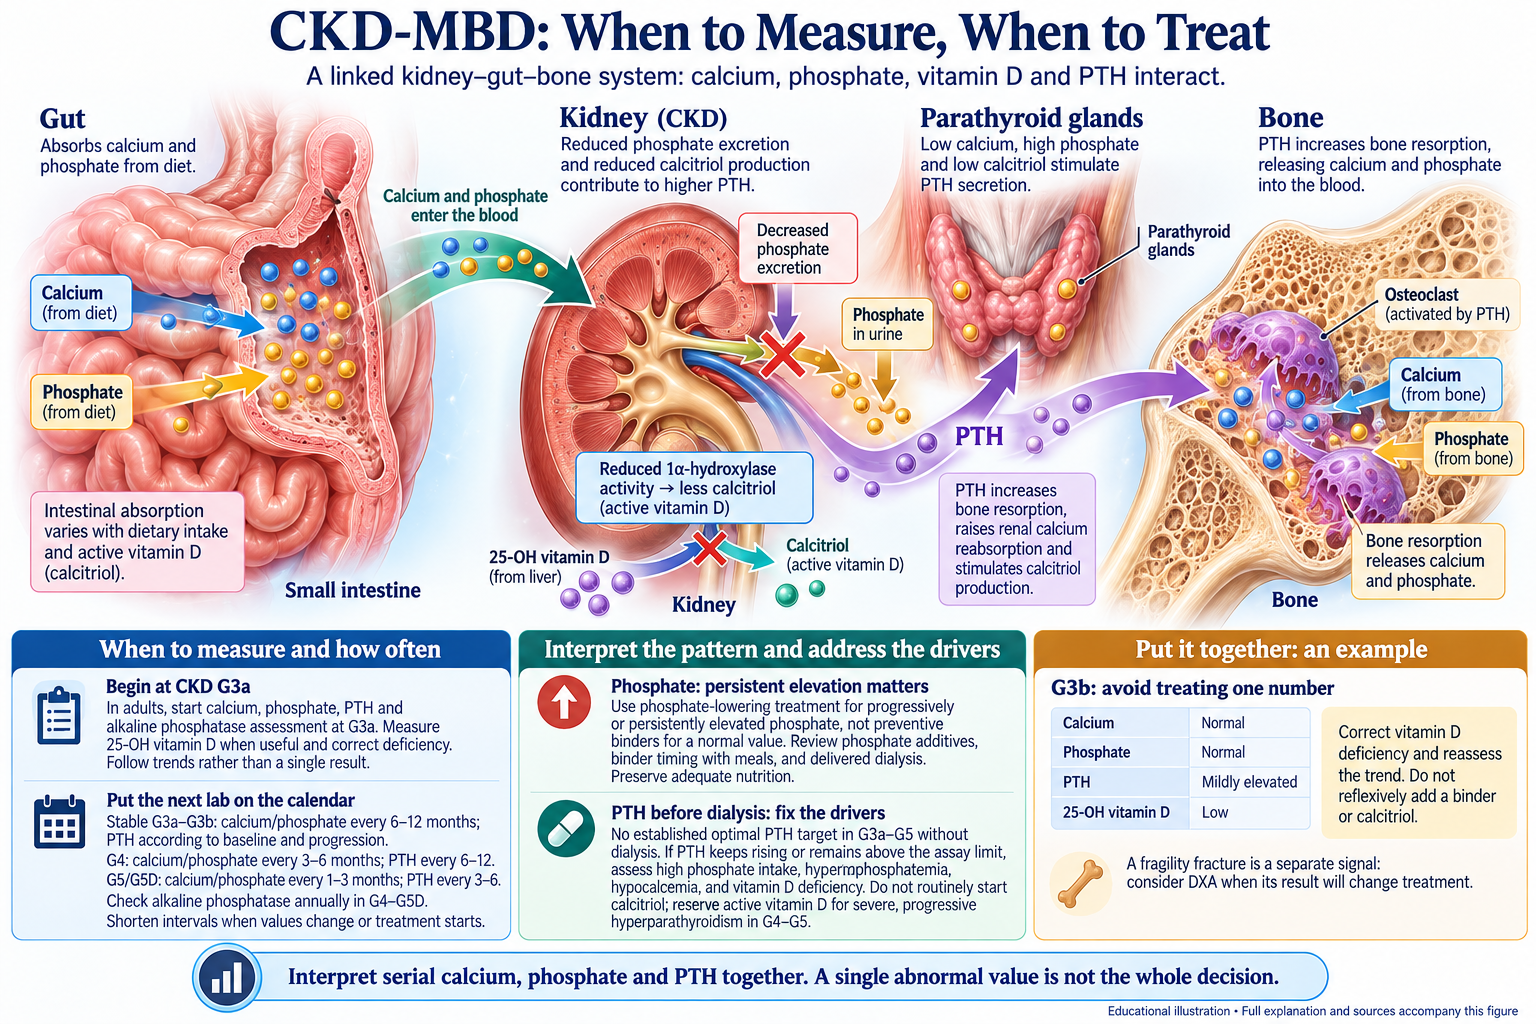
Monitoring Guidelines: KDIGO recommends beginning monitoring of calcium, phosphate, PTH, and alkaline phosphatase in CKD G3a (eGFR below 60 mL/min/1.73 m² in a patient with established CKD). Monitoring frequency depends on abnormalities and CKD progression. Measurement of 25-OH vitamin D may be appropriate. KDIGO 2017 CKD-MBD, recommendation 3.1.1.
Which calcium-based phosphate binder should be avoided in patients with hypercalcemia or vascular calcification?
Calcium-Based Binder Concerns: Calcium carbonate and calcium acetate should be avoided or used cautiously in patients with hypercalcemia, vascular calcification, or calcium-phosphate product greater than 55. Non-calcium-based binders (sevelamer, lanthanum, ferric citrate) are preferred in these situations to avoid increasing calcium burden.
Case Presentation
Patient: Mr. David Thompson, 58-year-old man
Chief Complaint: Routine CKD follow-up
History: Patient with CKD G4 (eGFR 25 mL/min/1.73m²) secondary to diabetic nephropathy. Recent labs show elevated phosphorus and PTH. Denies bone pain but has noted some muscle weakness. Compliant with medications and low-phosphate diet counseling from dietitian.
Past Medical History: CKD G4, type 2 diabetes, hypertension, coronary artery disease
Medications: Lisinopril 40mg daily, empagliflozin 10mg daily, insulin glargine 30 units nightly, atorvastatin 80mg daily
Labs: Calcium 9.8 mg/dL, Phosphorus 5.8 mg/dL, PTH 185 pg/mL, 25-OH Vit D 18 ng/mL, Alkaline phosphatase 145 U/L
📊 Clinical Assessment Questions
The combination of elevated phosphorus (5.8 mg/dL), elevated PTH (185 pg/mL), and low 25-OH vitamin D (18 ng/mL) indicates:
CKD-MBD Pathophysiology: This is classic secondary hyperparathyroidism from CKD. As kidney function declines, phosphate excretion decreases (causing hyperphosphatemia), 1,25-dihydroxyvitamin D production decreases (despite low 25-OH vitamin D), and FGF-23 rises. These changes stimulate PTH secretion. The parathyroid glands hypertrophy in response to chronically elevated PTH. Primary hyperparathyroidism would show hypercalcemia. Tertiary hyperparathyroidism refers to autonomous PTH secretion after prolonged secondary hyperparathyroidism, typically in long-term dialysis patients.
What is the most appropriate initial step in managing this patient's CKD-MBD?
Step-wise management: Review persistent phosphate elevation, dietary phosphate sources, calcium, and nutritional vitamin D deficiency. Use phosphate-lowering treatment for persistent/progressive elevation and restrict calcium-based binder exposure. Reassess PTH over time after addressing modifiable factors. In nondialysis G4-G5, active vitamin D is reserved for severe progressive hyperparathyroidism rather than any persistent elevation. Severe disease refractory to medical treatment can warrant surgical assessment. KDIGO 2017.
Which phosphate binder would be most appropriate for this patient with normal calcium (9.8 mg/dL)?
Phosphate Binder Selection: With normal calcium and mild-moderate hyperphosphatemia, calcium carbonate 500-1000mg with meals is reasonable and cost-effective. Total elemental calcium intake (diet plus binders) should not exceed 2000mg daily to avoid hypercalcemia and vascular calcification. If calcium rises or vascular calcification is present, switch to non-calcium-based binders like sevelamer carbonate (Renvela) 800mg three times daily with meals, lanthanum carbonate, or ferric citrate (which also treats iron deficiency). Aluminum hydroxide is effective but causes aluminum toxicity with chronic use and should be avoided. The phosphorus of 5.8 mg/dL requires treatment.
The patient's 25-OH vitamin D is 18 ng/mL. What is the appropriate vitamin D repletion strategy?
Vitamin D Repletion: 25-OH vitamin D should be maintained above thirty nanograms per milliliter. For levels below thirty, replete with ergocalciferol (D2) or cholecalciferol (D3) 50,000 IU weekly for 8-12 weeks, then maintenance 1000-2000 IU daily. This addresses nutritional vitamin D deficiency. Do not confuse with active vitamin D (calcitriol, paricalcitol, doxercalciferol) which is used specifically for PTH suppression after nutritional vitamin D is replete. Check 25-OH vitamin D level after repletion course. Many CKD patients have vitamin D deficiency due to dietary restrictions, limited sun exposure, and impaired skin synthesis.
After three months of phosphate binder and vitamin D repletion, labs show: Ca 10.2 mg/dL, Phos 4.5 mg/dL, PTH 220 pg/mL. What is the next step?
Active vitamin D decision: A PTH of 220 pg/mL with calcium 10.2 and phosphate 4.5 does not establish severe progressive hyperparathyroidism or mandate calcitriol. Recheck the assay trend, calcium exposure, phosphate intake, vitamin D status, and CKD trajectory. KDIGO advises against routine calcitriol/vitamin D analogues in nondialysis G3a-G5, reserving them for selected G4-G5 patients with severe progressive hyperparathyroidism after modifiable factors are addressed. Monitor calcium and phosphate closely if treatment is chosen; cinacalcet is not a routine nondialysis substitute. KDIGO 2017.
What dietary phosphorus intake should be recommended for CKD G4-G5 patients?
Dietary Phosphorus Management: Recommend 800-1000 mg phosphorus per day for CKD G4-G5. This typically requires limiting dairy products, processed foods with phosphate additives, dark colas, nuts, and beans. Inorganic phosphate additives in processed foods are nearly one hundred percent absorbed compared to organic phosphate in natural foods (forty to sixty percent absorbed). Renal dietitian involvement is essential for patient education and meal planning. Excessive restriction (less than 800 mg) may lead to malnutrition. Phosphate binders should complement, not replace, dietary restriction.
What is the calcium-phosphate product for a patient with calcium 10.5 mg/dL and phosphorus 5.5 mg/dL?
Calculation: Calcium-phosphate product = Ca × Phos = 10.5 × 5.5 = 57.8 mg²/dL². Values greater than 55 mg²/dL² increase risk of metastatic calcification in soft tissues including blood vessels, heart valves, and joints. This contributes to vascular calcification, cardiovascular disease, and calciphylaxis risk. When Ca-P product is elevated, prioritize lowering phosphorus with binders and dietary restriction. Avoid calcium-based binders if calcium is elevated. Monitor for symptoms of soft tissue calcification including joint pain and skin lesions.
Which medication is a calcimimetic that reduces PTH by increasing calcium-sensing receptor sensitivity?
Calcimimetic Agents: Cinacalcet (Sensipar) and etelcalcetide (Parsabiv) are calcimimetics that increase sensitivity of calcium-sensing receptors on parathyroid glands, reducing PTH secretion without increasing calcium or phosphorus. Reserved for severe secondary hyperparathyroidism (PTH greater than 600-800 pg/mL) unresponsive to phosphate binders and active vitamin D, or when active vitamin D causes hypercalcemia. Cinacalcet is oral, starting dose 30mg daily, can titrate to 180mg daily. Etelcalcetide is IV, given during dialysis. Common side effects include nausea and hypocalcemia. More expensive than traditional therapies. Can avoid or delay parathyroidectomy in many patients.
What is the primary complication of untreated secondary hyperparathyroidism in CKD?
CKD-MBD Complications: Untreated secondary hyperparathyroidism leads to renal osteodystrophy (abnormal bone turnover including osteitis fibrosa cystica with high turnover bone disease), increased fracture risk, bone pain, skeletal deformities, vascular calcification (contributing to cardiovascular disease), soft tissue calcification, and calciphylaxis (life-threatening condition with skin necrosis). The goal of CKD-MBD management is to prevent these complications while avoiding over-suppression which can cause adynamic bone disease (low bone turnover). Fracture risk is two to four times higher in CKD patients than age-matched controls.
When should parathyroidectomy be considered in CKD patients?
Parathyroidectomy Indications: Consider surgical parathyroidectomy for severe refractory hyperparathyroidism (PTH persistently greater than 800-1000 pg/mL) despite maximal medical therapy, calciphylaxis, progressive vascular or soft tissue calcification, refractory bone disease with fractures or severe bone pain, or intractable pruritus from hyperparathyroidism. Usually reserved for long-term dialysis patients who have developed tertiary hyperparathyroidism (autonomous PTH secretion). Surgical options include subtotal parathyroidectomy or total parathyroidectomy with autotransplantation. Post-operative risks include hungry bone syndrome (severe hypocalcemia and hypophosphatemia as bone rapidly takes up minerals) requiring aggressive calcium and calcitriol supplementation.
Which non-calcium-based phosphate binder also treats iron deficiency anemia?
Dual Benefit of Ferric Citrate: Ferric citrate (Auryxia) binds dietary phosphorus in the GI tract while also providing iron supplementation, addressing two common CKD complications simultaneously. Dose is 210-420mg three times daily with meals. Particularly useful in patients with both hyperphosphatemia and iron deficiency anemia. Side effects include GI upset and dark stools. More expensive than other binders but may reduce need for separate iron supplementation. Sevelamer and lanthanum do not provide iron. Monitor ferritin to avoid iron overload.
What is the target PTH range for patients with CKD G3-G5 not on dialysis?
PTH interpretation per KDIGO 2017: The optimal PTH level is unknown in nondialysis CKD G3a-G5. Progressively rising or persistently high PTH prompts evaluation of phosphate intake, hyperphosphatemia, hypocalcemia, and vitamin D deficiency. Do not normalize PTH reflexively. In G5D, KDIGO suggests approximately 2-9 times the assay upper limit; marked changes warrant treatment review. Interpret serial PTH with calcium and phosphate. KDIGO 2017 recommendations 4.2.1-4.2.4.
📝 Case Summary & Clinical Pearls
🔑 Key Clinical Pearls:
Stepwise Approach to CKD-MBD: Start with dietary phosphorus restriction and phosphate binders, replete 25-OH vitamin D, then add active vitamin D if needed, and finally calcimimetics for severe cases.
Monitor Starting at eGFR Less Than 45: Begin checking calcium, phosphorus, PTH, and vitamin D when eGFR falls below 45 mL/min/1.73m².
Avoid High Calcium-Phosphate Product: Ca × Phos greater than 55 mg²/dL² increases vascular calcification risk. Prioritize lowering phosphorus.
Balance PTH Suppression: In nondialysis G3a-G5, no optimal PTH target is established: assess serial trends and modifiable factors. In G5D, approximately 2-9 times the assay upper limit is a guide, with marked trends prompting review. Avoid treatment oversuppression and interpret PTH with calcium and phosphate.
Distinguish Vitamin D Types: Nutritional vitamin D (ergocalciferol, cholecalciferol) for repletion. Active vitamin D (calcitriol, analogues) for PTH suppression.