🎯 Key Concept: Water vs Sodium Balance
Sodium disorders reflect water balance, not sodium balance
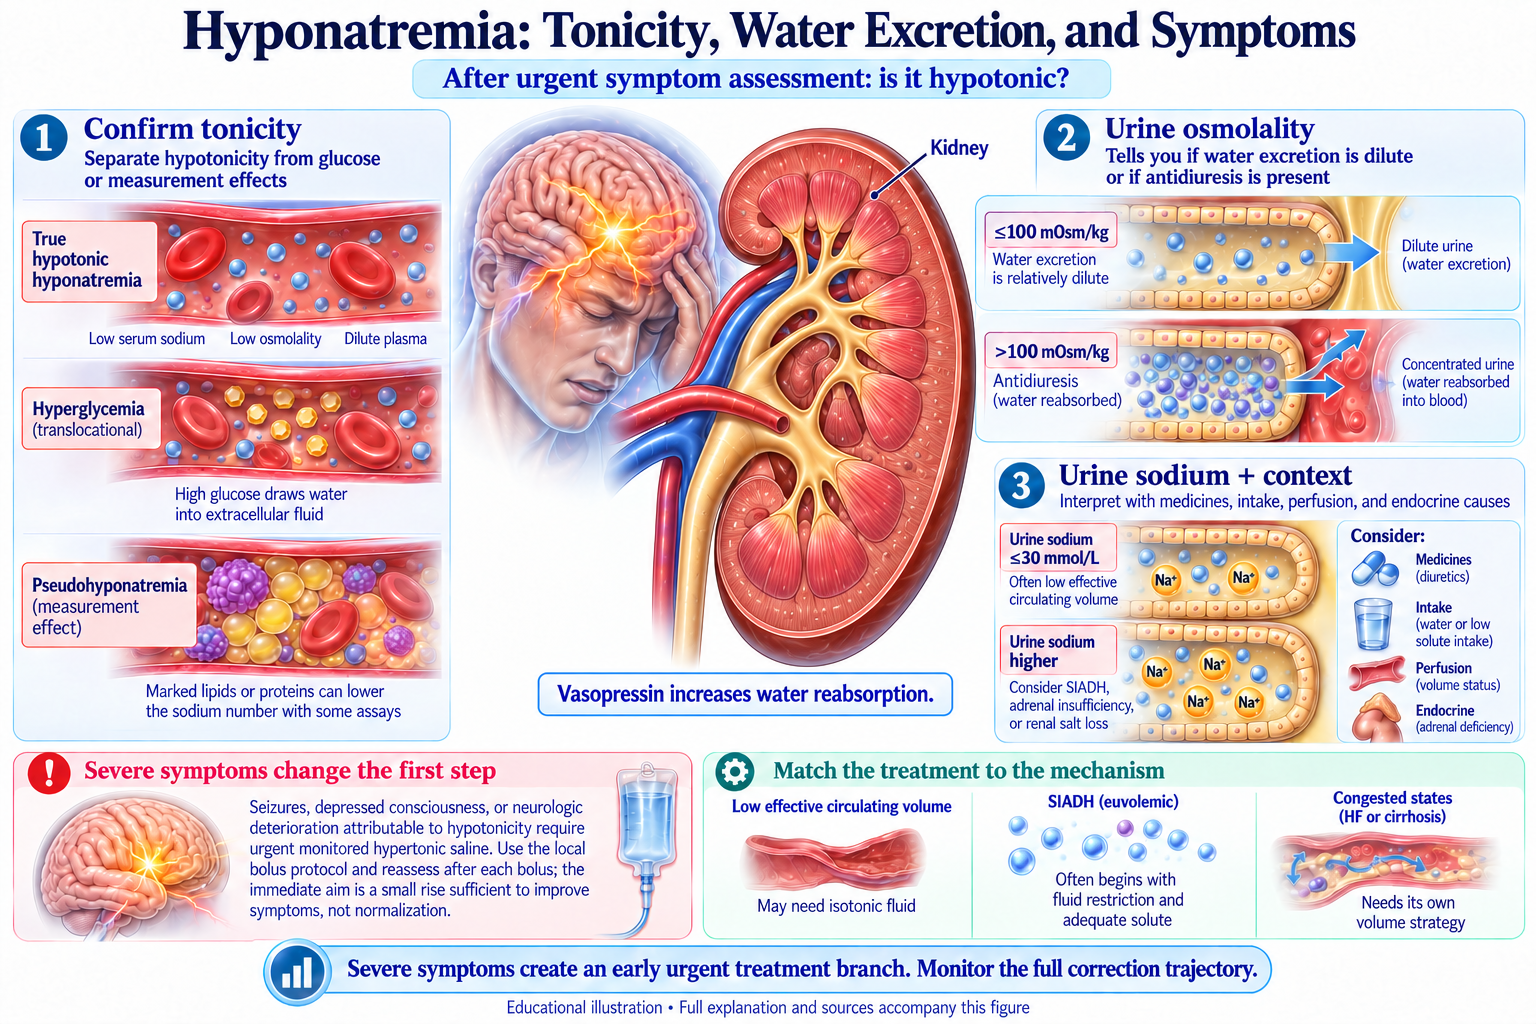
ADH controls water retention → affects serum sodium concentration
Visual reference
Browse the visual reference library · Download lesson Markdown
Choose the fluid for the problem
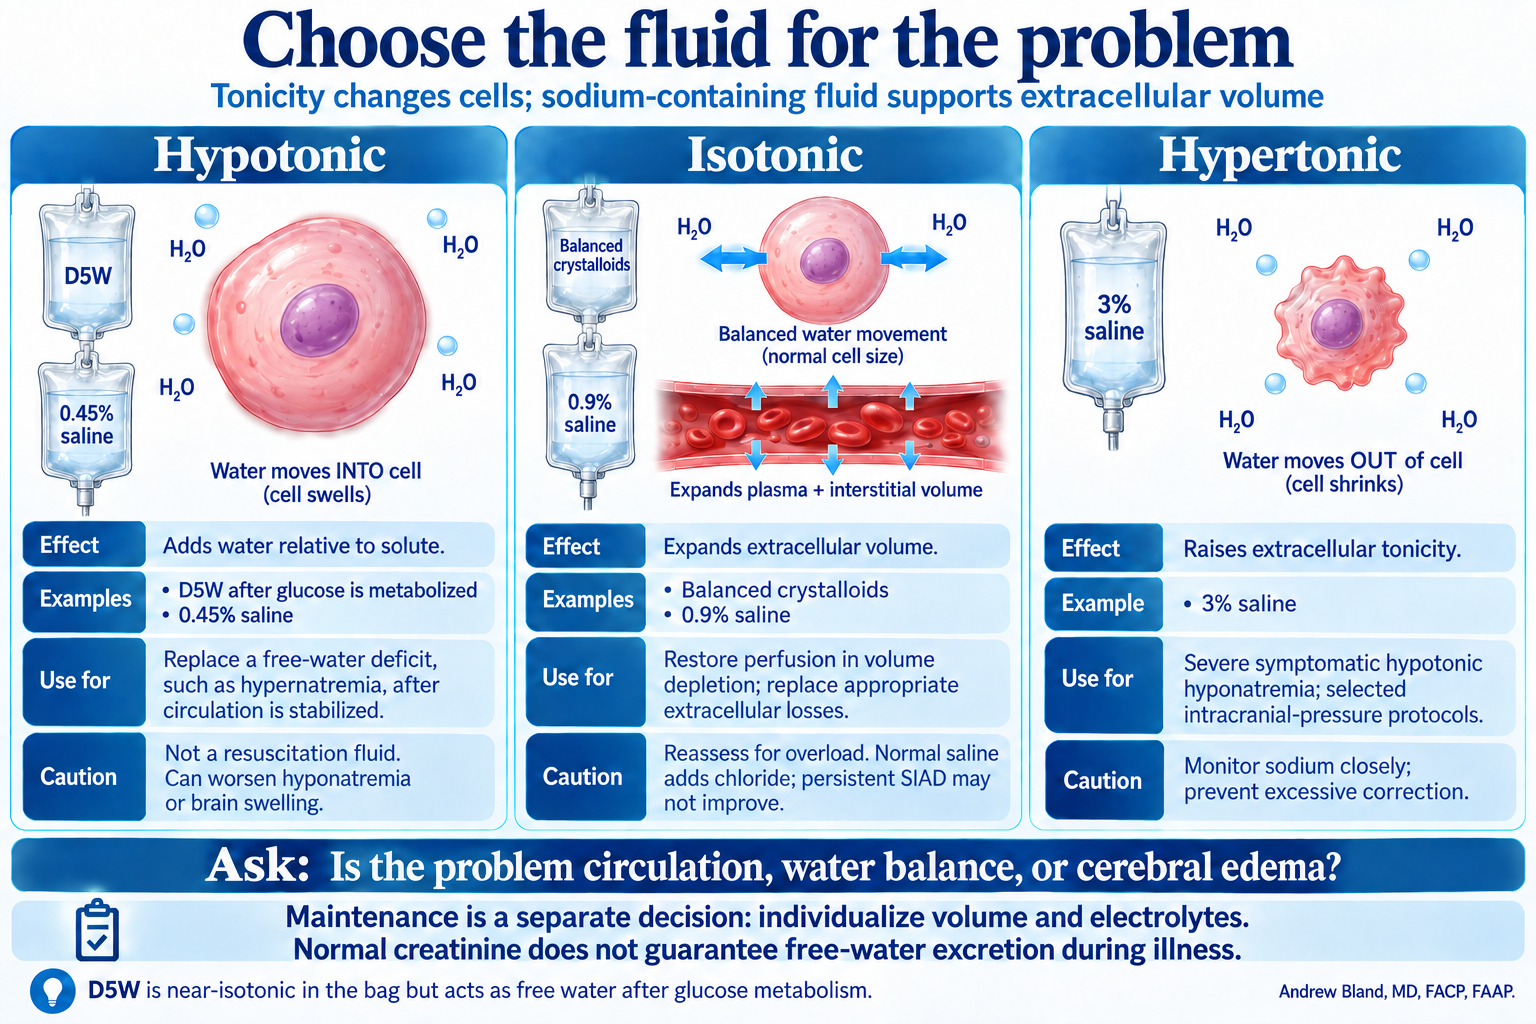
Separate circulation, water balance and cerebral edema from routine maintenance.
Hypotonic: replace water relative to solute
D5W becomes electrolyte-free water after glucose metabolism; 0.45% saline supplies both sodium and a free-water component. These can replace an identified water deficit, including hypernatremia, once circulation is stabilized. They are not resuscitation fluids and can worsen hyponatremia or brain swelling when water excretion is limited.
Isotonic: support extracellular volume
Balanced crystalloids such as LR and 0.9% saline are commonly used to restore perfusion in volume depletion. They distribute through extracellular fluid, including interstitial fluid; they do not remain entirely intravascular. Reassess perfusion, lungs, urine output and cumulative balance. In persistent SIAD, 0.9% saline may fail to improve sodium or sometimes worsen it.
Hypertonic: raise tonicity for a defined indication
3% saline is used for severe symptomatic hypotonic hyponatremia and selected intracranial-pressure protocols. Its use requires a defined goal and close monitoring. The initial objective in symptomatic hyponatremia is a modest effective rise, followed by reassessment and adherence to correction limits.
Compare bag pH carefully
Examples from product labels: D5W pH 4.3 (3.2–6.5); 0.45% saline 5.6 (4.5–7.0); NS 5.6 (4.5–7.0); LR 6.5 (6.0–7.5); 3% saline 5.0 (4.5–7.0). These are product-specific examples, not universal constants. Bag pH is unitless and does not predict the systemic acid–base effect. Neither NS nor LR contains bicarbonate in the bag; LR supplies a metabolizable precursor.
A functioning kidney regulates balance; it does not guarantee unlimited tolerance
With adequate perfusion, solute availability and intact regulation, kidneys adjust urine water and electrolyte excretion to match changing intake and losses. They do not literally create the needed water or salt. Pain, nausea, surgery and low effective circulation can sustain ADH even when creatinine is normal, limiting excretion of an administered water load. Both excess free water and excess sodium-containing fluid can cause harm.
Adult maintenance: prescribe the need, not a default bag
Maintenance replaces ordinary ongoing needs when oral or enteral intake is insufficient; resuscitation, deficit replacement and abnormal ongoing losses are separate prescriptions. Adult comparative evidence is limited and setting-specific. NICE permits a hypotonic maintenance regimen, while the small TOPMAST surgical trial illustrates the tradeoff: more sodium-rich fluid increased retention and hyperchloremia, whereas hypotonic fluid produced more mild hyponatremia. Neither result establishes one composition as best for every adult.
Pediatrics: Holliday–Segar is an estimate, not a complete prescription
The weight-based Holliday–Segar calculation estimates maintenance water volume; it does not itself choose tonicity or guarantee that a sick child needs the full calculated amount. The strongest pediatric trial evidence concerns fluid composition: PIMS reported hyponatremia in 4% with isotonic versus 11% with hypotonic maintenance fluid. The AAP recommends isotonic maintenance solutions with appropriate dextrose and potassium for most eligible hospitalized children aged 28 days–18 years; important excluded conditions need specific plans. Rate, all other fluid sources, sodium and clinical balance still require reassessment.
Teach the bedside decision
Ask first whether IV fluid is needed, then choose the goal, composition, amount and reassessment interval. Count oral intake, feeds, medication carriers and ongoing losses. Stop IV maintenance as soon as adequate enteral intake makes it unnecessary. A resuscitation-fluid trial does not answer a maintenance-fluid question.
| Fluid | Example pH | Labeled range |
|---|---|---|
| D5W | 4.3 | 3.2–6.5 |
| 0.45% saline | 5.6 | 4.5–7.0 |
| 0.9% saline / NS | 5.6 | 4.5–7.0 |
| Lactated Ringer’s | 6.5 | 6.0–7.5 |
| 3% saline | 5.0 | 4.5–7.0 |
Bag pH does not predict systemic acid–base response. Product examples and ranges are sourced in the references below.
Supporting evidence
- NICE CG174: adult IV fluid therapy
- TOPMAST: adult postoperative maintenance-fluid randomized trial
- PIMS: isotonic versus hypotonic pediatric maintenance fluid
- AAP guideline: maintenance intravenous fluids in children
- Holliday and Segar: original maintenance-water paper
- LR label with pH range
- Saline labels with pH range
- D5W label with pH range
- 3% saline label with pH range
🌊 Sodium Disorder Overview
🌊 Hyponatremia
Na+ < 135 mEq/L - Most common electrolyte disorder
- Mechanism: Excess water relative to sodium
- Key Test: Urine osmolality (ADH activity)
- Emergency: RIB therapy for severe symptomatic
- Correction: 4-8 mEq/L per 24 hours (standard risk)
- Risk Factors: Chronic, alcoholism, liver disease
🔥 Hypernatremia
Na+ > 145 mEq/L - Water deficit state
- Mechanism: Loss of free water or gain of sodium
- Formula: Water deficit = TBW × [(Na/140) - 1]
- Correction: ≤0.5 mEq/L per hour maximum
- Volume Status: Hypovolemic (most common)
- Risk: Cerebral edema with rapid correction
🔄 Physiology Review
ADH System: The Master Water Controller
🧠 Central Control
- Osmoreceptors: Hypothalamic sensors
- Threshold: ~280-290 mOsm/kg
- Response: ADH release + thirst
- Fine-tuning: 1% osmolality change triggers response
🫘 Kidney Response
- Target: Collecting duct principal cells
- Mechanism: Aquaporin-2 (AQP2) insertion
- Result: Water reabsorption
- Range: 50-1200 mOsm/kg urine concentration
⚖️ Clinical Assessment
- Urine Osmolality: Reflects ADH activity
- Serum Osmolality: Confirms true hypo/hypernatremia
- Volume Status: Separate from ADH system
- Medications: Many affect ADH
🎯 Clinical Decision Framework
Systematic Approach to Sodium Disorders
1️⃣ Confirm the Value
- Rule out pseudohyponatremia
- Check serum osmolality
- Consider lab error
2️⃣ Assess Symptoms
- Neurologic manifestations
- Acute vs chronic onset
- Severity assessment
3️⃣ Volume Status
- Physical examination
- Hemodynamic assessment
- Urine sodium
4️⃣ Urine Studies
- Urine osmolality (key test)
- Urine sodium
- Urine volume
5️⃣ Medication Review
- Diuretics
- SSRIs, antiepileptics
- NSAIDs, ACE inhibitors
6️⃣ Treatment Plan
- Address underlying cause
- Safe correction rate
- Monitor response
🌊 Comprehensive Hyponatremia Guide Available!
For in-depth coverage including 2024 RIB protocols, emerging therapies, and risk stratification