Visual reference
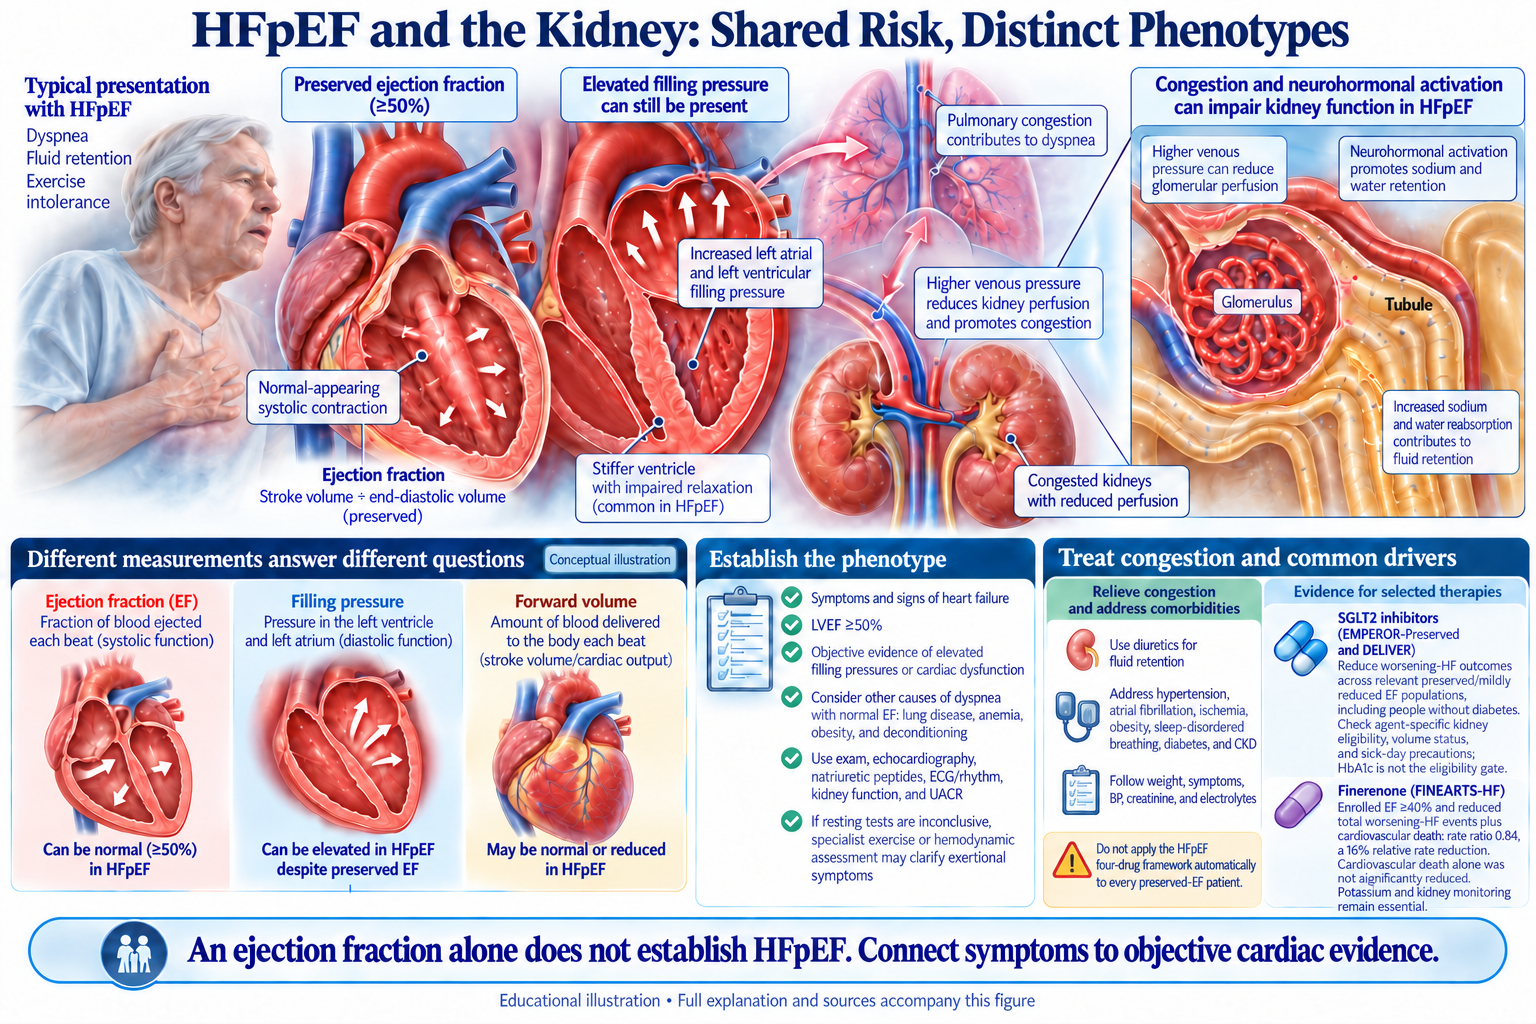
Browse the visual reference library · Download lesson Markdown
The Kidney Sits at the Pathophysiological Heart of HFpEF
The Paulus-Tschope paradigm established that comorbidities—obesity, diabetes, CKD, hypertension—drive HFpEF through coronary microvascular endothelial inflammation rather than ischemia-mediated cardiomyocyte death. This inflammatory cascade begins when elevated IL-6, TNF-alpha, and CRP provoke endothelial dysfunction, reducing nitric oxide bioavailability, ultimately causing titin hypophosphorylation and increased cardiomyocyte stiffness.
Mineralocorticoid Receptor Overactivation
Perhaps the most therapeutically actionable pathway linking CKD to HFpEF. MRs expressed in cardiomyocytes, fibroblasts, vascular endothelium, and immune cells stimulate TGF-beta, IL-6, and PAI-1, promoting fibrosis in both organs simultaneously. Critically, obesity and hyperglycemia cause ligand-independent MR activation even without elevated aldosterone.
Galectin-3
Central mediator of bidirectional cardiorenal injury. Reduced eGFR correlates strongly with increased galectin-3 (r = −0.71, p = 0.01). Kidney injury upregulates galectin-3, which then initiates cardiac inflammatory and fibrotic processes.
Hemodynamic Consequences
Reduced GFR decreases sodium filtration capacity while RAAS activation prevents compensatory reductions in tubular reabsorption. Elevated central venous pressure from HFpEF reduces the arteriovenous pressure gradient across the kidney, creating “renal tamponade” that further decreases GFR.
Albuminuria Predicts Heart Failure with Striking Consistency
ARIC Study (10,975 participants, 8.3 years): Continuous graded relationship between UACR and HF incidence, extending even within the “normal” range:
| UACR Category | HR for Incident HF |
|---|---|
| Optimal (<5 mg/g) | Reference |
| Intermediate-normal (5–9 mg/g) | HR 1.54 |
| High-normal (10–29 mg/g) | HR 1.91 |
| Microalbuminuria (30–299 mg/g) | HR 2.49 |
| Macroalbuminuria (≥300 mg/g) | HR 3.47 |
HOPE study: Every 0.4 mg/mmol UACR increase raises HF hospitalization risk by 11%. TOPCAT: 50% albuminuria reduction decreased HF hospitalization by approximately 30–70%.
Shah's Phenomapping: CKD as the Highest-Risk HFpEF Phenotype
Shah and colleagues published the HFpEF phenomapping study in Circulation in 2015. In 397 patients, clustering of detailed clinical and cardiac data identified phenogroups with different outcomes. This observational classification illustrates heterogeneity; it is not a universal diagnostic score. Phenomapping study
Phenogroup 3—the “CKD-vascular aging” phenotype—demonstrated HR 4.2 (95% CI 2.0–9.1, p<0.001) for HF hospitalization. Characterized by older age (median 75), CKD as the defining feature, 43% AF prevalence, pulmonary hypertension, and RV dysfunction.
The TOPCAT phenogroup analysis identified a similar cluster with the best response to spironolactone (NNT 14). CKD-associated HFpEF represents both the highest-risk phenotype and the subgroup most likely to benefit from targeted therapy.
The CKM Syndrome Framework (AHA 2023)
Formally defined by Ndumele et al. (October 2023 AHA Presidential Advisory) as “a systemic disorder characterized by pathophysiological interactions among metabolic risk factors, CKD, and the cardiovascular system.”
| Stage | Definition | Key Actions |
|---|---|---|
| 0 | No CKM risk factors | Prevention |
| 1 | Excess/dysfunctional adiposity | Screen with eGFR + UACR even here |
| 2 | Metabolic risk factors or moderate-high CKD | SGLT2i for CKD, HF, or T2D (eGFR ≥20) |
| 3 | Subclinical CVD or risk equivalent; KDIGO G4/G5 (eGFR <30) = automatic Stage 3 | Intensive prevention; add finerenone for DKD with UACR >300 on ACEi/ARB |
| 4a/4b | Established CVD ± kidney failure | Full cardiorenal GDMT |
KDIGO Stage G4/G5 CKD (eGFR <30) is now treated as a cardiovascular risk equivalent under the CKM framework, warranting intensive prevention even without overt CVD.
SGLT2 Inhibitors: Class I, Level A for HFpEF
EMPEROR-Preserved
5,988 patients, LVEF >40%: empagliflozin HR 0.79 (95% CI 0.69–0.90; p<0.001), NNT 30 over 26.2 months. Consistent benefit regardless of diabetes status.
DELIVER
6,263 patients, LVEF >40%: dapagliflozin HR 0.82 (95% CI 0.73–0.92; p<0.001). Benefit maintained even with LVEF ≥60%.
Pooled Meta-Analysis (n=12,251)
Consistent benefit across all prespecified subgroups including LVEF ≥60%. The 2023 ESC Focused Update upgraded SGLT2i to Class I, Level A for HFmrEF and HFpEF.
FINEARTS-HF: Finerenone as Definitive HFpEF Therapy
6,001 patients, LVEF ≥40%, across 634 sites in 37 countries: primary composite rate ratio 0.84 (95% CI 0.74–0.95; p=0.007) — 16% relative risk reduction. Remarkably consistent across the EF spectrum (p for interaction = 0.75).
K+ >5.5 mmol/L: 14.3% finerenone vs. 6.9% placebo (2.6-fold increase). By eGFR: eGFR ≥60 (0.3% vs 0.1% hospitalization), eGFR 45–<60 (0.4% vs 0.3%), eGFR <45 (1.2% vs 0.4%). No deaths attributable to hyperkalemia.
Finerenone Advantages Over Steroidal MRAs
- No affinity for androgen or progesterone receptors — eliminates gynecomastia, breast pain, menstrual irregularities
- ARTS trial: hyperkalemia 5% (finerenone) vs. 12% (spironolactone), p=0.05
- Balanced heart-kidney tissue distribution vs. steroidal MRAs (kidney-concentrated)
- AMBER trial: spironolactone caused hyperkalemia in 64.2% vs. 11.6% with finerenone in FIDELITY
FIDELIO/FIGARO/FIDELITY for DKD
- FIDELIO-DKD: Renal composite HR 0.82 (p=0.001); CV composite HR 0.86 (p=0.03)
- FIGARO-DKD: CV composite HR 0.87 (p=0.03); HF hospitalization HR 0.71 (29% reduction); new-onset HF reduced by 32%
- FIDELITY pooled (n=13,171): CV composite HR 0.86, kidney composite HR 0.77, HF hospitalization HR 0.82
CONFIDENCE Trial: Simultaneous Initiation
CONFIDENCE randomized patients with type 2 diabetes, CKD, and albuminuria to finerenone, empagliflozin, or both. At 180 days the combination reduced UACR more than either monotherapy. This short-term albuminuria endpoint does not establish the added effect on kidney failure or mortality. Monitor potassium, kidney function, and volume status; concomitant SGLT2 use in subgroup analyses was not randomized evidence of eliminating finerenone-related hyperkalemia. CONFIDENCE
Hyperkalemia with finerenone was substantially lower in SGLT2i users: 8.1% vs. 18.7% without SGLT2i. This suggests SGLT2i may mitigate finerenone-associated hyperkalemia through natriuretic and kaliuretic effects.
KDIGO 2024 Sequential Approach
- Optimize ACEi/ARB to maximum tolerated dose
- Add SGLT2i regardless of diabetes status if eGFR ≥20
- Add finerenone if persistent UACR ≥30 despite RAASi + SGLT2i (eGFR ≥25, K+ ≤5.0)
- Consider GLP-1 RA if additional glycemic control, CV risk reduction, or weight management needed
Finerenone Dosing
| eGFR | Starting Dose | Target |
|---|---|---|
| ≥60 | 20 mg daily | 20–40 mg |
| 25–<60 | 10 mg daily | 20 mg |
| <25 | Not recommended for initiation | |
Monitor K+ and eGFR at 4 weeks post-initiation. Uptitrate if K+ ≤4.8 and eGFR stable. If K+ >5.5: hold until ≤5.0, then restart at lower dose.
HFpEF Screening in Nephrology Practice
ADA 2024: Screen for asymptomatic HF in diabetics using BNP or NT-proBNP. In CKD (eGFR <60), higher thresholds of 200–400 pg/mL may be appropriate.
Practical Nephrology Screening Algorithm
- All T2D + CKD patients: annual NT-proBNP
- NT-proBNP ≥125 pg/mL (≥200 if eGFR <45): trigger echocardiography
- Combine symptoms + elevated NP + echo abnormalities → HFA-PEFF scoring
- Scores 2–4: cardiology referral
- Scores ≥5: confirm diagnosis; initiate SGLT2i + consider finerenone
The Four Pillars of Cardiorenal Protection
- RAASi (ACEi/ARB) — foundation of cardiorenal therapy
- SGLT2i — Class I, Level A for HFpEF
- Finerenone — definitive MRA for HFpEF and DKD
- GLP-1 RA — complementary CV, renal, and metabolic benefits
References
- Shah SJ, et al. Phenomapping for novel classification of HFpEF. Circulation. 2015;131(3):269-279. PubMed
- Ndumele CE, Rangaswami J, Chow SL, et al. Cardiovascular-Kidney-Metabolic Health: A Presidential Advisory From the American Heart Association. Circulation. 2023;148(20):1606-1635. DOI | PubMed
- Anker SD, et al. Empagliflozin in HFpEF (EMPEROR-Preserved). N Engl J Med. 2021;385(16):1451-1461. PubMed
- Solomon SD, et al. Dapagliflozin in HFmrEF/HFpEF (DELIVER). N Engl J Med. 2022;387(12):1089-1098. PubMed
- Bakris GL, et al. Finerenone reduces kidney failure events (FIDELIO-DKD). N Engl J Med. 2020;383(23):2219-2229. PubMed
- Pitt B, et al. Cardiovascular events with finerenone in DKD (FIGARO-DKD). N Engl J Med. 2021;385(24):2252-2263. PubMed
- Solomon SD, et al. Finerenone in HFmrEF and HFpEF (FINEARTS-HF). N Engl J Med. 2024;391(16):1475-1485. PubMed
- Agarwal R, Green JB, Heerspink HJL, et al. Finerenone with Empagliflozin in Chronic Kidney Disease and Type 2 Diabetes. N Engl J Med. 2025;393(6):533-543. DOI | PubMed
- Blecker S, Matsushita K, Köttgen A, et al. High-normal albuminuria and risk of heart failure in the community. Am J Kidney Dis. 2011;58(1):47-55. PubMed
- Paulus WJ, Tschope C. A novel paradigm for HFpEF: comorbidities drive myocardial dysfunction. J Am Coll Cardiol. 2013;62(4):263-271. PubMed