Anti-GBM Disease (Goodpasture Syndrome)
Pulmonary-Renal Syndrome, Urgent Diagnosis, and Triple Therapy
Andrew Bland, MD, FACP, FAAP
Visual reference
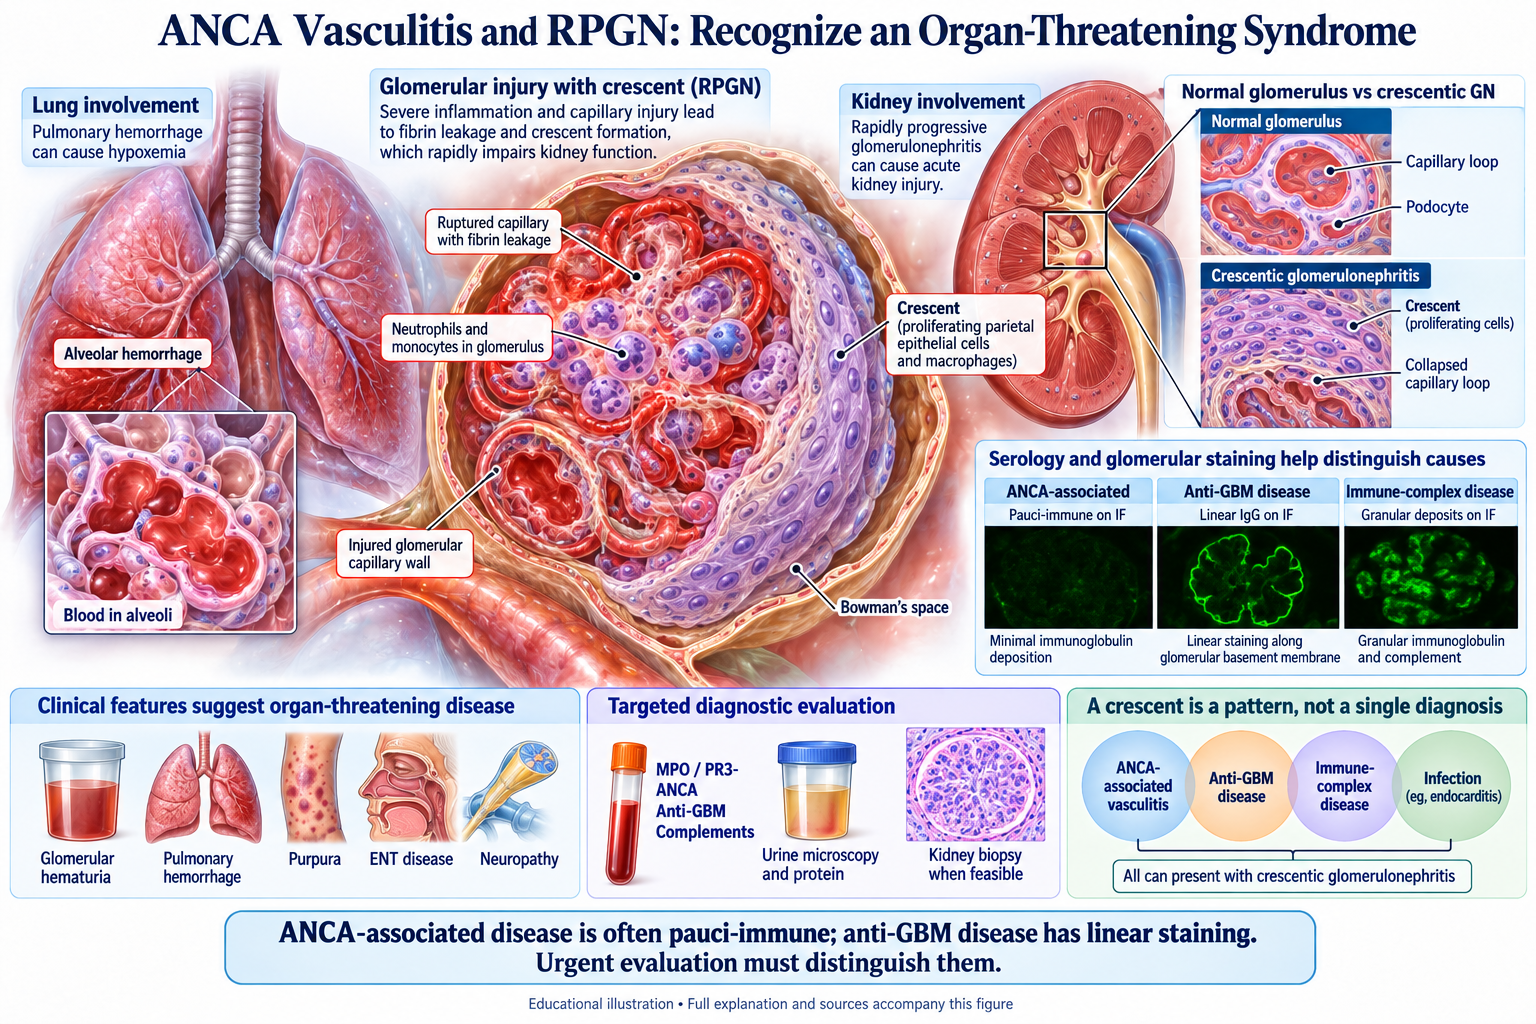
Browse the visual reference library · Download lesson Markdown
Epidemiology & Pathophysiology
Anti-GBM disease represents 5–10% of RPGN cases and 1–2% of all GN. Annual incidence approximately 0.5–2 per million.
Target & Mechanism
- Target antigen: NC1 domain of α3 chain of type IV collagen (α3(IV)NC1)
- Located in GBM, alveolar basement membrane, and Descemet membrane
- IgG anti-GBM antibodies circulate and deposit along GBM in a linear pattern
- Classical pathway complement activation → neutrophil infiltration → crescent formation → rapid loss of renal function
⚠️ Critical: Anti-GBM disease is rapidly progressive and requires urgent diagnosis and treatment. Linear IgG on immunofluorescence with serum anti-GBM antibodies confirms diagnosis. Pulmonary involvement (hemoptysis + alveolar infiltrates) occurs in ~50% and signifies life-threatening disease.
Goodpasture Syndrome (~50% of patients)
Identical anti-GBM antibodies target alveolar basement membrane causing diffuse alveolar hemorrhage, hemoptysis, and pulmonary infiltrates. Can be life-threatening; often precedes renal manifestations.
Triggering Factors
- Respiratory infection (viral URI; may expose cryptic epitope)
- Smoking (induces alveolar permeability; increases pulmonary hemorrhage risk)
- Hydrocarbon exposure
- Genetic predisposition (HLA-DR2, HLA-DQ2)
Clinical Presentation
Renal-Limited Disease (50%)
- Sudden onset hematuria + proteinuria
- Progressive rise in creatinine (doubling times 24–72 hours typical)
- Dysmorphic RBC + RBC casts on UA
- No systemic symptoms (distinguishes from systemic vasculitis)
Pulmonary-Renal Syndrome
- Hemoptysis (blood-tinged sputum to life-threatening hemorrhage)
- Dyspnea, chest pain
- Diffuse alveolar infiltrates on CXR
- Anemia from ongoing hemorrhage
Laboratory Features
- Creatinine often markedly elevated (1.5–10+ mg/dL)
- Normal C3, C4 (distinguishes from immune-complex RPGN)
- Negative ANA, ANCA, cryoglobulins (seronegative RPGN pattern)
- Positive serum anti-GBM antibodies in >90% (may be transiently negative in fulminant cases)
Treatment: Triple Therapy (Urgent Initiation Required)
⚠️ Critical Principle: Anti-GBM disease progresses rapidly to ESRD. Treatment must begin within days of diagnosis. Delay >4 weeks is associated with poor renal outcomes.
1. High-Dose Corticosteroids
- IV methylprednisolone 500 mg–1 g daily for 3–5 days, then oral prednisone 1 mg/kg/day
- Slow taper over 8–12 weeks
2. Cyclophosphamide
- 2 mg/kg/day oral (dose-reduced if elderly or low WBC) OR pulsed IV 1 g/m² x 3 monthly
- Duration: 8–12 weeks oral; monitor CBC weekly (target WBC 4,000–8,000)
3. Plasmapheresis
- Especially critical when Cr >5.8 mg/dL, oliguria/anuria, or fulminant pulmonary hemorrhage
- 40–60 mL/kg daily for 7–14 days or until anti-GBM antibodies undetectable
- Removes pre-formed antibodies; cyclophosphamide prevents new antibody synthesis
📚 Key Point: Dialysis requirement alone does not settle treatment. KDIGO identifies a poor-recovery exception when dialysis at presentation coexists with 100% crescents or >50% global glomerulosclerosis in an adequate biopsy and no pulmonary hemorrhage. Pulmonary hemorrhage and dual ANCA positivity change the decision. Isolated anti-GBM relapse is uncommon; dual-positive disease needs ANCA-informed follow-up.
Prognosis
Renal Outcomes by Creatinine at Diagnosis
| Creatinine at Diagnosis | Avoid Dialysis |
|---|---|
| <2.8 mg/dL | 85–90% |
| 2.8–5.8 mg/dL | 50% |
| >5.8 mg/dL | 10% |
| Oliguria/anuria | <5% |
Biopsy: >80% crescents = poor prognosis; <50% crescents = better prognosis.
Timing: Initiation within 2 weeks of symptom onset yields much better outcomes. Initiation >4 weeks: most become ESRD.
RPGN Classification: Key Differentiating Features
| Feature | Anti-GBM | ANCA-RPGN | Immune-Complex RPGN |
|---|---|---|---|
| Serology | Anti-GBM+ | ANCA+ (MPO/PR3) | ANA+, anti-dsDNA+ |
| Complement | Normal | Normal | LOW C3, C4 |
| IF Pattern | LINEAR IgG | Pauci-immune | Granular |
| Pulmonary | Alveolar hemorrhage | Upper respiratory | Rare |
| Plasmapheresis | Essential in severe | Limited role | Optional |
Clinical Pearls
- Linear IgG on IF is virtually pathognomonic
- Serum anti-GBM antibodies may be transiently negative in fulminant disease; negative serology does not exclude diagnosis
- Time to treatment is the most modifiable predictor of outcome
- Plasmapheresis should NOT be delayed waiting for biopsy if clinical suspicion is high
- Anti-GBM disease does NOT recur after antibodies clear
- Dialysis initiation is not a contraindication to therapy — late renal recovery possible years later
- Smoking cessation essential in Goodpasture syndrome
References
- McAdoo SP, Pusey CD. Anti-GBM disease. CJASN. 2017;12(7):1162-1172. PubMed
- Levy JB, Turner AN, Rees AJ, et al. Long-term outcome of anti-glomerular basement membrane antibody disease treated with plasma exchange and immunosuppression. Ann Intern Med. 2001;134(11):1033-1042. PubMed
- . Chapter 14: Anti-glomerular basement membrane antibody glomerulonephritis. Kidney Int Suppl (2011). 2012;2(2):240-242. PubMed
- Hellmark T, Johansson C, Wieslander J. Characterization of anti-GBM antibodies involved in Goodpasture's syndrome. Kidney Int. 1994;46(3):823-9. PubMed
© Urine Nephrology Now — Clinical Mastery Series