Cryoglobulinemic Glomerulonephritis
HCV-Associated Vasculitis, DAA Revolution, and Renal Outcomes
Andrew Bland, MD, FACP, FAAP
Visual reference
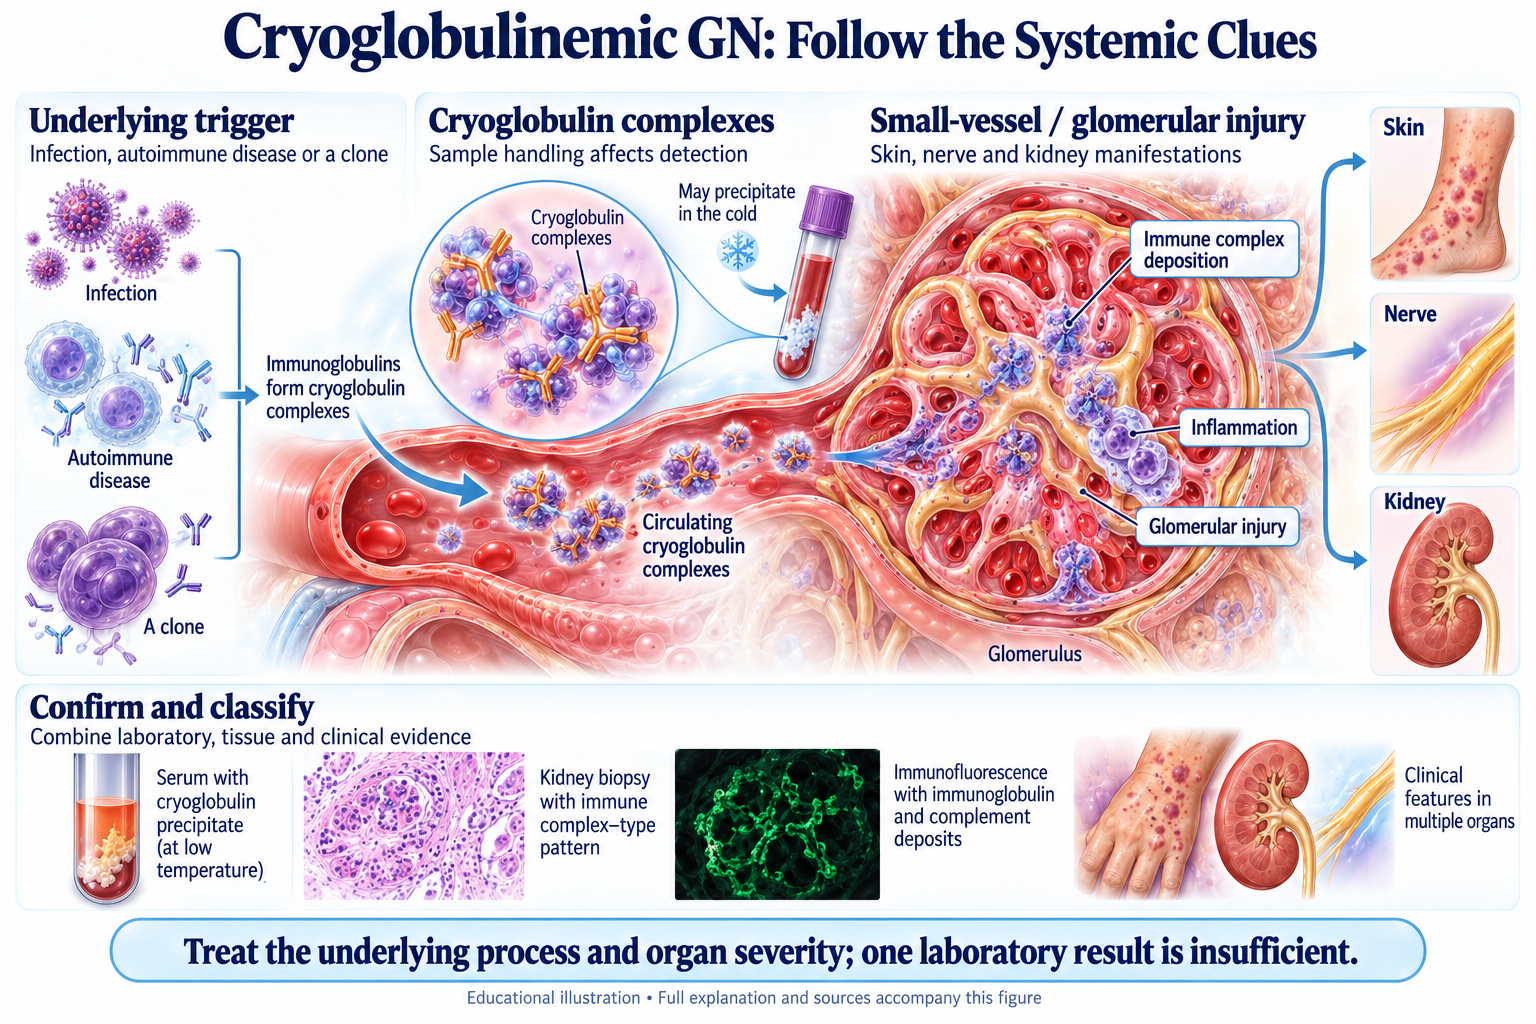
Browse the visual reference library · Download lesson Markdown
Overview & Classification
Cryoglobulinemia consists of circulating immune complexes that precipitate at temperatures <37°C, causing systemic vasculitis.
| Type | % | Composition | Association | Renal Involvement |
|---|---|---|---|---|
| Type I | 10–15% | Monoclonal Ig (usually IgM) | Waldenstrom, CLL, myeloma | Rare (1–3%) |
| Type II | 50–60% | Monoclonal IgM-RF + polyclonal IgG | HCV (80–90%) | VERY COMMON (40–60%) |
| Type III | 25–30% | Polyclonal IgM-RF + polyclonal IgG | SLE, Sjögren, chronic infections | Less common (10–15%) |
📚 Key Point: Type II (mixed essential) cryoglobulinemia is the most common form causing significant kidney disease, and HCV is the primary driver globally. DAA therapy for HCV has revolutionized outcomes.
Clinical Presentation: Classic Triad (50–60% of patients)
1. Palpable Purpura
Lower extremities, buttocks. Triggered by cold exposure. Blanch incompletely. May progress to ulceration.
2. Arthralgia/Arthritis
Large joints (knees, ankles, shoulders). Non-erosive. Intermittent or chronic.
3. Renal Disease (GN)
Hematuria, proteinuria (<3 g/day typical), hypertension, progressive renal dysfunction.
Hallmark Laboratory Finding
📚 Clinical Pearl: Low C4 (normal C3) is a hallmark laboratory finding in cryoglobulinemic vasculitis. Combined with positive cryoglobulins + HCV serology + palpable purpura + GN, the diagnosis is clear. C4 may improve with treatment; follow organ findings and the underlying driver as well.
Diagnosis
Key Tests
- Serum cryoglobulins (essential): Must be collected in warm tube, transported at 37°C. Cryocrit >5% indicates significant.
- Complement: C4 very low (often <5 mg/dL); C3 normal. C1q low.
- HCV serology/RNA: Positive in 80–90% of Type II
- Rheumatoid factor: Positive (80–90%)
- ANA, ANCA: Usually negative
Kidney Biopsy
- LM: Membranoproliferative pattern; intraluminal thrombi (PAS-positive hyaline deposits — pathognomonic)
- IF: Granular IgM, IgG + C3, C4, C1q deposition
- EM: Subendothelial deposits; may see intraluminal fibrillar or crystalline material
Treatment
HCV-Positive Cryoglobulinemia: DAAs First-Line
- Sofosbuvir-based or glecaprevir/pibrentasvir: Pan-genotypic, 12-week course, >95% cure rate
- Outcomes: Viral eradication often improves vasculitis, but clinical and renal responses vary; persistence or relapse can occur despite sustained virologic response.
- Most patients do NOT need concurrent immunosuppression
Severe Flares Requiring Acute Treatment
- Plasmapheresis: 1–1.5 plasma volumes daily for 5–10 sessions for RPGN, severe vasculitis
- Corticosteroids: IV methylprednisolone 500 mg–1 g daily x 3–5 days for acute flares
- Rituximab: 375 mg/m² weekly x 4; 70–80% response rate; depletes B cells producing IgM-RF
- Cyclophosphamide: Reserved for severe RPGN with crescents
📚 Key Point: DAA therapy for HCV has revolutionized cryoglobulinemia management. HCV eradication is the primary goal. Most patients do NOT need long-term immunosuppression once HCV is cured. C4 normalization serves as a marker of disease activity and treatment response.
Prognosis
DAA Era (Modern)
- HCV eradication: >95% SVR with modern DAAs
- Vasculitis remission: Not guaranteed by viral clearance; follow clinical organ involvement as well as HCV RNA.
- Renal outcomes: Recovery depends on the severity and chronicity of injury. Persistent glomerulonephritis requires reassessment after antiviral treatment.
| Favorable | Unfavorable |
|---|---|
| Low baseline creatinine | Baseline Cr >2 mg/dL |
| <2 g/day proteinuria | Nephrotic-range proteinuria |
| No crescent formation | Circumferential crescents |
| Early DAA initiation | Delayed treatment (established CKD) |
Key Differential Diagnosis
| Feature | Cryoglobulinemia | Type II MPGN | Lupus GN | ANCA-RPGN |
|---|---|---|---|---|
| Cryoglobulins | Positive | Negative | Negative | Negative |
| C4 Level | Very low | Normal or low C3 | Low C3, C4 | Normal |
| HCV | +80–90% | Negative | Negative | Negative |
| Purpura | Palpable (typical) | Rare | Rare | Absent |
| DAA Response | Excellent | N/A | N/A | N/A |
Clinical Pearls
- Cryoglobulin testing supports diagnosis; false-negative results require attention to warm sample handling and repeat evaluation when suspicion remains high — collected in warm tube at 37°C
- Low C4 with normal C3 is characteristic pattern
- Palpable purpura + GN + HCV = cryoglobulinemia until proven otherwise
- DAAs are curative for HCV (>95% SVR); excellent first-line therapy
- Cryoglobulinemia remission is slower than HCV eradication — allow 6–12 months
- Severe RPGN flares warrant plasmapheresis + rituximab (not just DAAs)
- C4 may improve with treatment; follow organ findings and the underlying driver as well; use as marker of disease activity
References
- Cacoub P, Comarmond C, Domont F, et al. Cryoglobulinemia Vasculitis. Am J Med. 2015;128(9):950-955. PubMed
- De Vita S, Soldano F, Isola M, et al. Preliminary classification criteria for the cryoglobulinaemic vasculitis. Ann Rheum Dis. 2011;70(7):1183-90. PubMed
- Comarmond C, Cacoub P, Saadoun D. Treatment of chronic hepatitis C-associated cryoglobulinemia vasculitis at the era of direct-acting antivirals. Ther Adv Gastroenterol. 2020;13:1756284820942617. PubMed
- Zaja F, De Vita S, Mazzaro C, et al. Efficacy and safety of rituximab in type II mixed cryoglobulinemia. Blood. 2003;101(10):3827. PubMed
- Terrier B, et al. Cryoglobulinemia vasculitis: an update. Curr Opin Rheumatol. 2013;25(1):10-18. PubMed
- Terrier B, Cacoub P. Renal involvement in HCV-related vasculitis. Clin Res Hepatol Gastroenterol. 2013;37(4):334-9. PubMed
© Urine Nephrology Now — Clinical Mastery Series