Lupus Nephritis
Treatment Evidence, Biologic Selection, Serologically Quiet Disease, and Clinical Decision-Making
Andrew Bland, MD, FACP, FAAP
Visual reference
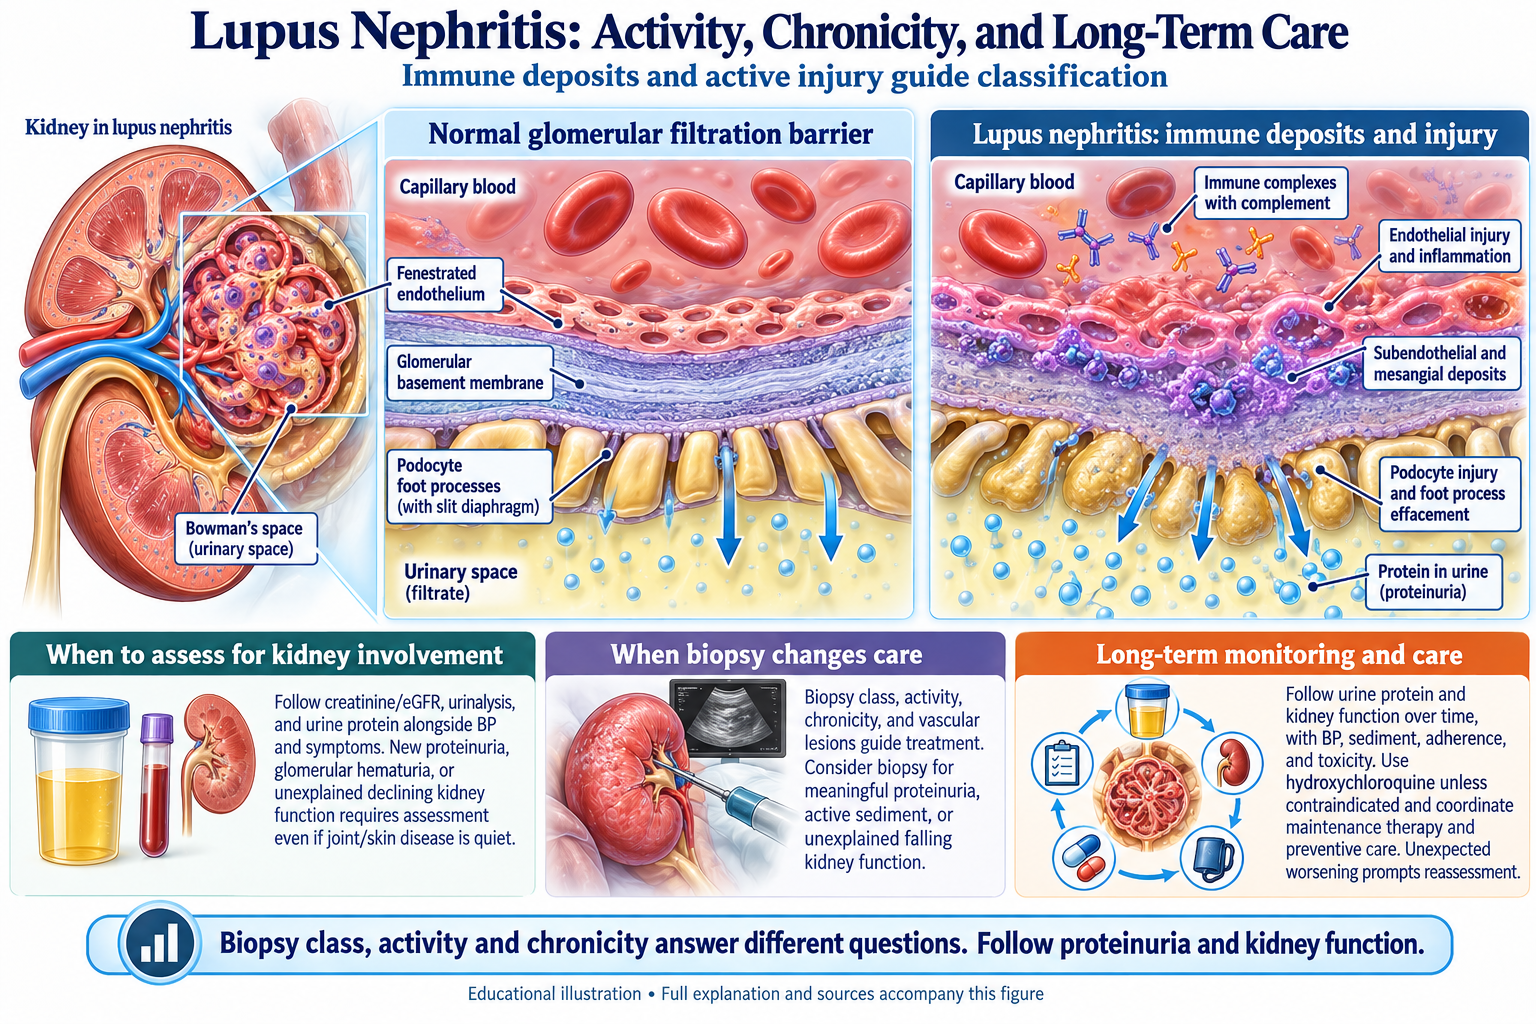
Browse the visual reference library · Download lesson Markdown
Executive Summary
- Lupus nephritis affects 25–60% of SLE patients; remains a leading cause of ESRD
- Neither 2024 ACR nor KDIGO guidelines specifically recommend obinutuzumab over belimumab based on proteinuria thresholds — obinutuzumab was approved after guideline publication
- Post-hoc BLISS-LN: belimumab showed NO observed benefit in patients with UPCR ≥3 g/g
- REGENCY subgroup: obinutuzumab showed greatest benefit in patients with UPCR ≥3 g/g and Class IV disease
- CNI contraindicated when eGFR ≤45 mL/min/1.73m²
- Cyclophosphamide should be held in reserve for crescentic disease
- Serologically quiet lupus nephritis (15–40% of cases) does not indicate milder disease
Clinical Presentation Patterns
Classic Presentation
Proteinuria (often nephrotic-range), microscopic hematuria with dysmorphic RBCs/RBC casts, hypertension, varying degrees of renal insufficiency. Elevated anti-dsDNA antibodies and depressed C3/C4.
Serologically Quiet Lupus Nephritis (15–40% of cases)
Active histological disease despite normal or near-normal serologies. Mechanisms include:
- In situ immune complex formation: Local complement activation without systemic depletion
- Tissue-resident B cells and tertiary lymphoid structures: Local antibody production within the kidney
- Alternative autoantibody specificities: Anti-C1q, anti-nucleosome, anti-ENO1 not routinely measured
- Predominantly cellular immunity: T cell-mediated mechanisms independent of humoral autoimmunity
Renal-First Presentation (10–20%)
Lupus nephritis as the first manifestation of SLE, sometimes without meeting full classification criteria. Biopsy-proven Class III or IV alone provides 10 points on 2019 ACR/EULAR criteria — sufficient for SLE classification even without other features.
Biopsy: ISN/RPS Classification
| Class | Description | Typical Presentation |
|---|---|---|
| I | Minimal mesangial | Minimal proteinuria, preserved GFR |
| II | Mesangial proliferative | Mild proteinuria, microscopic hematuria |
| III | Focal proliferative (<50%) | Proteinuria, hematuria, variable GFR decline |
| IV | Diffuse proliferative (≥50%) | Nephrotic/nephritic, often impaired GFR |
| V | Membranous | Nephrotic syndrome, usually preserved GFR initially |
| VI | Advanced sclerotic (>90% sclerosed) | ESRD, minimal active disease |
Activity and Chronicity Indices
Activity Index (max 24): Fibrinoid necrosis and crescents weighted x2. High activity (>6) demands urgent aggressive therapy.
Chronicity Index (max 12): Glomerulosclerosis, fibrous crescents, tubular atrophy, interstitial fibrosis. High chronicity influences expectations but does NOT reduce treatment intensity for active disease.
Treatment Evidence: Induction Therapy
Mycophenolate Mofetil (MMF)
- ALMS trial: non-inferior to cyclophosphamide (56.2% vs 53.0% response)
- Ginzler trial: superior CR in predominantly African American/Hispanic patients
- Better tolerated; no gonadal toxicity or bladder cancer risk
- Preferred by 2024 ACR Voting Panel over cyclophosphamide based on toxicity profile
Obinutuzumab (Anti-CD20) — FDA Approved October 2025
- Glycoengineered type II anti-CD20; more complete B-cell depletion than rituximab
- REGENCY (Phase III, N=271): CRR 46.4% vs 33.1% placebo (p=0.02)
- CRR with prednisone ≤7.5 mg/day: 42.7% vs 30.9%
- Renal-related events or death: 17.8% vs 33.8% (HR 0.5)
- Greatest benefit in UPCR ≥3 g/g and Class IV disease
- Peripheral B-cell depletion sustained in 95% through week 76
Voclosporin (CNI)
- AURORA 1: CRR 40.8% vs 22.5% placebo (p<0.001); aggressive steroid taper to 2.5 mg by week 16
- Fixed dosing without therapeutic drug monitoring
Belimumab (Anti-BAFF)
- BLISS-LN: primary efficacy renal response 43% vs 32% (p=0.03)
- Renal-related events or death reduced by 49% (HR 0.51)
Cyclophosphamide
- Euro-Lupus low-dose (6 fortnightly pulses of 500 mg, cumulative 3 g) equivalent to high-dose; preferred approach
- Hold in reserve for crescentic disease, RPGN, or failure of obinutuzumab-based therapy
- Toxicity concerns: gonadal failure (26–62%), malignancy risk, hemorrhagic cystitis
Biologic Selection: Evidence-Based Decision Framework
| Baseline Proteinuria | Preferred Biologic | Evidence Level |
|---|---|---|
| UPCR <3 g/g | Either belimumab or obinutuzumab | Phase III data for both |
| UPCR ≥3 g/g | Obinutuzumab preferred | Belimumab shows no benefit in this subgroup |
| UPCR >5 g/g | Obinutuzumab strongly preferred | Greatest benefit in high-proteinuria patients |
Treatment Decision Framework by Clinical Factor
| Clinical Factor | Treatment Implication |
|---|---|
| UPCR ≥3 g/g | Obinutuzumab preferred per REGENCY subgroups |
| eGFR ≤45 | CNI contraindicated per FDA/KDIGO |
| High Chronicity (≥6/12) | Kidney-protective approach paramount; obinutuzumab's eGFR advantage valuable |
| Serologically quiet | May reflect tissue-resident B-cell disease; potent B-cell depletion may be particularly effective |
| No crescents | No specific indication for cyclophosphamide; reserve as salvage |
| Crescents/fibrinoid necrosis | Cyclophosphamide may be favored (2024 ACR); consider Euro-Lupus protocol |
Maintenance Therapy
- MMF preferred over azathioprine: ALMS maintenance trial showed treatment failure 16.4% vs 32.4% (HR 0.44, p=0.003)
- Add-on belimumab reduces flare risk during maintenance
The Diagnostic Delay Problem
- 92% of patients with UPCR <1 g/g had ISN/RPS Class III, IV, V, or mixed histology on biopsy
- 85% of patients with proteinuria <0.5 g/day had Class III, IV, or mixed histology
- 50% of SLE patients with UPCR 0.2–0.5 g/g progressed to ≥0.5 g/g; median time 1.2 years
Monitoring and Response Assessment
Response Definitions
- Complete Renal Response: UPCR <0.5, normal/near-baseline creatinine, inactive sediment
- Partial Renal Response: ≥50% proteinuria reduction to sub-nephrotic, stable/improved creatinine
Serologically Quiet Disease Monitoring
- Serial proteinuria quantification (most sensitive marker)
- Serum creatinine and eGFR trajectory
- Urine sediment examination
- Anti-C1q antibodies if initially positive
- Repeat biopsy at 6–12 months if response uncertain
Prognosis
Favorable: Early treatment, CR within 12 months, low chronicity index, adherence to maintenance.
Unfavorable: African American/Hispanic ethnicity, high chronicity (>4), delayed treatment, persistent proteinuria >1 g/day at 12 months, elevated baseline creatinine, non-adherence.
| Chronicity Index | Expected Response | Clinical Approach |
|---|---|---|
| 0–2 (Low) | Excellent potential for complete recovery | Standard triple therapy |
| 3–5 (Moderate) | Good response possible, some residual impairment | Aggressive therapy, close monitoring |
| 6–8 (High) | Stabilization achievable, full recovery unlikely | Prioritize kidney-protective agents |
| 9–12 (Very High) | Limited benefit from aggressive IS | Consider supportive care, transplant planning |
References
- Hanly JG, et al. Frequency and outcome of lupus nephritis. Rheumatology. 2016;55(2):252-262. PubMed
- Tektonidou MG, et al. Risk of ESRD in lupus nephritis, 1971–2015. Arthritis Rheumatol. 2016;68(6):1432-1441. PubMed
- Furie R, et al. Belimumab in lupus nephritis (BLISS-LN). NEJM. 2020;383(12):1117-1128. PubMed
- Dooley MA, et al. MMF vs azathioprine maintenance. NEJM. 2011;365(20):1886-1895. PubMed
- Rovin BH, et al. Voclosporin in lupus nephritis (AURORA 1). Lancet. 2021;397(10289):2070-2080. PubMed
- Furie RA, Rovin BH, Garg JP, et al. Efficacy and Safety of Obinutuzumab in Active Lupus Nephritis. N Engl J Med. 2025;392(15):1471. PubMed
- Cozzani E, et al. Serology of lupus erythematosus. Autoimmune Dis. 2014;2014:321359. PubMed
- Esdaile JM, et al. Laboratory tests as predictors of SLE exacerbations. Arthritis Rheum. 1996;39(3):370-378. PubMed
- Austin HA 3rd, et al. Predicting renal outcomes in severe lupus nephritis. Kidney Int. 1994;45(2):544-550. PubMed
- Austin HA 3rd, et al. Prognostic factors in lupus nephritis. Am J Med. 1983;75(3):382-391. PubMed
- Parikh SV, Rovin BH. Current and emerging therapies. JASN. 2016;27(10):2929-2939. PubMed
- Anders HJ, et al. Lupus nephritis. Nat Rev Dis Primers. 2020;6(1):7. PubMed
- Trendelenburg M, et al. Anti-C1q antibodies in active lupus nephritis. NDT. 2006;21(11):3115-3121. PubMed
- Faurschou M, et al. Prognostic factors in lupus nephritis: diagnostic delay. J Rheumatol. 2006;33(8):1563-1569. PubMed
- Weening JJ, et al. ISN/RPS classification of lupus GN. JASN. 2004;15(2):241-250. PubMed
- Hill GS, et al. Predictive power of the second renal biopsy. Kidney Int. 2001;59(1):304-316. PubMed
- Austin HA 3rd, et al. Therapy of lupus nephritis (NIH trial). NEJM. 1986;314(10):614-619. PubMed
- Houssiau FA, et al. Euro-Lupus Nephritis Trial. Arthritis Rheum. 2002;46(8):2121-2131. PubMed
- Houssiau FA, et al. 10-year follow-up of Euro-Lupus trial. Ann Rheum Dis. 2010;69(1):61-64. PubMed
- Henderson L, et al. Treatment for lupus nephritis (Cochrane). Cochrane Database Syst Rev. 2012;12:CD002922. PubMed
- Appel GB, et al. MMF vs CYC for induction (ALMS). JASN. 2009;20(5):1103-1112. PubMed
- Isenberg D, Appel GB, Contreras G, et al. Influence of race/ethnicity on response to lupus nephritis treatment: the ALMS study. Rheumatology (Oxford). 2010;49(1):128. PubMed
- Ginzler EM, et al. MMF vs IV CYC for lupus nephritis. NEJM. 2005;353(21):2219-2228. PubMed
- Furie R, et al. Obinutuzumab in proliferative LN (NOBILITY). Ann Rheum Dis. 2022;81(1):100-107. PubMed
- Rovin BH, Furie RA, Ross Terres JA, et al. Kidney Outcomes and Preservation of Kidney Function With Obinutuzumab in Patients With Lupus Nephritis: A Post Hoc Analysis of the NOBILITY Trial. Arthritis Rheumatol. 2024;76(2):247. PubMed
- Rovin BH, et al. Rituximab in LN (LUNAR). Arthritis Rheum. 2012;64(4):1215-1226. PubMed
- Rovin BH, et al. Voclosporin dose-ranging. Kidney Int. 2019;95(1):219-231. PubMed
- Saxena A, Ginzler EM, Gibson K, et al. Safety and Efficacy of Long-Term Voclosporin Treatment for Lupus Nephritis in the Phase 3 AURORA 2 Clinical Trial. Arthritis Rheumatol. 2024;76(1):59. PubMed
- Rovin BH, Furie R, Teng YKO, et al. A secondary analysis of the Belimumab International Study in Lupus Nephritis trial examined effects of belimumab on kidney outcomes and preservation of kidney function in patients with lupus nephritis. Kidney Int. 2022;101(2):403. PubMed
- Dooley MA, et al. MMF vs AZA maintenance (ALMS). NEJM. 2011;365(20):1886-1895. PubMed
- Houssiau FA, et al. MAINTAIN Nephritis Trial. Ann Rheum Dis. 2010;69(12):2083-2089. PubMed
- Jones RB, et al. Rituximab vs CYC in ANCA vasculitis (RITUXVAS). NEJM. 2010;363(3):211-220. PubMed
- Weidenbusch M, Römmele C, Schröttle A, et al. Beyond the LUNAR trial. Efficacy of rituximab in refractory lupus nephritis. Nephrol Dial Transplant. 2013;28(1):106. PubMed
- Liu Z, et al. Multitarget therapy for induction. Ann Intern Med. 2015;162(1):18-26. PubMed
- Moroni G, Porata G, Raffiotta F, et al. Beyond ISN/RPS Lupus Nephritis Classification: Adding Chronicity Index to Clinical Variables Predicts Kidney Survival. Kidney360. 2022;3(1):122-132. PubMed
- Nakagawa S, Toyama T, Iwata Y, et al. The relationship between the modified National Institute of Health activity and chronicity scoring system, and the long-term prognosis for lupus nephritis: A retrospective single-center study. Lupus. 2021;30(11):1739. PubMed
- Bajema IM, et al. Revised ISN/RPS classification: modified NIH indices. Kidney Int. 2018;93(4):789-796. PubMed
- Moroni G, Porata G, Raffiotta F, et al. Predictors of increase in chronicity index and of kidney function impairment at repeat biopsy in lupus nephritis. Lupus Sci Med. 2022;9(1). PubMed
- Arriens C, Chen S, Karp DR, et al. Prognostic significance of repeat biopsy in lupus nephritis: Histopathologic worsening and a short time between biopsies is associated with significantly increased risk for end stage renal disease and death. Clin Immunol. 2017;185:3. PubMed
- Liu X, Chen X, Yang C, et al. Biologicals for the treatment of lupus nephritis: a Bayesian network meta-regression analysis. Front Immunol. 2024;15:1445814. PubMed
- Tunnicliffe DJ, et al. Immunosuppressive treatment for LN (Cochrane). Cochrane Database Syst Rev. 2018;6:CD002922. PubMed
- Perge B, Papp G, Bói B, et al. Prognostic Factors of the Progression of Chronic Kidney Disease and the Development of End-Stage Renal Disease in Patients with Lupus Nephritis: A Retrospective Cohort Study. J Clin Med. 2025;14(3). PubMed
- Carlucci PM, Li J, Fava A, et al. High incidence of proliferative and membranous nephritis in SLE patients with low proteinuria in the Accelerating Medicines Partnership. Rheumatology (Oxford). 2022;61(11):4335. PubMed
- Wang S, Spielman A, Ginsberg M, et al. Short- and Long-Term Progression of Kidney Involvement in Systemic Lupus Erythematosus Patients with Low-Grade Proteinuria. Clin J Am Soc Nephrol. 2022;17(8):1150. PubMed
- Sammaritano LR, Askanase A, Bermas BL, et al. 2024 American College of Rheumatology (ACR) Guideline for the Screening, Treatment, and Management of Lupus Nephritis. Arthritis Rheumatol. 2025;77(9):1115. PubMed
- KDIGO 2024 Clinical Practice Guideline for LN. Kidney Int. 2024;105(1S):S1-S69. DOI
- Beck LH, Ayoub I, Caster D, et al. KDOQI US Commentary on the 2021 KDIGO Clinical Practice Guideline for the Management of Glomerular Diseases. Am J Kidney Dis. 2023;82(2):121. PubMed
© Urine Nephrology Now — Clinical Mastery Series