Minimal Change Disease
Comprehensive Review — Podocytopathy, Steroid Response, and Long-Term Management
Andrew Bland, MD, FACP, FAAP
Visual reference
Browse the visual reference library · Download lesson Markdown
Epidemiology & Pathophysiology
MCD represents the most common cause of nephrotic syndrome in children (85–90%) and a significant etiology in adults (10–15%). Peak childhood incidence occurs between ages 2–6 years.
Pathogenesis
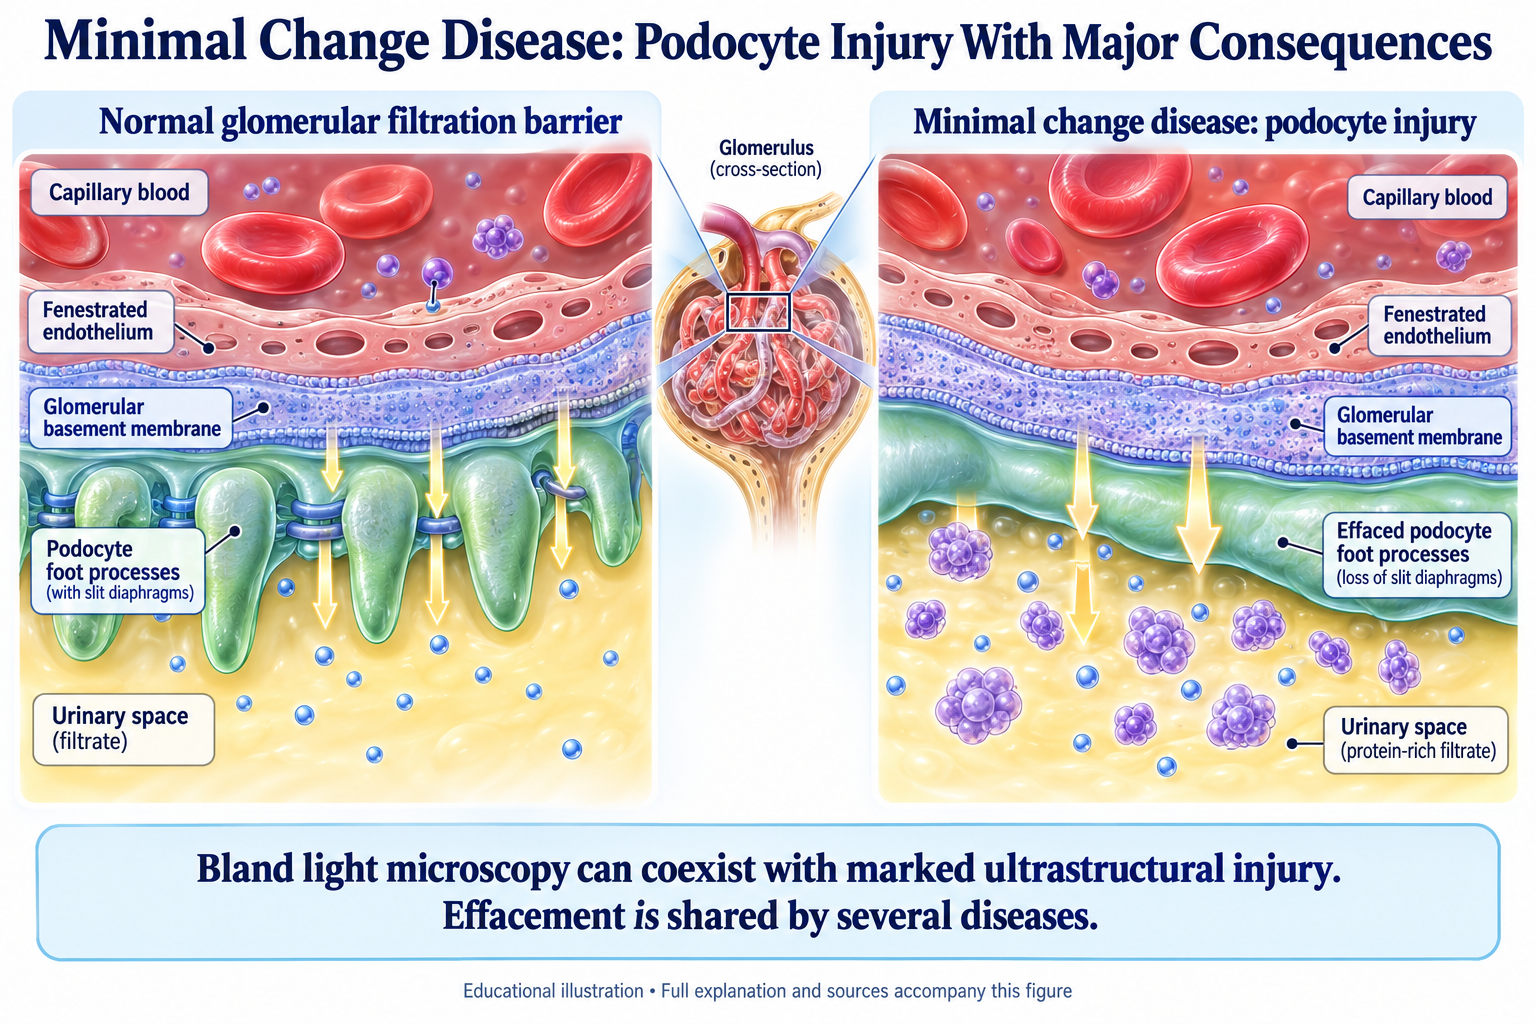
MCD is a podocytopathy characterized by functional podocyte injury without histologic abnormality on light microscopy:
- Podocyte foot process effacement on electron microscopy (EM) is the hallmark
- Loss of slit diaphragm proteins (ZO-1, nephrin, podocin) without structural damage
- Presumed immune mechanism: T-cell dysfunction producing a circulating permeability factor (CPF)
- Evidence: rapid proteinuria response to immunosuppression, association with Hodgkin lymphoma and allergies
- Proteinuria is highly selective (mainly albumin)
📚 Key Point: Foot process effacement is reversible with appropriate therapy — this distinguishes MCD from other podocytopathies and explains the excellent prognosis.
Clinical Presentation
Typical Features
- Sudden onset nephrotic syndrome (proteinuria >3.5 g/day, typically 1–10 g/day)
- Hypoalbuminemia with resultant edema (periorbital, lower extremity, ascites)
- Normal blood pressure and absence of hematuria (key differentiator from other GN)
- Normal complement levels (C3, C4 normal)
- No systemic disease features
📚 Clinical Pearl: In children with nephrotic syndrome presenting with edema, proteinuria, hypoalbuminemia, normal creatinine, no hematuria, and normal complement, the presentation is highly predictive of MCD. Many pediatric nephrologists empirically treat with corticosteroids without biopsy. Adults and atypical features warrant biopsy.
Diagnosis
Laboratory Findings
- Serum: Hypoalbuminemia (often <2 g/dL), decreased immunoglobulins, normal creatinine
- Urinalysis: Heavy proteinuria, absent or minimal hematuria (≤5 RBC/hpf)
- Lipiduria: Oval fat bodies, fatty casts (pathognomonic appearance)
- Complement: Normal C3, C4 (rules out immune-complex disease)
- Serologies: Negative ANA, ANCA, anti-GBM
Kidney Biopsy
| Modality | Finding |
|---|---|
| Light Microscopy | Completely normal glomeruli (defining feature) |
| Electron Microscopy | Diffuse foot process effacement (hallmark). No electron-dense deposits. Normal GBM. |
| Immunofluorescence | Negative or trace staining (no immune complex deposits) |
Treatment
First-Line: Corticosteroid Therapy
| Population | Regimen | Response |
|---|---|---|
| Pediatric | Prednisone 60 mg/m²/day (max 80 mg) for 4–6 weeks, then taper | 90% achieve CR within 2 weeks |
| Adult | Prednisone 1 mg/kg/day (up to 80 mg) for 4–6 weeks, slow taper; total 8–12 weeks | 50–80% achieve CR (slower: 4–8 weeks) |
Response Categories
| Response | Definition |
|---|---|
| Complete Remission | Proteinuria <0.3 g/day, normal serum albumin |
| Partial Remission | Proteinuria 0.3–3.5 g/day (>50% reduction) |
| No Response | Proteinuria >3.5 g/day or <50% reduction — consider alternative diagnosis |
Steroid-Sparing Agents (for dependent/resistant disease)
- Cyclophosphamide: 2 mg/kg/day for 8–12 weeks (40–50% long-term remission)
- Mycophenolate mofetil: 1–1.5 g BID for 6–12 months
- Calcineurin inhibitors (tacrolimus, cyclosporine): effective for steroid-dependent disease
- Rituximab: increasingly used; can induce long-term remission in steroid-dependent/resistant cases
Supportive Care
- Salt restriction (<2–3 g/day)
- Diuretics for symptomatic edema (avoid excessive diuresis — risk of AKI)
- ACE-I or ARB to reduce proteinuria
- Statins for hyperlipidemia
- VTE prophylaxis if albumin <2 g/dL with high-risk features
📚 Key Point: Steroid-dependent disease is common in MCD and does not indicate poor long-term prognosis if managed appropriately with steroid-sparing agents. The key is achieving sustained remission on minimal therapy.
Prognosis
- Pediatric: 90–95% initial steroid response; normal renal function in >95% long-term; ESRD <5% at 20 years
- Adult: 50–80% achieve CR; excellent long-term survival (>95% at 20 years if well-managed)
- Relapses: 50–80% of children experience at least one relapse
📚 Clinical Pearl: Always counsel patients that MCD has an excellent prognosis. Multiple relapses do not worsen long-term renal outcomes if managed appropriately. Focus shifts to minimizing corticosteroid burden.
Key Differentiating Features
| Feature | MCD | FSGS | MPGN | Lupus GN |
|---|---|---|---|---|
| LM | Normal | Sclerosis | Proliferation | Proliferation |
| Hematuria | Absent/minimal | Present | Present | Present |
| Complement | Normal | Normal | Low (often) | Low |
| Steroid Response | Excellent (>80%) | Poor (<10%) | Variable | Variable |
Complications
- AKI: From massive proteinuria, severe hypoalbuminemia, or overly aggressive diuresis
- Thromboembolism: From urinary loss of anticoagulants (protein C, S, antithrombin)
- Infection: Asplenia-like state from urinary loss of immunoglobulins; increased pneumococcal risk
- Hyperlipidemia: Increased hepatic lipoprotein synthesis; cardiovascular risk
- Growth retardation (pediatric): From prolonged corticosteroid therapy
References
- Vivarelli M, et al. Minimal change disease. CJASN. 2017;12(2):332-345. PubMed
- KDIGO Glomerular Disease Work Group. KDIGO 2021 Clinical Practice Guideline. Kidney Int. 2021;99(3S):S1-S304. DOI
- Maas RJ, Deegens JK, Smeets B, et al. Minimal change disease and idiopathic FSGS: manifestations of the same disease. Nat Rev Nephrol 2016. PubMed 27748392.
- Hahn D, Samuel SM, Willis NS, et al. Corticosteroid therapy for nephrotic syndrome in children. Cochrane Database Syst Rev. 2020;2020(8):CD001533. DOI | PubMed
- Shalhoub RJ. Pathogenesis of lipoid nephrosis: a disorder of T-cell function. Lancet. 1974;2(7888):556-560. PubMed
© Urine Nephrology Now — Clinical Mastery Series