Effectiveness of Dialysis in Ammonia Removal
A Comprehensive Review of Modalities, Thresholds, and Outcomes
Andrew Bland, MD, FACP, FAAP
Visual reference
Browse the visual reference library · Download lesson Markdown
Ammonia Removal and Clinical Context
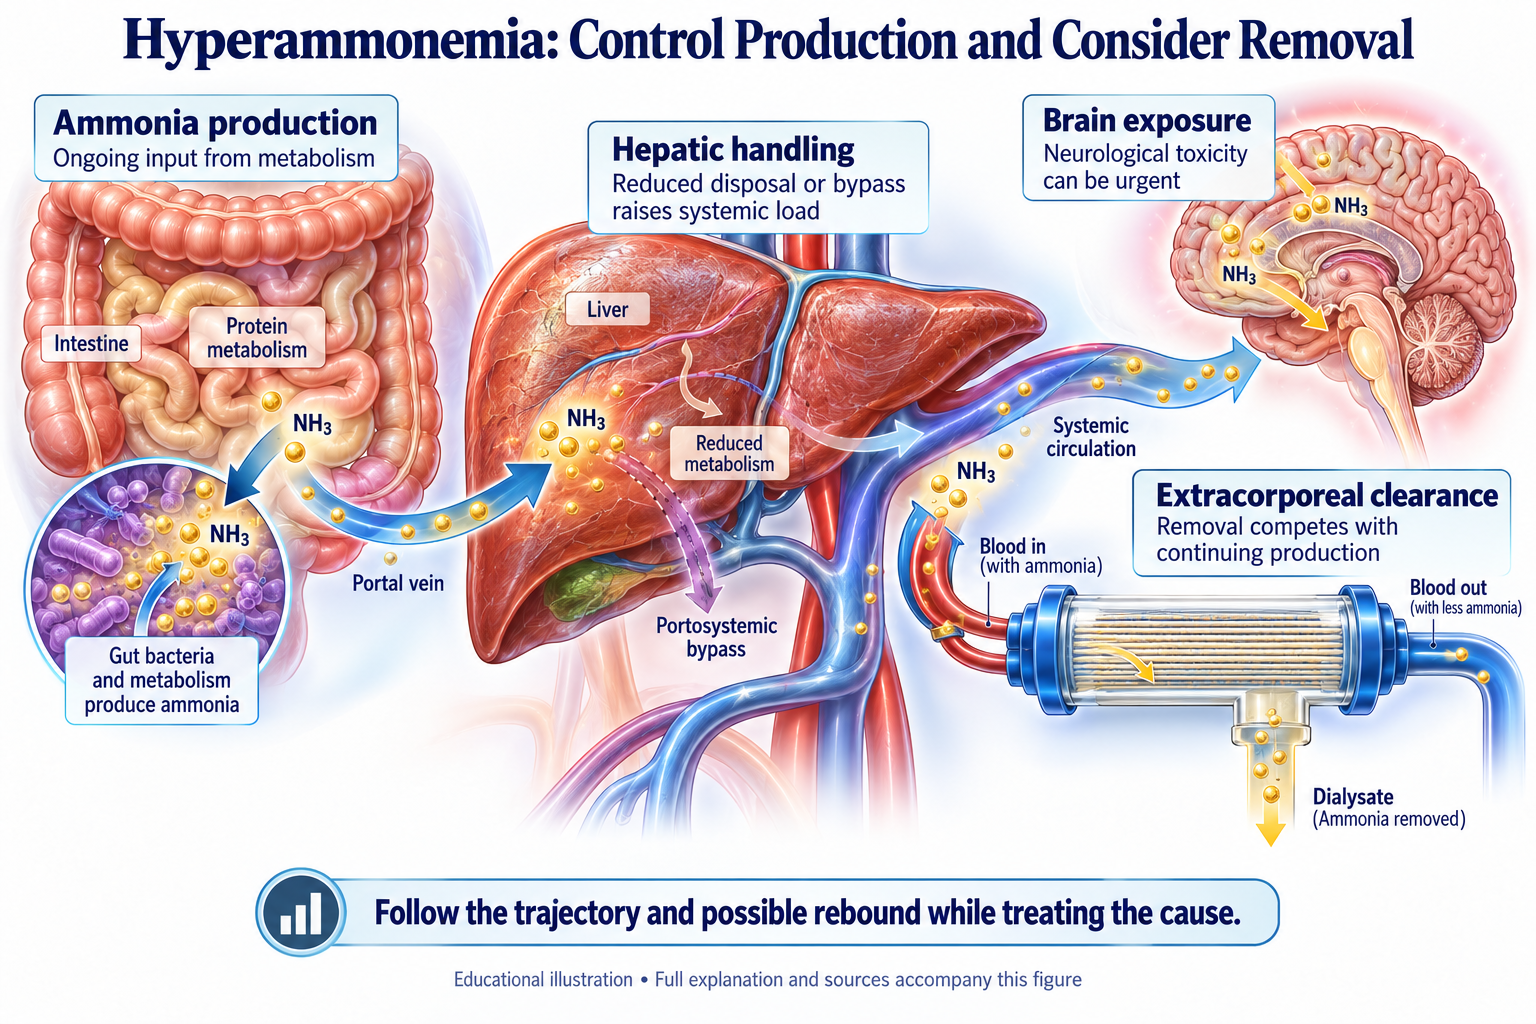
Ammonia is a small, dialyzable solute. Both intermittent hemodialysis and continuous kidney replacement therapy can remove it. Delivered clearance depends on the prescription, blood and dialysate or effluent flows, interruptions and ongoing ammonia production. A membrane label alone does not establish clinical superiority. The Gupta review summarizes the limited evidence across adults and children [1].
Acute liver failure, chronic cirrhosis, urea-cycle disorders, drug toxicity and post-transplant hyperammonemia require different diagnostic and treatment approaches. Identify and treat the cause while arranging extracorporeal support when appropriate.
When to Escalate
Severe or rapidly rising ammonia with encephalopathy, seizures or concern for cerebral edema warrants urgent critical-care, nephrology and cause-specific specialist assessment. Use the clinical trajectory as well as the concentration; do not wait for a universal numerical threshold or for creatinine to rise [1,4].
The reviewed adult evidence does not establish one initiation threshold that applies to every cause of hyperammonemia. Pediatric and neonatal metabolic emergencies need dedicated metabolic and pediatric nephrology protocols. Confirm the units and sample handling when interpreting a result.
Choosing a Modality
| Modality | Practical role | Limitation |
|---|---|---|
| Intermittent HD | Can provide rapid solute removal when tolerated | Rebound and hemodynamic/osmotic shifts require attention |
| Continuous therapy | Sustained control; often favored in unstable acute liver failure or cerebral-edema risk | Delivered dose and circuit downtime affect clearance |
| Sequential or prolonged strategies | May combine rapid initial reduction with sustained removal | Individual specialist prescription; no universal superior sequence |
Continued ammonia generation and redistribution can cause rebound after intermittent treatment. The fastest instantaneous clearance is not the only consideration when intracranial pressure or hemodynamic stability is at risk [1,4].
What the Studies Show
- Cardoso et al., 2018: In a multicenter acute-liver-failure registry cohort, CRRT was associated with lower ammonia and better 21-day transplant-free survival. This was observational evidence; it does not prove a survival benefit from a specific initiation threshold [2].
- Warrillow et al., 2020: A retrospective single-center study documented declining ammonia during early CRRT. It did not establish an optimal timing, dose or duration through randomization [3].
- Slack et al., 2014: Physiologic work measured ammonia clearance during hemofiltration in adults with liver disease. Clearance findings inform prescription design but should not be converted into a guaranteed neurological or survival benefit [5].
Monitoring During Treatment
Follow serial ammonia, neurologic status, hemodynamics, fluid balance and delivered treatment. Check electrolytes, particularly phosphate, and account for enhanced medication clearance. Coordinate stopping or tapering treatment with clinical recovery and continue surveillance for rebound [4].
Dialysis supports ammonia removal; it does not replace cause-directed therapy, metabolic treatment or liver-transplant assessment when indicated. Albumin dialysis and specialized membranes should not be presented as proven superior ammonia treatments on the basis of unverified comparative studies.
References
- Gupta S, Fenves AZ, Hootkins R. The Role of RRT in Hyperammonemic Patients. Clin J Am Soc Nephrol. 2016. PubMed PMID 27197910
- Cardoso FS, Gottfried M, Tujios S, et al. Continuous renal replacement therapy is associated with reduced serum ammonia levels and mortality in acute liver failure. Hepatology. 2018. PubMed PMID 28859230
- Warrillow S, Fisher C, Bellomo R. Correction and Control of Hyperammonemia in Acute Liver Failure: The Impact of Continuous Renal Replacement Timing, Intensity, and Duration. Crit Care Med. 2020. PubMed PMID 31939790
- Paine C, Pichler R. How We Treat Hyperammonemia in Acute Liver Failure. Clin J Am Soc Nephrol. 2024. PubMed PMID 37847521
- Slack AJ, Auzinger G, Willars C, et al. Ammonia clearance with haemofiltration in adults with liver disease. Liver Int. 2014. PubMed PMID 23786538
© Urine Nephrology Now — Clinical Mastery Series