Kidney Disease in End-Stage Liver Disease
A Comprehensive Review of Hepatorenal Syndrome
Andrew Bland, MD, FACP, FAAP
Visual reference
Browse the visual reference library · Download lesson Markdown
Abstract
This comprehensive review examines the pathophysiology, diagnosis, management, and outcomes of kidney disease in end-stage liver disease, with particular emphasis on hepatorenal syndrome (HRS). Recent advances in our understanding have led to significant changes in nomenclature and diagnostic criteria, with HRS type 1 now designated as HRS-AKI (acute kidney injury). The effectiveness of dialysis in this population remains controversial, with mortality rates exceeding 60% at one year. Portal hypertension poses additional challenges, including increased risks of intradialytic hypotension and potential variceal bleeding. This review synthesizes recent literature from 2021–2024 to provide current perspectives on managing this complex condition.
Keywords: hepatorenal syndrome, end-stage liver disease, cirrhosis, dialysis, portal hypertension, acute kidney injury
Introduction
The relationship between hepatic and renal function represents one of the most intricate physiological relationships in human medicine. In end-stage liver disease, kidney dysfunction emerges as a frequent and often life-threatening complication that significantly impacts patient outcomes. Among the various forms of kidney dysfunction encountered in this population, hepatorenal syndrome stands as the most challenging, representing the convergence of two major organ failures with profound implications for patient survival and management.
Hepatorenal syndrome has recently undergone substantial revision in its definition and classification. The traditional dichotomy of HRS type 1 and type 2 has been replaced with a more nuanced framework that reflects our evolving understanding of this condition's pathophysiology. This review discusses diagnosis, treatment and prognosis, incorporating the 2024 ADQI–ICA consensus alongside earlier clinical studies and reviews.
Pathophysiology: The Hepatorenal Interface
Hemodynamic Mechanisms
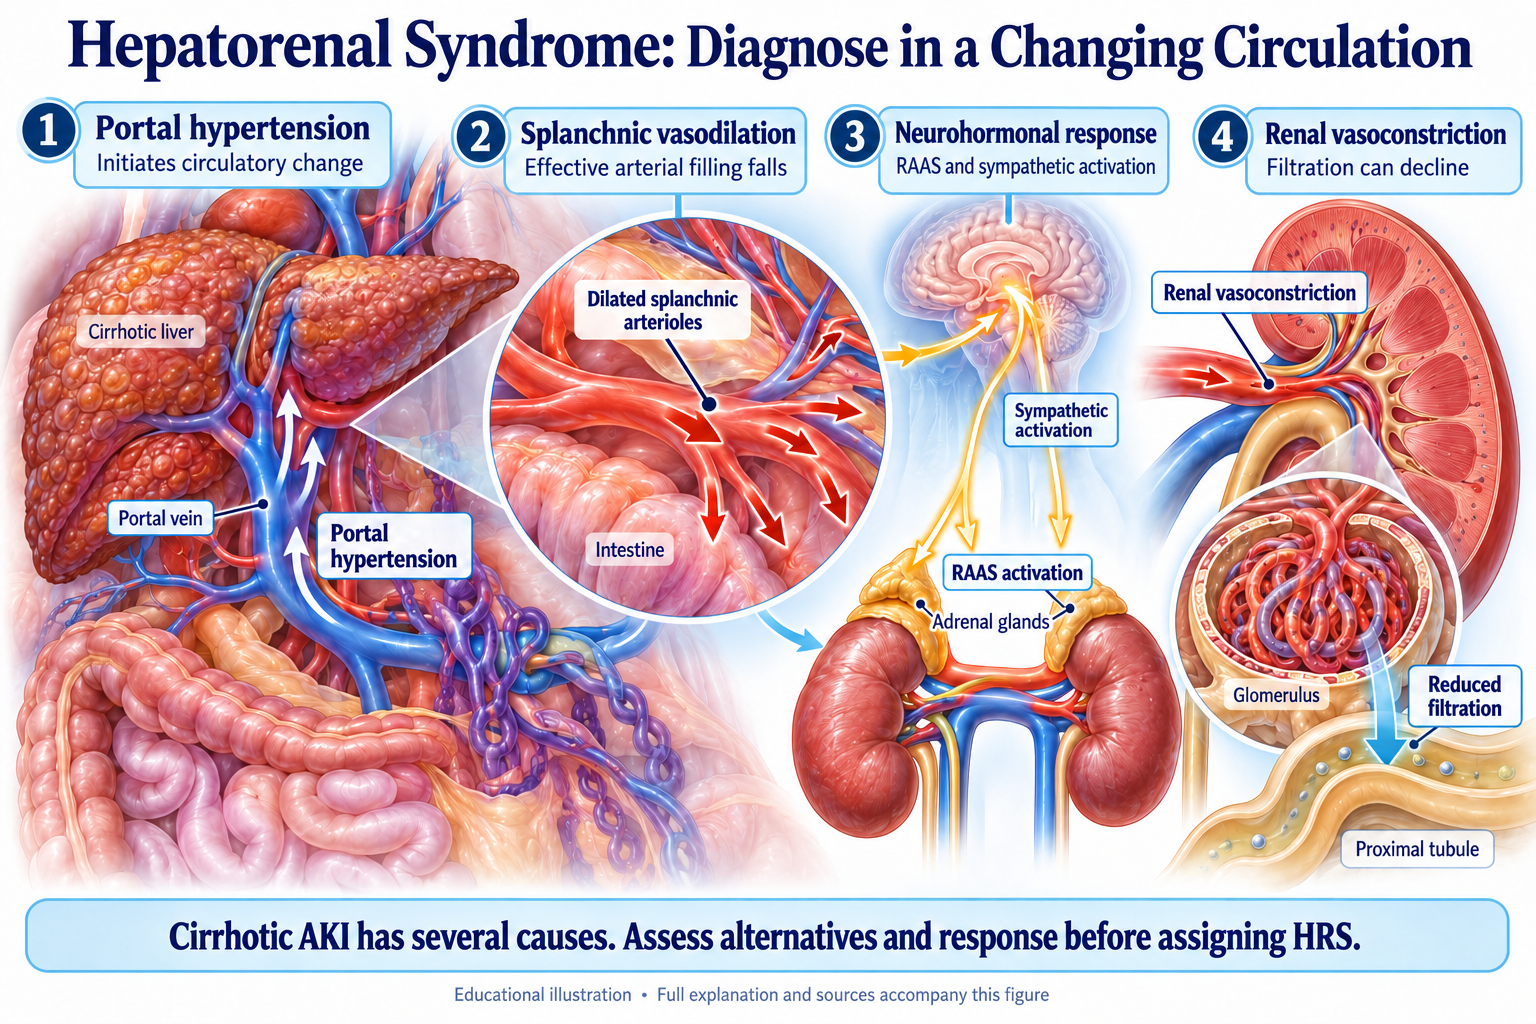
The development of kidney dysfunction in cirrhosis represents a complex interplay of hemodynamic, neurohormonal, and inflammatory processes. Portal hypertension, the hallmark of advanced cirrhosis, initiates a cascade of events that ultimately compromise renal perfusion. The primary mechanism involves splanchnic arterial vasodilation, which leads to a state of "effective hypovolemia" despite total body fluid overload.1
This hemodynamic derangement activates multiple compensatory mechanisms, including the renin-angiotensin-aldosterone system (RAAS), the sympathetic nervous system, and non-osmotic vasopressin release. While these systems initially attempt to maintain systemic blood pressure, they paradoxically result in intense renal vasoconstriction, ultimately reducing glomerular filtration rate (GFR) and renal blood flow.2
Inflammatory Component
Recent research has illuminated the role of inflammation in HRS pathogenesis. The dysregulated immune response associated with acute-on-chronic liver failure contributes to systemic inflammation, which may condition the development of extrahepatic organ dysfunction, including kidney injury.2 This inflammatory process may explain why some patients with cirrhosis develop HRS while others do not, despite similar hemodynamic profiles.
Updated Classification and Diagnostic Criteria
The Evolution of HRS Nomenclature
A paradigm shift has occurred in the classification of HRS, reflecting advances in our understanding of this condition. The International Club of Ascites (ICA) has revised its nomenclature, with HRS type 1 now designated as HRS-AKI.2 This change represents more than semantic modification; it facilitates earlier recognition and treatment initiation by eliminating arbitrary creatinine thresholds.
The current classification encompasses:
- HRS-AKI: Rapidly progressive kidney dysfunction occurring in the setting of cirrhosis
- HRS-non-AKI (HRS-NAKI): Encompasses both HRS-acute kidney disease (AKD) and HRS-chronic kidney disease (CKD)
HRS-AKI, HRS-AKD and HRS-CKD describe timing and duration. The 2024 consensus recognizes that HRS-AKI can coexist with tubular injury, proteinuria or pre-existing CKD; it is not always a purely functional process.12
Diagnostic Considerations
The 2024 ADQI–ICA framework requires cirrhosis with ascites, dynamic creatinine and/or urine-output changes, no improvement after appropriate resuscitation when indicated, and no strong alternative primary cause. Routine 48-hour albumin administration is not a mandatory diagnostic step; assess volume status and avoid fluid overload.12
Mortality and Prognostic Factors
Natural History
Dialysis Outcomes
McAllister et al. studied 7,830 USRDS patients attributed HRS as the cause of kidney failure who began maintenance dialysis in 1996–2015. Eleven percent recovered kidney function. HRS attribution was associated with lower recovery and higher one-year mortality than ATN in adjusted analyses.4
This outpatient registry cohort should not be generalized to every hospitalized patient with cirrhosis and AKI. Dialysis decisions require the illness trajectory, reversibility, transplant pathway and patient goals; an HRS label alone should not determine whether treatment is offered.5,12
Predictors of Outcomes
| Factor | Impact |
|---|---|
| Age | Younger age was associated with greater recovery in the registry cohort |
| Transplant candidacy | Transplant eligibility and severe liver disease shape prognosis and treatment options |
| Dialysis modality | Select modality using hemodynamics, treatment needs and patient context; observational comparisons do not establish causation |
Effectiveness of Dialysis: Therapeutic Considerations
Primary Medical Management
The cornerstone of HRS-AKI treatment remains pharmacological, with vasoconstrictive medications — particularly terlipressin — combined with albumin administration.3,12 Terlipressin's approval in the United States represents a significant advance, offering the first FDA-approved treatment specifically for HRS-AKI.8
Indications for Dialysis
Renal replacement therapy in HRS serves primarily as a bridging intervention rather than definitive treatment. Indications include:
- Persistent AKI with conventional kidney replacement indications and an individualized treatment plan
- Development of complications requiring urgent intervention (uremia, severe electrolyte imbalances, volume overload)
- Bridge to liver transplantation
Outcomes and Limitations
Portal Hypertension and Dialysis: Clinical Challenges
Intradialytic Hypotension
Patients with cirrhosis may have reduced effective arterial volume, limited cardiac reserve and vulnerability to intradialytic hypotension. Definitions vary, so interpret symptoms, perfusion and BP nadir together. Outpatient hemodialysis reviews identify multiple modifiable contributors, but their overall prevalence estimates are not cirrhosis-specific rates.6,7
- Baseline hemodynamic instability
- Reduced cardiac reserve
- Autonomic dysfunction
- Splanchnic vascular pooling
Variceal Bleeding Risk
The risk of variceal bleeding during dialysis in patients with portal hypertension represents a significant clinical concern. Contributing factors include:
- Hemodynamic fluctuations during dialysis
- Anticoagulation exposure when used; heparin-free or regional strategies may be appropriate
- Coexisting portal-hypertension complications requiring hepatology management10
Risk Mitigation Strategies
To minimize complications associated with dialysis in portal hypertensive patients:
- Careful assessment and gradual attainment of dry weight
- Utilization of minimal or regional anticoagulation protocols
- Continuous hemodynamic monitoring
- Environmental optimization (temperature control, appropriate dialysate composition)
- Implementation of predictive models for IDH risk assessment
Contemporary Perspectives and Future Directions
Personalized Medicine
Emerging evidence suggests significant heterogeneity in HRS presentation and outcomes, supporting the development of personalized treatment algorithms. Factors such as age, ethnicity, and underlying liver disease etiology influence both treatment response and prognosis.4
Novel Biomarkers
Research continues to focus on identifying biomarkers that enable early HRS detection and differentiation from other causes of AKI in cirrhosis; no single biomarker is a definitive stand-alone test.12 These advances may facilitate earlier intervention and improved outcomes.
Extracorporeal Support Systems
The molecular adsorbent recirculating system (MARS) represents a promising development, offering simultaneous hepatic and renal support through albumin dialysis.8 However, its role in improving HRS outcomes remains limited, requiring further validation.
Clinical Implications and Conclusion
The management of kidney disease in end-stage liver disease demands a nuanced approach that balances aggressive intervention with realistic prognostic expectations. Key considerations include:
- Early Recognition: Implementation of updated HRS-AKI diagnostic criteria facilitates timely treatment initiation
- Appropriate Therapeutic Selection: Vasoconstrictors remain first-line therapy, with dialysis reserved for specific indications
- Risk Stratification: Careful evaluation of transplant candidacy and baseline patient characteristics influences treatment algorithms
- Complication Management: Vigilant monitoring for IDH and bleeding complications is essential in patients with portal hypertension
A multidisciplinary approach involving hepatology, nephrology, and critical care specialists remains essential for optimizing outcomes while maintaining quality of life considerations. As our understanding advances, the hope is that earlier intervention and more targeted therapies will improve the dismal prognosis that currently characterizes this condition.
References
- Tiwari N, Wong F. Hepatorenal syndrome: Updates. Clin Liver Dis (Hoboken). 2023. PubMed PMID 37663551
- Kiani C, Zori AG. Recent advances in pathophysiology, diagnosis and management of hepatorenal syndrome: A review. World J Hepatol. 2023. PubMed PMID 37397940
- Loftus M, Brown RS, El-Farra NS, et al. Improving the Management of Hepatorenal Syndrome-Acute Kidney Injury Using an Updated Guidance and a New Treatment Paradigm. Gastroenterol Hepatol (N Y). 2023. PubMed PMID 37771795
- McAllister S, Lai JC, Copeland TP, et al. Renal Recovery and Mortality Risk among Patients with Hepatorenal Syndrome Receiving Chronic Maintenance Dialysis. Kidney360. 2021. PubMed PMID 35373067
- Velez JCQ. Patients with Hepatorenal Syndrome Should Be Dialyzed? PRO. Kidney360. 2021. PubMed PMID 35369012
- Davenport A. Why is Intradialytic Hypotension the Commonest Complication of Outpatient Dialysis Treatments? Kidney Int Rep. 2023. PubMed PMID 36938081
- Hamrahian SM, Vilayet S, Herberth J, et al. Prevention of Intradialytic Hypotension in Hemodialysis Patients: Current Challenges and Future Prospects. Int J Nephrol Renovasc Dis. 2023. PubMed PMID 37547077
- Jung CY, Chang JW. Hepatorenal syndrome: Current concepts and future perspectives. Clin Mol Hepatol. 2023. PubMed PMID 37050843
- Roy P, Minhaz N, Shah-Riar P, et al. A Comprehensive Systematic Review of the Latest Management Strategies for Hepatorenal Syndrome: A Complicated Syndrome to Tackle. Cureus. 2023. PubMed PMID 37680416
- Kaplan DE, Ripoll C, Thiele M, et al. AASLD Practice Guidance on risk stratification and management of portal hypertension and varices in cirrhosis. Hepatology. 2024. PubMed PMID 37870298
- Nadim MK, Kellum JA, Davenport A, et al. Hepatorenal syndrome: the 8th International Consensus Conference of the Acute Dialysis Quality Initiative (ADQI) Group. Crit Care. 2012. PubMed PMID 22322077
- Nadim MK, Kellum JA, Forni L, et al. Acute kidney injury in patients with cirrhosis: Acute Disease Quality Initiative (ADQI) and International Club of Ascites (ICA) joint multidisciplinary consensus meeting. J Hepatol. 2024. PubMed PMID 38527522
Interpreting the Evidence
The bibliography includes narrative reviews, a retrospective dialysis registry cohort, practice guidance, expert opinion and consensus recommendations. These designs answer different questions. Observational prognostic associations do not prove that dialysis or a specific prescription causes better or worse survival. The 2024 ADQI–ICA consensus is the current diagnostic framework cited here; the 2012 consensus is historical context.4,5,11,12
© Urine Nephrology Now — Clinical Mastery Series