Visual reference
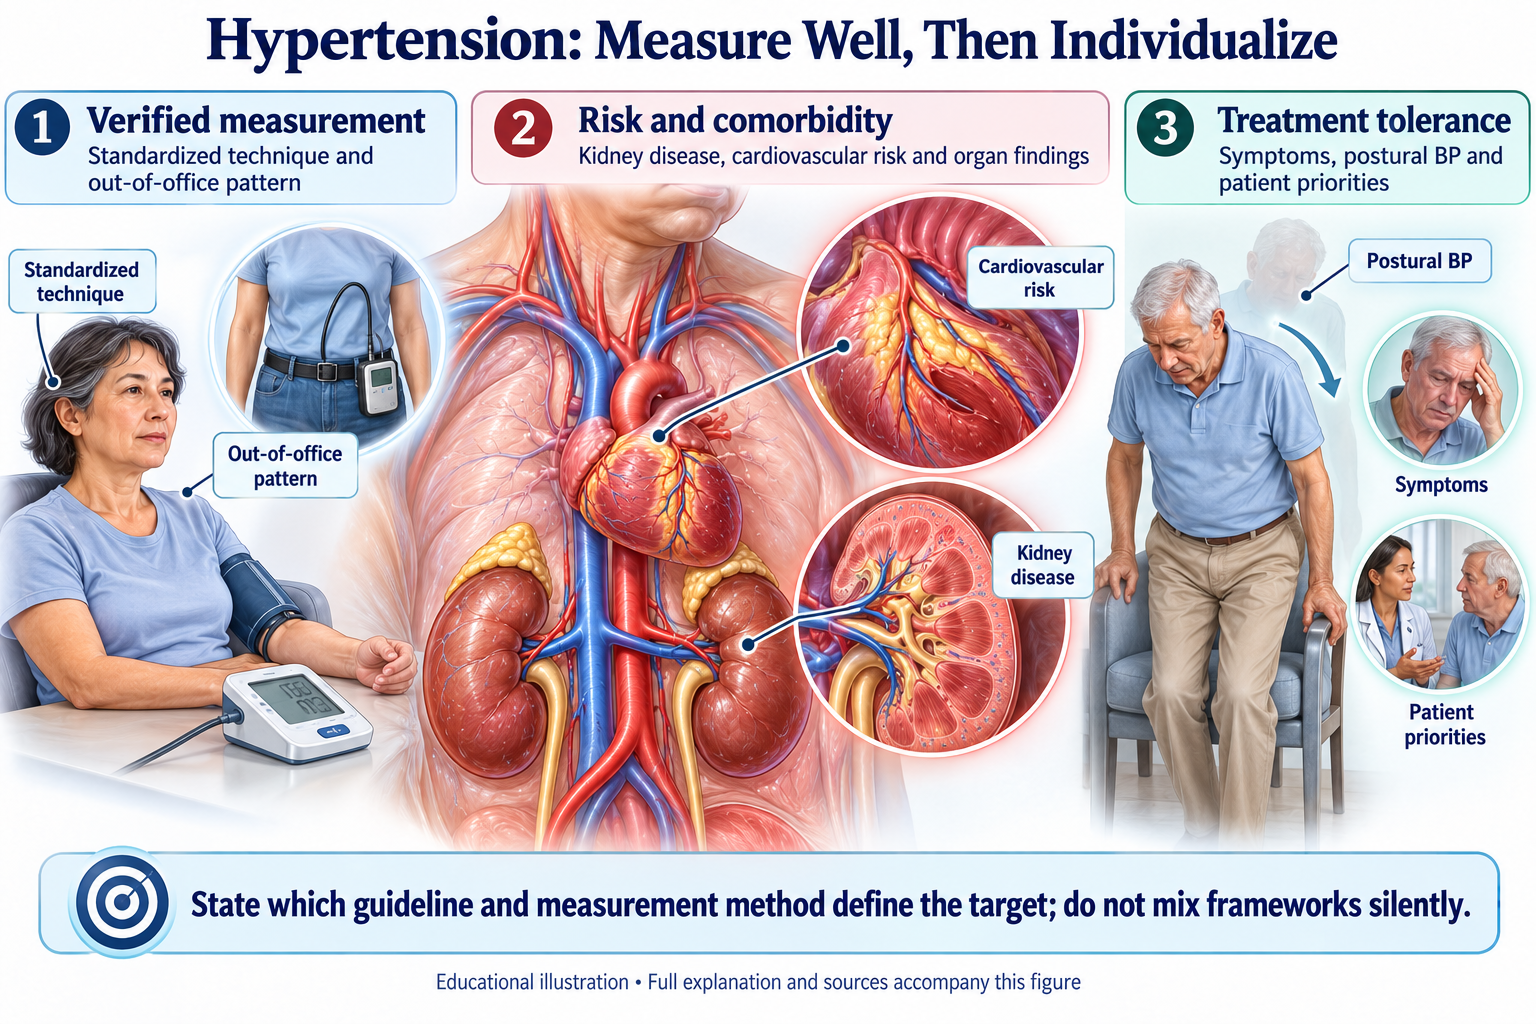
Browse the visual reference library · Download lesson Markdown
Home Blood Pressure Monitoring
Morning pre-dose readings have the strongest association with CV outcomes (HR 1.18 per 10 mmHg increase). If only one daily measurement is possible, morning pre-medication measurement is preferred.
Standardized Protocol
- 5-minute rest (reduces SBP by 4.2 mmHg vs. immediate measurement)
- Arm at heart level (each cm below heart level → +0.7–0.8 mmHg systolic)
- Appropriate cuff size (undersized cuff → falsely elevated +5.7 mmHg systolic)
- 2–3 readings 1 minute apart; discard first, average remainder
- 7-day rule: AM + PM for 7 days, discard day 1
24-Hour Ambulatory Blood Pressure Monitoring
ABPM values are more strongly predictive of CV outcomes than office or home measurements.
| Measurement Method | HR per 10 mmHg SBP |
|---|---|
| 24-hour ABPM | 1.25 (1.20–1.30) |
| Home BP | 1.19 (1.14–1.25) |
| Office BP | 1.15 (1.11–1.19) |
ABPM can screen for obstructive sleep apnea. Non-dipping pattern (sensitivity 78%, specificity 63%) combined with nocturnal HTN and high nocturnal BP variability has PPV of 83% when 3+ patterns present. A two-step algorithm (ABPM → home sleep testing) reduces unnecessary PSG by 67%.
Morning Blood Pressure Phenotypes
Isolated morning HTN prevalence: 10.8% overall, increasing to 19.6% in patients ≥75 years.
| Morning Surge >35 mmHg vs. <10 mmHg | HR (95% CI) | 5-Year ARI |
|---|---|---|
| Stroke risk | 2.27 (1.41–3.67) | 3.5% |
| Coronary events | 1.69 (1.08–2.65) | 2.2% |
| HF hospitalization | 1.83 (1.21–2.76) | 2.8% |
Cardiovascular Risk Reduction by Blood Pressure Level
Ettehad et al. (Lancet 2016; 123 trials, 613,815 participants) established the per-10-mmHg effect sizes. Each 10 mmHg reduction in SBP produces, on average:5
- 20% RRR in major CV events (RR 0.80, 95% CI 0.77–0.83)
- 17% RRR in coronary heart disease (RR 0.83, 0.78–0.88)
- 27% RRR in stroke (RR 0.73, 0.68–0.77)
- 28% RRR in heart failure (RR 0.72, 0.67–0.78)
- 13% RRR in all-cause mortality (RR 0.87, 0.84–0.91)
The proportional risk reduction per 10 mmHg drop is roughly the same whether the patient starts at 200 mmHg or 140 mmHg. Ettehad meta-regression: no significant trend by baseline SBP (all ptrend > 0.05).5 BPLTTC 2021 (48 RCTs, 344,716 participants) confirmed: per 5 mmHg SBP reduction, HR 0.91 (no prior CVD) / 0.89 (prior CVD), with no heterogeneity across seven baseline-SBP strata from <120 to ≥170.6
What varies is the absolute benefit: because event rates are much higher at 200 mmHg than at 140 mmHg, the same 20% RRR yields a larger ARR at higher baseline BP. The "law of diminishing returns" lives in ARR/NNT, not in RRR.
Modeled 5-Year ARR/NNT by Baseline SBP
The table below applies a constant approximately 20% RRR per 10 mmHg drop (Ettehad) to declining baseline 5-year MACE event rates by stratum. These ARR and NNT values are extrapolated, not measured directly — useful for shared decision-making but not a head-to-head trial result.
| Starting SBP | Target SBP | RRR per 10 mmHg | Modeled 5-yr ARR | Modeled NNT (5-yr) |
|---|---|---|---|---|
| 190–170 | 170–150 | 20% | 4.8% | 21 |
| 170–150 | 150–140 | 20% | 3.2% | 31 |
| 150–140 | 140–130 | 20% | 2.0% | 50 |
| 140–130 | 130–120 | 20% | 1.4% | 71 |
| <130 | <120 | 20% | 0.6% | 167 |
SPRINT — the Anchor Trial for Intensive Targets
SPRINT (NEJM 2015; 9,361 participants, no diabetes, SBP ≥130, high CV risk) randomized SBP <120 vs <140.7 Median follow-up 3.26 years (stopped early). Primary composite (MI, ACS, stroke, HF, CV death): HR 0.75 (0.64–0.89) — 25% RRR, ARR 1.6%, NNT 61. All-cause mortality: HR 0.73 (0.60–0.90) — 27% RRR, ARR 1.2%, NNT 90. Adverse events (hypotension, syncope, electrolyte abnormalities, AKI) significantly higher in the intensive arm.
SPRINT used standardized automated measurements; attendance varied across sites. Use standardized technique and individualized targets. There is no universal fixed conversion to routine clinic BP. Measurement methods.
ARR-Harm: Does Adverse-Event Risk Also Rise as You Push Lower?
The benefit side of BP lowering has constant RRR and shrinking ARR. The harm side moves the opposite direction: as you target lower BP, several adverse events become more common in absolute terms. SPRINT's SAE table is the cleanest direct test.7
| Serious Adverse Event | HR Intensive vs Standard | Direction |
|---|---|---|
| Hypotension | 1.67 (1.21–2.32) | ↑ harm scales with target |
| Syncope | 1.33 (1.05–1.69) | ↑ harm scales |
| Electrolyte abnormality | 1.35 (1.11–1.66) | ↑ harm scales |
| Acute kidney injury or failure | 1.66 (1.31–2.10) | ↑ harm scales |
| Injurious falls | 1.00 (0.83–1.20) | → no increase — including SPRINT-Senior ≥75y |
| Orthostatic hypotension on study visit | numerically lower in intensive arm | → no signal |
The clinical lore that "more BP lowering = more falls in the elderly" was specifically tested in SPRINT and was not supported. Injurious falls were equally common in both arms (HR 1.00), including in the pre-specified SPRINT-Senior subgroup of patients age ≥75. This does not mean falls never happen on intensive therapy — it means the trial-level signal does not support withholding intensification on falls-fear alone.
Time Course of Benefit — Years, Not Weeks
The RRR/ARR figures above are realized over years of treatment, not days or weeks. This is critical for shared decision-making and titration pace.
| Trial / Source | Median Follow-up | When Event Curves Separated |
|---|---|---|
| SPRINT (PMID 26551272) | 3.26 yr | Approximately month 12 for primary composite, accelerating through year 3 |
| ASCOT-BPLA (PMID 16154016) | 5.5 yr | Year 1 for primary composite |
| HOPE-3 | 5.6 yr | Year 2-3 for stroke benefit |
| BPLTTC IPD meta (PMID 33933205) | 4.15 yr | Anchored effect-size estimates at this window |
| Ettehad meta-analysis (PMID 26724178) | Approximately 4 yr typical | Trial-level RRRs assume this follow-up scale |
Sequence of benefit emergence: stroke first (6-12 months), CHD next, HF intermediate, all-cause mortality last (years 2-5).
For uncomplicated stage 1 or stage 2 hypertension (SBP <180), weeks to months of gradual titration is appropriate — this matches the time-scale on which the published RRR/ARR benefits are realized. There is no week-by-week catastrophic risk in asymptomatic chronic hypertension that justifies rapid pharmacologic reduction.
The only paradigms that demand faster action:
- Hypertensive emergency (SBP ≥180 with target-organ damage — papilledema, AKI, MI, stroke, eclampsia, dissection): hours to days, target 25% SBP reduction in the first hour for most; faster for aortic dissection.
- Severe HTN without TOD (SBP ≥180 without symptoms): the AHA 2025 guideline explicitly retired the term "hypertensive urgency." Outpatient titration over days to weeks is the modern standard.
Patel et al. studied outcomes of patients with hypertensive urgency in the office setting. That observational study is not a randomized trial of IV antihypertensive treatment in hospitalized patients. Distinguish asymptomatic severe hypertension from an emergency with acute target-organ injury before choosing the setting and pace of treatment.
Net-Benefit Framing — ARR-Benefit vs ARR-Harm
- ARR-benefit shrinks as baseline BP drops (smaller absolute target with constant 20% RRR).
- ARR-harm grows for hypotension, syncope, AKI, electrolyte abnormalities — but not for falls.
- Below some threshold the curves cross. ACCORD-BP in diabetics is the clearest published example of the cross: similar SAE excess to SPRINT, no CV benefit — net negative. This is why diabetes was excluded from SPRINT, and why intensive targets in diabetic patients remain contested.
- Generalizability boundary: SPRINT excluded nursing-home residents, prior stroke, dementia, and proteinuric CKD. The "no fall increase" finding does not extend to those populations — clinical judgment dominates the meta-analysis.
Pulse Pressure Considerations
Low diastolic pressure, particularly with elevated systolic pressure or established coronary disease, deserves careful assessment during treatment. In ARIC, low DBP was associated with myocardial injury and coronary events. This observational association does not prove that medication-induced lowering causes those events or define a universal safe lower limit. Consider symptoms, orthostasis, coronary disease, arterial stiffness, and the overall benefit of BP control. McEvoy et al., JACC 2016.
ACE Inhibitors vs. ARBs
Comparable BP reduction. ONTARGET (PMID 18378520) found no significant difference between ramipril, telmisartan, or both in 25,620 high-risk patients (primary composite RR 1.01, 95% CI 0.94–1.09). The two classes diverge in adverse-event profile, not in BP-lowering or CV-outcome efficacy.
Side Effect Comparison
| Adverse effect | Evidence and interpretation | Source |
|---|---|---|
| Cough | Across 22 placebo-controlled trials, cough was reported in 13.5% receiving an ACE inhibitor and 8.5% receiving placebo. The attributable fraction varied by clinical setting; evaluate alternative causes, especially in heart failure. | Vukadinović et al., 2019 |
| Angioedema | Weighted incidence was 0.30% with ACE inhibitors and 0.11% with ARBs across randomized trials; ACE inhibitor risk was higher in head-to-head comparisons. These pooled rates do not predict an individual patient's risk. | Makani et al., 2012 |
| Hyperkalemia | Both classes require potassium monitoring. A diabetic kidney disease network meta-analysis found imprecise estimates for harms, with concern for combined ACE inhibitor plus ARB therapy. Do not use it to assign a fixed class-specific incidence or infer safety of dual blockade. | Palmer et al., 2015; ONTARGET |
| Creatinine increase | In a UK cohort of new ACE inhibitor/ARB users, 1.2% of patients eligible for the monitored creatinine comparison had a rise of at least 30%. This is not an incidence estimate for all 223,814 initiators or a randomized class comparison. Assess volume status, concomitant drugs, potassium, and kidney function when a substantial change occurs. | Schmidt et al., 2017 |
Transition From an ACE Inhibitor to Sacubitril/Valsartan
Do not give an ACE inhibitor together with sacubitril/valsartan or within the 36-hour washout interval. Severe kidney impairment affects the recommended starting dose and calls for close monitoring of blood pressure, kidney function, and potassium. Entresto prescribing information.
Many ACE inhibitors accumulate with reduced kidney function, although elimination differs between agents. This pharmacokinetic observation supports drug-specific dose adjustment; it does not establish a routine fosinopril bridge or a validated longer washout schedule for all patients with CKD. Hoyer et al., 1993.
Losartan: Special Considerations
Pro-Drug and CYP2C9 Polymorphisms
Losartan requires hepatic conversion via CYP2C9 to active metabolite EXP3174, which is more potent than the parent compound. CYP2C9 poor metabolizers (homozygous variant alleles) have substantially reduced active metabolite formation, with potential impact on antihypertensive efficacy. The mechanistic basis is established in Lee CR, Goldstein JA, Pieper JA. Pharmacogenetics 2002;12(3):251-263 (PMID 11927841).
- CYP2C9*2 variant prevalence: approximately 11% in Caucasians, 3–4% in African Americans
- CYP2C9*3 variant prevalence: approximately 7–9% in Caucasians, 2–3% in African Americans
Uricosuric Properties — Corrected 2026-04-29
Losartan is unique among ARBs and ACEi in having clinically significant uricosuric properties via URAT1 inhibition. Hamada T et al. Am J Hypertens 2008 (PMID 18670416) demonstrated the URAT1-mediated mechanism in 41 patients (32 hypertensive + 9 with idiopathic renal hypouricemia) — losartan lowered serum urate; candesartan did not.
Choi HK et al. BMJ 2012;344:d8190 (PMID 22240117) — UK case-control study of 24,768 incident gout cases — reported the actual clinical effect: losartan RR 0.81 (95% CI 0.70–0.94) for incident gout, i.e., approximately 19% RRR. Effect strengthens with longer use: RR 0.71 at ≥2 years. ARR and NNT depend on baseline gout incidence and were not published as population-level figures in Choi 2012.
Interpret gout risk estimates from their actual population and comparator; do not infer a universal absolute benefit or NNT from a relative association.
Comparative context from Choi 2012: diuretics RR 2.36 (over 2x gout risk), beta-blockers RR 1.48, ACEi RR 1.24, non-losartan ARBs RR 1.29 — losartan stands alone among RAAS blockers in actually lowering gout risk.
Extended Half-Life Agents for 24-Hour Coverage
| Agent | Half-Life | Key Advantage | CKD Impact |
|---|---|---|---|
| Amlodipine | 35–50 hr | Highest T:P ratio (85–90%). Effective at 48–72 hr post-dose. | No change (90% hepatic) |
| Telmisartan | ~24 hr | Longest ARB t½. T:P 77% at 24 hr, 65% at 36 hr. | Minimal (>97% hepatic) |
| Chlorthalidone | 40–60 hr | 24-hr SBP effect 45% greater than HCTZ. | Reduced efficacy below eGFR 30 |
| Olmesartan | 12–18 hr | Highest AT1 binding affinity. Insurmountable binding. T:P ~70%. | Minimal (60% hepatobiliary) |
Thiazide-Induced Hyponatremia: Risks and Mitigation
Thiazide-induced hyponatremia (TIH) is one of the most clinically significant adverse effects of this drug class. Across observational cohorts the prevalence of any hyponatremia (Na <135) in thiazide users ranges from 4–30% depending on threshold and population studied; clinically significant hyponatremia (Na <130) is less common but meaningful, particularly in elderly patients. Severe hyponatremia (Na <125) carries appreciable mortality, especially with rapid onset or rapid overcorrection — Sonnenblick's case-series review of 129 reported cases identified 12 deaths directly related to hyponatremia.14
Risk Factors — What the Primary Source Actually Says
The canonical case-control study is Chow KM et al., QJM 2003 (PMID 14631057) — 223 hospitalized cases of symptomatic TIH vs 216 thiazide-using controls. Multivariable logistic regression identified only three independent predictors:
| Risk Factor (Chow 2003) | Effect |
|---|---|
| Each 10-year increment in age | HR 2.14 (1.59–2.88) |
| Each 5 kg increment in body weight | OR 0.77 (0.68–0.87) — lower body weight = higher risk |
| Each SD (0.84 mmol/L) increase in serum potassium | OR 0.37 (0.27–0.50) — hypokalemia = higher risk |
Thiazide-associated hyponatremia risk depends on age, body size, potassium, comorbidities, and exposures. Distinguish the independent predictors in a particular study from risk factors discussed in broader reviews. Clinical review · Mechanisms and management.
The advice to "push fluids" on thiazides is mechanistically wrong: thiazides impair urinary dilution by inhibiting the distal Na-Cl cotransporter while preserving the medullary concentration gradient, so excess water intake worsens hyponatremia rather than helping.15 The principle of avoiding excess fluid intake on thiazides is supported by:
- Mechanism (Filippone 2020 catalogues impaired free-water excretion + osmotic inactivation as core pathophysiology)
- Single-dose rechallenge data (Friedman et al. Ann Intern Med 1989, PMID 2491733) demonstrating polydipsia/weight gain after thiazide drives serum sodium decline
- Case-series observation (Sonnenblick Chest 1993, PMID 8432162) identifying excess water intake in the majority of severe TIH cases
- Management guideline (Filippone 2020 lists oral fluid restriction as a cornerstone of TIH management)
Avoid excessive fluid intake during thiazide therapy and assess individual hyponatremia risk. A universal preventive fluid-restriction regimen has not been established by the cited evidence.
Benefit vs Harm — Honest Framing
The benefit-risk equation for thiazides is favorable in most patients but inverts in specific populations. Honest framing:
- Benefit = BP reduction × baseline CV risk. Thiazides produce 8–10 mm Hg SBP reduction in adherent users. Applying the verified Ettehad 2016 per-10-mmHg RRRs (20% MACE, 27% stroke, 28% HF, 13% mortality) to a typical hypertensive's baseline event rate yields modeled 5-year ARR of 1–3% across these outcomes — useful but extrapolated.
- Harm = Hyponatremia × reported risk factors (age, low body weight, hypokalemia) plus broader-literature risk factors (female sex, SSRI/NSAID concomitancy, comorbid HF/liver/malignancy).
- Net assessment varies by population. Favorable in younger patients without risk factors. Often unfavorable in elderly women with multiple risk factors — consider non-thiazide first-line (DHP CCB, ACEi, ARB) in that subgroup. Closer monitoring (sodium at baseline, 1–2 weeks, then routinely) is reasonable when thiazide is chosen in higher-risk patients.
Key References
- Unger T, Borghi C, Charchar F, et al. 2020 International Society of Hypertension global hypertension practice guidelines. J Hypertens 2020. PubMed 32371787.
- Stergiou GS, Palatini P, Parati G, et al. 2021 European Society of Hypertension practice guidelines for office and out-of-office blood pressure measurement. J Hypertens 2021. PubMed 33710173.
- Whelton PK, Carey RM, Aronow WS, et al. 2017 ACC/AHA/AAPA/ABC/ACPM/AGS/APhA/ASH/ASPC/NMA/PCNA Guideline for the Prevention, Detection, Evaluation, and Management of High Blood Pressure in Adults: A Report of the American College of Cardiology/American Heart Association Task Force on Clinical Practice Guidelines. J Am Coll Cardiol 2018. PubMed 29146535.
- Kario K. Morning surge in blood pressure and cardiovascular risk: evidence and perspectives. Hypertension 2010. PubMed 20937968.
- Ettehad D, Emdin CA, Kiran A, et al. Blood pressure lowering for prevention of cardiovascular disease and death: a systematic review and meta-analysis. Lancet. 2016;387(10022):957-967. [PubMed]
- Blood Pressure Lowering Treatment Trialists' Collaboration (Rahimi K, et al.). Pharmacological blood pressure lowering for primary and secondary prevention of cardiovascular disease across different levels of blood pressure: an individual participant-level data meta-analysis. Lancet. 2021;397(10285):1625-1636. [PubMed]
- SPRINT Research Group. A randomized trial of intensive versus standard blood-pressure control. N Engl J Med. 2015;373(22):2103-2116. [PubMed]
- SPRINT Research Group. Final report of a trial of intensive versus standard blood-pressure control. N Engl J Med. 2021;384(20):1921-1930. [PubMed]
- ONTARGET Investigators. Telmisartan, ramipril, or both in high-risk vascular patients. N Engl J Med. 2008;358(15):1547-1559. [PubMed]
- Vukadinović D, Vukadinović AN, Lavall D, Laufs U, Wagenpfeil S, Böhm M. Rate of Cough During Treatment With Angiotensin-Converting Enzyme Inhibitors: A Meta-Analysis of Randomized Placebo-Controlled Trials. Clin Pharmacol Ther. 2019;105(3):652-660. [PubMed]
- Makani H, Messerli FH, Romero J, et al. Meta-analysis of randomized trials of angioedema as an adverse event of renin-angiotensin system inhibitors. Am J Cardiol. 2012;110(3):383-391. [PubMed] Added 2026-04-29 as primary source for ACEi/ARB angioedema rates.
- Hoyer J, Schulte KL, Lenz T. Clinical pharmacokinetics of angiotensin converting enzyme (ACE) inhibitors in renal failure. Clin Pharmacokinet. 1993;24(3):230-254. [PubMed]
- Hamada T, Ichida K, Hosoyamada M, et al. Uricosuric action of losartan via the inhibition of urate transporter 1 (URAT1) in hypertensive patients. Am J Hypertens. 2008;21(10):1157-1162. [PubMed] Date corrected 2026-04-29 from "2019".
- Choi HK, Soriano LC, Zhang Y, García Rodríguez LA. Antihypertensive drugs and risk of incident gout among patients with hypertension: population based case-control study. BMJ. 2012;344:d8190. [PubMed] Date corrected 2026-04-29 from "2021"; gout-RRR figure corrected from "25-30%" to actual 19% (RR 0.81).
- Chow KM, Szeto CC, Wong TY, et al. Risk factors for thiazide-induced hyponatraemia. QJM. 2003;96(12):911-917. [PubMed] Date corrected 2026-04-29 from "2022".
- Sonnenblick M, Friedlander Y, Rosin AJ. Diuretic-induced severe hyponatremia. Review and analysis of 129 reported patients. Chest. 1993;103(2):601-606. [PubMed]
- Filippone EJ, Ruzieh M, Foy A. Thiazide-Associated Hyponatremia: Clinical Manifestations and Pathophysiology. Am J Kidney Dis. 2020;75(2):256-264. [PubMed]
- Friedman E, Shadel M, Halkin H, Farfel Z. Thiazide-induced hyponatremia: reproducibility by single dose rechallenge and an analysis of pathogenesis. Ann Intern Med. 1989;110(1):24-30. [PubMed] Date corrected 2026-04-29 from "2022".
- Liamis G, Filippatos TD, Elisaf MS. Thiazide-associated hyponatremia in the elderly: what the clinician needs to know. J Geriatr Cardiol. 2016;13(2):175-182. [PubMed] Added 2026-04-29 as canonical TIH-in-elderly review.
- Williams B, et al. PATHWAY-2: spironolactone for resistant HTN. Lancet. 2015;386(10008):2059-2068. [PubMed]
- Williams B, Mancia G, Spiering W, et al. 2018 ESC/ESH Guidelines for the management of arterial hypertension. Eur Heart J. 2018;39(33):3021-3104. [PubMed] Date/volume/pages corrected 2026-04-29 from "2022;43(41):3420-3490".
Also on this topic
The same subject at other levels of depth.
- Lecture: 🌅 Morning Hypertension Management
- Interactive case: Outpatient Hypertension Management
- Student handout: Hypertension Management: Evidence-Based Clinical Guide