Visual reference
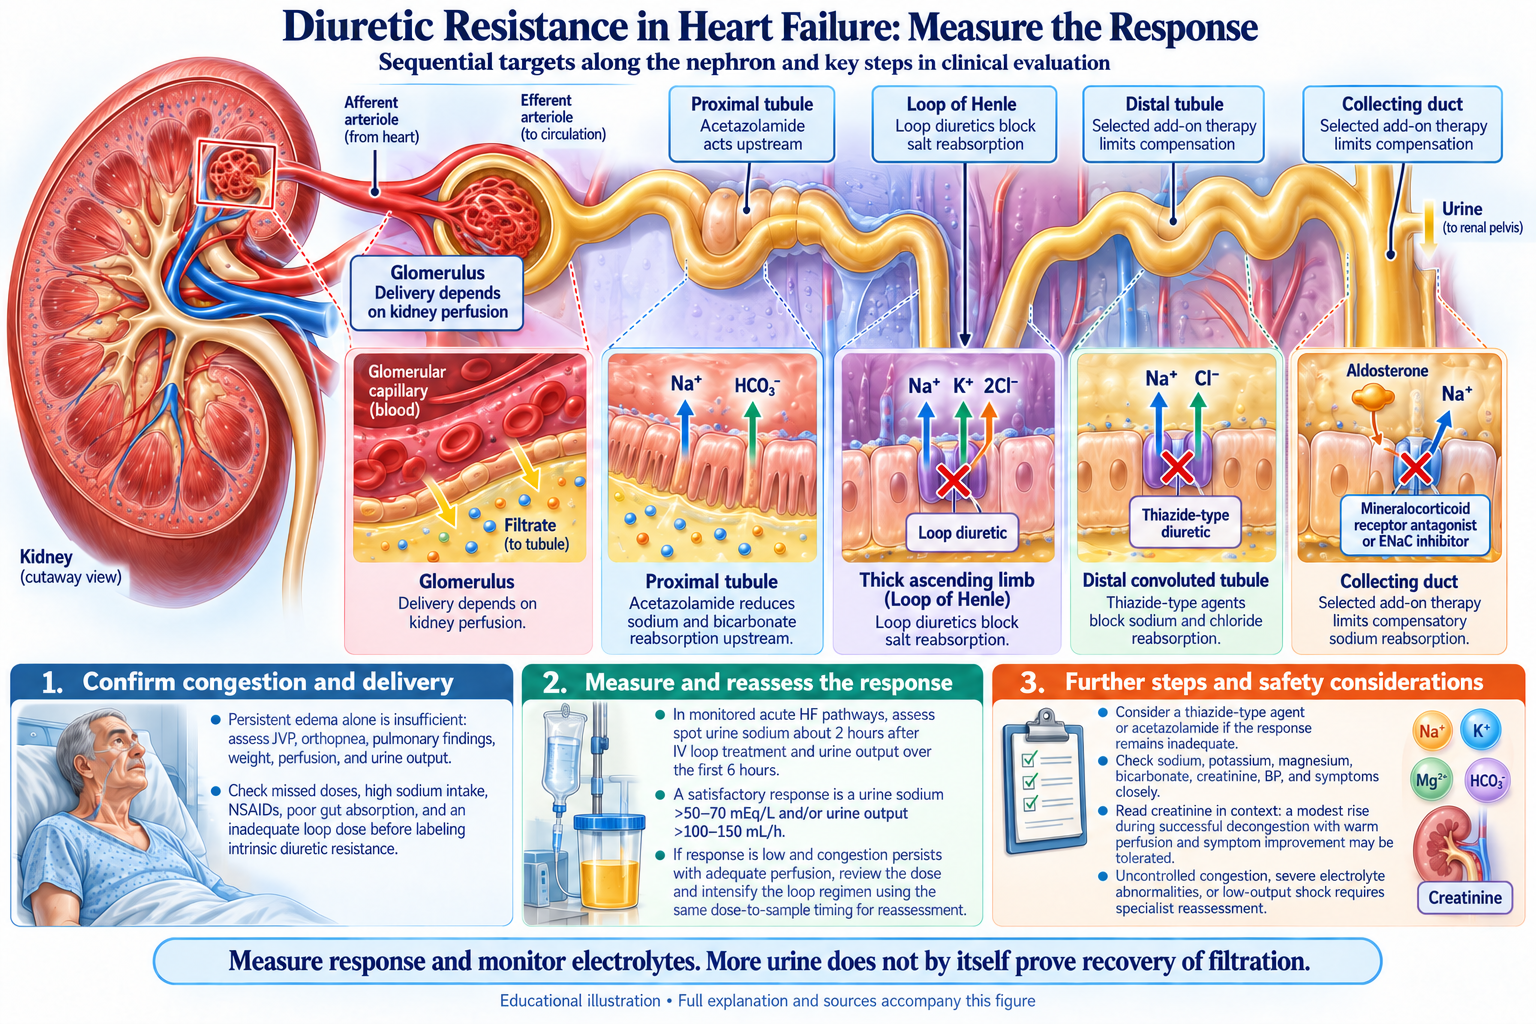
Browse the visual reference library · Download lesson Markdown
A Comprehensive Clinical Framework for Escalating Diuretic Therapy
Advanced Decongestive Strategy for Nephrology and Cardiology Practitioners
Andrew Bland, MD, FACP, FAAP
Browse the visual reference library · Download lesson Markdown
Diuretic therapy is the cornerstone of volume management in heart failure, nephrotic syndrome, hepatic cirrhosis, and chronic kidney disease. Despite being available since the 1960s, loop diuretics are used in isolation in the majority of hospitalized patients despite compelling mechanistic and emerging clinical data supporting multi-agent sequential nephron blockade (SNB). The consequence of this single-agent paradigm is startling: after 72 hours of intravenous loop diuretic therapy, approximately 85% of ADHF patients still exhibit clinical signs of congestion, and 24% experience treatment failure defined as persistent or worsening fluid overload.
SNB is built on the recognition that the nephron does not passively accept loop-diuretic–induced natriuresis. Instead, it responds with coordinated adaptive compensatory mechanisms across multiple tubular segments that offset sodium losses and perpetuate volume overload:
Each of these maladaptive responses is a pharmacologically reversible target.
Understanding SNB requires a working map of nephron segment function and diuretic site of action. Sodium reabsorption is distributed across five main functional compartments with quantifiably different contributions to total filtered-load recapture.
The PCT reabsorbs the largest share of filtered sodium, primarily via luminal carbonic anhydrase–mediated NaHCO₃ cotransport (NHE3) and SGLT2-coupled glucose-sodium uptake in the S1/S2 segments. Despite handling the majority of filtered sodium, the PCT is paradoxically the least efficient diuretic target in isolation: any sodium escaping the PCT is largely recaptured downstream.
Agents targeting this segment:
The TAL is the primary target of loop diuretics, which block the Na⁺/K⁺/2Cl⁻ cotransporter (NKCC2). This is the most potent diuretic site per milliequivalent of sodium blocked because the thick ascending limb is impermeable to water. Loop diuretics are correctly described as "high-ceiling" agents.
Agents targeting this segment:
The DCT reabsorbs sodium via the Na⁺/Cl⁻ cotransporter (NCC). Loop diuretic–induced chronic sodium delivery to the DCT drives compensatory NCC upregulation and tubular hypertrophy — the anatomical substrate for the "post-diuretic braking phenomenon."
Agents targeting this segment:
The ASDN — comprising the late DCT, connecting tubule, and cortical/medullary collecting duct — mediates sodium reabsorption via the epithelial sodium channel (ENaC), regulated primarily by aldosterone.
Agents targeting this segment:
Aquaporin-2 (AQP2) channels mediate vasopressin-regulated free water reabsorption. This segment is the target of vaptans.
Agents targeting this segment:
Before building the combination matrix, it is necessary to establish individual agent effectiveness. "Effectiveness" refers to net 24-hour natriuresis relative to a hypothetical untreated baseline (FENa typically <0.35% in edematous states with reduced EABV).
| Diuretic Class | Target Segment | Segment's Share of Filtered Na | Net Natriuretic Effect (monotherapy) | Relative Effectiveness vs. No Treatment |
|---|---|---|---|---|
| Acetazolamide | PCT (NHE3/CA) | 60–67% | Modest; FENa ~1–3%; limited by downstream rescue | ~1.5× |
| SGLT2 inhibitor | Early PCT (SGLT2) | Osmotic/glucose only (~3%) | Water diuresis > natriuresis; limited, non-durable | ~1.2–1.5× (primarily water) |
| Loop diuretic (IV) | TAL (NKCC2) | 20–25% | FENa 3–8%; net output +2–4L/day acute | ~4–6× baseline |
| Thiazide/metolazone | DCT (NCC) | 5–10% | Modest alone; FENa 1–3%; GFR-dependent | ~1.5–2× |
| K-sparing (MRA/ENaC) | ASDN (ENaC) | 2–3% | Mild (FENa 0.5–2%); powerful in hyperaldosteronism | ~1.2–1.5× |
| Tolvaptan (vaptan) | Inner MCD (AQP2) | Pure free water | Aquaresis; corrects hyponatremia; minimal Na loss | ~1.2× (aquaresis only) |
Note: Loop diuretic response (4–6× baseline) is the reference standard. All combination multipliers below are expressed relative to loop diuretic monotherapy.
Knauf and Mutschler established the theoretical and clinical foundations of SNB, demonstrating that the major mechanism of resistance was excessive proximal tubular sodium reabsorption, addressable by coadministering carbonic anhydrase inhibitors. The principle: low-dose combination therapy targeting multiple segments is more effective and safer than high-dose monotherapy.
This is the best-studied SNB combination. Loop diuretics deliver a heightened sodium load to the DCT; DCT hypertrophy creates a compensatory "distal sodium conservation" loop. Thiazide blockade intercepts this compensation directly.
| Combination | Segments Blocked | Relative Effectiveness vs. Loop Alone | Key Complication Risk |
|---|---|---|---|
| Loop alone | TAL | 1.0× (reference) | Hypokalemia, metabolic alkalosis |
| Loop + Metolazone | TAL + DCT | ~2–4× | Profound hypokalemia, hypomagnesemia, AKI |
| Loop + Chlorothiazide (IV) | TAL + DCT | ~2–3× | Same as above; rapid onset |
The ADVOR trial (n=519) is the only large RCT of proximal SNB. IV acetazolamide 500 mg daily added to standardized IV loop diuretics achieved successful decongestion in 42.2% vs. 30.5% (RR 1.46, 95% CI 1.17–1.82; p<0.001). Patients with baseline HCO₃ ≥27 mmol/L showed greater benefit (OR 2.39).
| Combination | Segments Blocked | Relative Effectiveness vs. Loop Alone | Notes |
|---|---|---|---|
| Loop + Acetazolamide | PCT + TAL | ~1.5× (decongestion probability) | Especially effective with metabolic alkalosis (HCO₃ ≥27) |
| Specific natriuretic gain | — | ~25–40% more natriuresis vs. loop alone | Per ADVOR secondary endpoints |
K-sparing agents add modest incremental natriuresis but serve critical roles in electrolyte preservation, aldosterone antagonism, and anti-fibrosis. In the PHARES trial, SNB with furosemide + spironolactone + amiloride produced markedly greater blood pressure reduction than combined RAAS blockade in resistant hypertension.
| Combination | Segments Blocked | Relative Effectiveness vs. Loop Alone | Notes |
|---|---|---|---|
| Loop + Spironolactone | TAL + ASDN | ~1.2–1.5× | Greatest benefit in hyperaldosteronism; slower onset |
| Loop + Amiloride | TAL + ASDN | ~1.2–1.4× | Faster onset (hours); potassium-sparing |
| Loop + Eplerenone | TAL + ASDN | ~1.2–1.4× | Selective MRA; less gynecomastia |
SGLT2 inhibition produces glucosuria with complex sodium and water responses. EMPULSE met a hierarchical composite endpoint incorporating death, HF events and symptoms in clinically stable hospitalized patients; it was not designed to establish an isolated mortality reduction. These agents complement, rather than replace, loop-based decongestion. EMPULSE; renal physiology review.
| Combination | Segments Blocked | Relative Effectiveness vs. Loop Alone | Notes |
|---|---|---|---|
| Loop + SGLT2i | TAL + early PCT (osmotic) | ~1.2–1.3× natriuresis; ~1.3–1.5× urine volume | Water diuresis > Na diuresis; durable long-term cardioprotection |
| Key Clinical Role | — | Reassess loop dose using congestion and tolerance; no fixed reduction applies to every patient | Not a primary inpatient escalation agent |
As additional nephron segments are blocked, there are two countervailing forces: (1) incrementally greater net natriuresis as compensatory reabsorption is disabled; and (2) diminishing marginal returns because each additional segment contributes less filtered sodium. Importantly, full nephron blockade shifts urine composition toward a plasma-like isotonic solution — this is the physiologic rationale for SNB safety as well as efficacy.
This combination targets three sequential segments and is arguably the most rational escalation from the ADVOR framework. Estimated relative effectiveness: ~3–5× loop alone.
| 3-Agent Combination | Segments | Estimated Multiplier vs. Loop | Key Complications |
|---|---|---|---|
| Loop + Acetazolamide + Metolazone | PCT + TAL + DCT | ~3–5× | Metabolic acidosis + hypokalemia, AKI |
| Loop + Metolazone + Spironolactone | TAL + DCT + ASDN | ~2.5–4× | K-sparing mitigates thiazide effect |
| Loop + Acetazolamide + Spironolactone | PCT + TAL + ASDN | ~2–3× | Metabolic acidosis; potassium effect depends on baseline |
| Loop + SGLT2i + Metolazone | Early PCT + TAL + DCT | ~2.5–4× | AKI risk; DKA risk with SGLT2i in sick patients |
| Loop + SGLT2i + Acetazolamide | PCT + TAL (early PCT) | ~2–3× | Both act proximally; limited evidence |
| Loop + SGLT2i + Spironolactone | PCT + TAL + ASDN | ~1.8–2.5× | Lower AKI risk; reasonable outpatient maintenance |
The most commonly employed practical triple regimen. The MRA or amiloride is essential for electrolyte preservation. Estimated effectiveness: ~2.5–4× loop alone.
Four-agent SNB is the domain of the advanced heart failure inpatient unit or the cardiorenal ICU, implying blockade of four distinct nephron segments.
| 4-Agent Combination | Segments Blocked | Estimated Multiplier vs. Loop | Key Monitoring Requirements |
|---|---|---|---|
| Loop + Acetazolamide + Metolazone + Spironolactone | PCT + TAL + DCT + ASDN | ~4–7× | Acid-base (q12h), K, Mg, Cr (q24h); strict I/O; telemetry |
| Loop + SGLT2i + Acetazolamide + Metolazone | Early PCT + TAL + PCT + DCT | ~3.5–6× | DKA risk; acidosis risk; close glucose monitoring |
| Loop + SGLT2i + Metolazone + Spironolactone | Early PCT + TAL + DCT + ASDN | ~3–5× | Well-tolerated relative to acetazolamide-containing regimens |
| Loop + Acetazolamide + Metolazone + Tolvaptan | PCT + TAL + DCT + MCD | ~4–6× (+ free water clearance) | Hyponatremia overcorrection risk; hepatotoxicity |
Five-agent SNB represents the closest achievable approximation to total nephron blockade.
| 5-Agent Combination | Estimated Multiplier vs. Loop | Clinical Context |
|---|---|---|
| SGLT2i + Acetazolamide + Loop + Metolazone + Spironolactone | ~5–10× | Advanced HF, pre-ultrafiltration trial; intensive monitoring mandatory |
| As above + Tolvaptan (6th agent) | ~6–10× with aquaretic component | Hyponatremia + congestion phenotype; hepatotoxicity risk |
Hypertonic saline (HS) concurrently with high-dose loop diuretics counteracts the paradox of the volume-overloaded patient with reduced EABV. The mechanism: bolus HS mobilizes fluid from interstitial to intravascular compartment through osmotic forces, restoring renal perfusion and improving diuretic delivery.
A 2014 meta-analysis (n=1,032) demonstrated a 44% reduction in all-cause mortality (RR 0.56, 95% CI 0.41–0.76; p=0.0003) and a 50% reduction in HF rehospitalization (RR 0.50, 95% CI 0.33–0.76; p=0.001).
HS functions not as a direct nephron-segment blocker but as a pharmacokinetic enhancer of loop diuretics — a "Segment 0" intervention that potentiates all subsequently administered agents.
Estimated contribution: ~2–3× urine output vs. loop alone in diuretic-resistant patients.
| HS Protocol Component | Details |
|---|---|
| Concentration | 3% NaCl (150 mEq/100 mL) |
| Dose | 150 mL over 30 minutes (Testani/Griffin protocol) |
| Timing | Simultaneous with or immediately before high-dose IV loop |
| Setting | CICU or cardiac step-down; central venous access preferred |
| Monitoring | Serial Na, osmolality, BMP q6–12h; strict I/O; neurological check |
| Contraindications | Serum Na >145 mEq/L; active pulmonary edema not yet responding (relative); severe uncontrolled HTN |
Metabolic alkalosis is a frequently underrecognized co-conspirator in diuretic resistance. Alkalosis drives proximal tubular NaHCO₃ reabsorption, creating a cycle: alkalosis → increased proximal Na reabsorption → more renal Na retention → more alkalosis.
IV sodium bicarbonate serves two roles in SNB:
Clinical indication: Serum HCO₃ >30 mEq/L with diuretic resistance. Protocol: 150 mEq in 1L D5W at 1–2 mL/kg/hr. Estimated diuretic contribution: ~1.1–1.3× loop alone.
The DOSE trial (Felker et al., NEJM 2011) randomized 308 ADHF patients in a 2×2 factorial design. Results:
The fundamental limitation of escalating furosemide drip rate is that loop diuretics act on only one segment (TAL, ~25% of filtered Na). At the ceiling dose, every additional milligram is wasted. SNB disassembles the compensatory architecture itself.
| Strategy | Segments Targeted | Net Natriuretic Potential | Complication Profile | Evidence Quality |
|---|---|---|---|---|
| Furosemide bolus (low dose) | 1 (TAL) | ~4× baseline | Hypokalemia, alkalosis; mild AKI | High (DOSE RCT) |
| Furosemide drip (escalating) | 1 (TAL) | ~4–5× baseline (marginal) | Similar; theoretical ototoxicity | High (DOSE); no mortality benefit |
| Loop + Metolazone | 2 (TAL + DCT) | ~8–16× baseline | Severe electrolyte loss; AKI | Moderate |
| Loop + Acetazolamide | 2 (PCT + TAL) | ~6× baseline; 46% more decongestion | Metabolic acidosis; well-tolerated | High (ADVOR) |
| Loop + Metolazone + Spiro | 3 (TAL + DCT + ASDN) | ~10–20× baseline | Moderate; K-sparing mitigates risk | Moderate |
| Loop + AZA + Metolazone | 3 (PCT + TAL + DCT) | ~12–20× baseline | Acidosis + electrolyte depletion | Low (mechanistic) |
| 4-segment blockade | PCT + TAL + DCT + ASDN | ~20–40× baseline (estimated) | High; ICU-level monitoring | Very low |
| 5-segment blockade | All major segments | Approaching CRRT-equivalent | Very high | Expert opinion |
| Hypertonic saline + loop | "Segment 0" + TAL | ~2–3× loop alone in resistant patients | Hypernatremia, pulmonary fluid shifts | Moderate (meta-analysis) |
Oral furosemide bioavailability ranges from 10% to 90%, with an average of ~50% in euvolemic patients but substantially less in decompensated heart failure due to bowel wall edema. Because loop diuretics require a minimum plasma concentration threshold to trigger natriuresis, slow and erratic absorption may mean the drug never crosses this threshold despite adequate dosing.
Torsemide is the pharmacokinetically rational oral loop diuretic: bioavailability 80–100%, half-life ~6 hours, absorption unaffected by bowel edema, and IV-to-oral equivalency of 1:1. A meta-analysis (n=19,280) demonstrated significantly greater functional class improvement (NNT=5) and fewer HF hospitalizations (10.6% vs. 18.4%; OR 0.72).
| Setting | Route/Drug | Bioavailability | Onset | Peak Effect | Key Limitation |
|---|---|---|---|---|---|
| Outpatient | PO Furosemide | 10–90% (avg ~50%) | 30–60 min | 60–120 min | Bowel edema reduces absorption |
| Outpatient | PO Torsemide | 80–100% | 30–60 min | 60–90 min | Hepatic metabolism (variable in decompensation) |
| Outpatient | PO Bumetanide | ~80% | 30–60 min | 60–120 min | Short duration |
| Inpatient | IV Furosemide (bolus) | 100% | 5–15 min | 30–60 min | Braking phenomenon; trough-driven Na retention |
| Inpatient | IV Furosemide (drip) | 100% | 5–15 min | Sustained | No superiority to bolus; complex nursing |
| Inpatient | IV Chlorothiazide | 100% | 15–30 min | 30–60 min | Add-on only; not primary |
| Inpatient | IV Acetazolamide + IV Loop | 100% | 15–30 min | 60–90 min | Metabolic acidosis; temporary |
The transition from inpatient IV to outpatient oral diuretics is a critical failure point. Patients discharged on oral furosemide at the same milligram dose will receive approximately half the effective drug dose in bioavailability-equivalent terms.
Practical strategies:
Loop diuretic efficacy is progressively impaired in CKD. CKD patients with GFR <30 mL/min may require furosemide doses of 200–400 mg IV to achieve the same response as 40 mg IV in normal kidney function. Metolazone retains efficacy at GFR as low as 10–15 mL/min, making it the thiazide of choice for SNB in advanced CKD.
Nephrotic syndrome creates a unique pharmacokinetic barrier: intraluminal protein binds furosemide in the tubular lumen, reducing the free (pharmacologically active) fraction. Loop + thiazide SNB remains effective and is the preferred escalation strategy.
CRS Type 1 (acute HF causing AKI) and Type 2 (chronic HF causing CKD) are settings where aggressive decongestion improves renal outcomes despite transient creatinine rise — the "azotemia-decongestion paradox." SNB is appropriate even when creatinine rises modestly (≤0.3–0.5 mg/dL from baseline).
Post-transplant patients on calcineurin inhibitors are particularly susceptible to hyperkalemia with K-sparing agents. Amiloride is preferred over spironolactone due to more predictable potassium kinetics. Acetazolamide is useful in post-transplant metabolic alkalosis.
The case rested on two pharmacokinetic arguments: (1) maintaining plasma levels above the natriuretic threshold continuously, and (2) avoiding high-concentration bolus-driven neurohormonal activation surges. Both arguments are physiologically coherent. The problem is they did not survive clinical testing.
The DOSE trial (Felker et al., NEJM 2011; PMID 21366472): 308 patients, 2×2 factorial, 26 centers.
High-dose (2.5× home oral dose) produced greater net fluid loss, weight loss, more dyspnea relief, and a trend toward better symptom score (p=0.06). Practical translation: when a patient is not responding, the correct first move is to increase the IV dose — not switch to an infusion at the same dose.
| Parameter | IV Bolus (q12h) | Continuous Infusion | Evidence |
|---|---|---|---|
| Symptom improvement (VAS AUC) | 4236 ± 1440 | 4373 ± 1404 (p=0.47) | Tier 1: RCT |
| Creatinine change at 72h | +0.05 mg/dL | +0.07 mg/dL (p=0.45) | Tier 1: RCT |
| Net volume loss at 72h | 4237 mL | 4249 mL (p=0.89) | Tier 1: RCT |
| Treatment failure rate | 38% | 39% (NS) | Tier 1: RCT |
| Weight reduction (meta) | Reference | +0.70 kg advantage (p=0.02) | Tier 1: Meta |
| 24h urine output advantage | Reference | +461 mL/24h (p<0.01) | Tier 1: Meta |
| 60-day mortality/rehosp | No difference | No difference | Tier 1: RCT |
| Hospital length of stay | No difference | No difference | Tier 1: RCT + Meta |
| Ototoxicity risk | Standard | Theoretical reduction (unproven) | Tier 3: Inference |
| Nursing complexity/cost | Lower | Higher (pump, dedicated line) | Tier 3: Expert opinion |
| Segments targeted | 1 (TAL) | 1 (TAL) | Fixed |
A critical distinction: the DOSE trial did not test 40 mg/hour infusions. The high-dose arm delivered roughly 200 mg IV/day — approximately 8 mg/hour. The conclusion "drip is equivalent to bolus" applies to 6–8 mg/hour, not 40 mg/hour.
When a patient fails at 10–20 mg/hour and responds promptly to 40 mg/hour, this is a dose-threshold phenomenon, not a route effect. The drip at 40 mg/hour is a vehicle for delivering a substantially higher total dose per unit time.
When the loop diuretic blocks the TAL, the nephron activates compensatory reabsorption at the DCT and ASDN. In a healthy person, this compensation is appropriate. In the volume-overloaded patient, it is the mechanism of diuretic resistance. When a thiazide blocks the DCT, it allows the full upstream natriuretic effect of the loop diuretic to manifest. The net result is substantially greater than the DCT's baseline 5–10% segment contribution would suggest, because it is freeing the loop diuretic's effect from its primary compensatory constraint.
| Strategy | Segments Blocked | Est. Natriuresis vs. IV Bolus | Decongestion Probability Shift | Key Complications | Evidence |
|---|---|---|---|---|---|
| IV Furosemide Bolus | TAL | 1.0× (reference) | 15% achieve full decongestion at 72h | Hypokalemia, metabolic alkalosis, braking phenomenon | Tier 1: DOSE RCT |
| Furosemide Drip (equivalent dose) | TAL | ~1.0–1.05× | Not significantly different from bolus | Same; +nursing complexity | Tier 1: DOSE + Meta |
| Furosemide Drip (escalated rate) | TAL | ~1.1–1.3× | Modestly improved if underdosed at baseline | AKI, ototoxicity at very high rates | Tier 2 |
| Drip + Metolazone | TAL + DCT | ~2–4× | Meaningful improvement in resistant patients | Severe hypokalemia, hypomagnesemia, AKI | Tier 2 |
| Drip + Acetazolamide | PCT + TAL | ~1.5× decongestion; ~1.3–1.4× natriuresis | 42.2% vs. 30.5% (ADVOR); RR 1.46 | Metabolic acidosis; well-tolerated | Tier 1: ADVOR RCT |
| Drip + K-Sparing Agent | TAL + ASDN | ~1.2–1.5× | Modest natriuresis; prevents hypokalemia | Hyperkalemia if not monitored | Tier 2 |
| Drip + SGLT2i | Early PCT + TAL | ~1.2–1.3× natriuresis; ~1.3–1.5× volume | Modest acute; durable chronic HF reduction | Osmotic diuresis; DKA risk; euglycemic DKA | Tier 2 |
| Drip + Metolazone + Spiro (3 segments) | TAL + DCT + ASDN | ~2.5–4× | Substantial | Moderate; manageable with monitoring | Tier 2–3 |
| Drip + AZA + Metolazone (3 segments) | PCT + TAL + DCT | ~3–5× | High; most potent evidence-anchored 3-agent | Metabolic acidosis + electrolyte depletion; ICU | Tier 2–3 |
| Drip + AZA + Meto + Spiro (4 segments) | PCT + TAL + DCT + ASDN | ~4–7× | Very high in refractory patients | Severe; telemetry, q12h BMP, strict I/O | Tier 3 |
| Full 5-segment blockade | All major segments | ~5–10× (approaching hemofiltration) | Near-maximal pharmacologic decongestion | Very high; ICU mandatory; reconsider UF | Tier 3 |
| Hypertonic Saline + Drip | "Segment 0" + TAL | ~2–3× in diuretic-resistant patients | Rescues pharmacokinetic platform | Hypernatremia; neurological risk | Tier 2 |
| HS + Drip + AZA + Meto | "Segment 0" + PCT + TAL + DCT | ~6–10× in diuretic-resistant | Highest achievable short of RRT | All combined; ICU-only strategy | Tier 3 |
The 3-, 4-, and 5-agent multipliers are constructed by applying the additive-with-compensation principle iteratively from Tier 1 and Tier 2 anchors. They are not invented; they are derived. But they have not been directly measured in a controlled trial.
Early urine sodium and urine output can help assess response to an IV loop diuretic in acute heart failure. ESC guidance describes a spot sample around two hours after dosing as one part of reassessment. Interpret concentration alongside urine volume, dose, timing, congestion, blood pressure, kidney function and electrolyte trends. ESC guidance.
A low urine sodium suggests limited sodium excretion in context, but cannot quantify proximal reabsorption, diagnose NHE3 or NCC upregulation, or select acetazolamide versus a thiazide by itself. A high value does not independently diagnose tubular injury or exclude a low total sodium output. Diuretics, GFR, water handling and collection timing affect the result.
| Finding | Next assessment |
|---|---|
| Low early urine sodium with persistent congestion | Review loop dose and delivery, urine volume, perfusion and adherence. Consider an adjusted diuretic strategy using the whole clinical picture. |
| Apparently adequate concentration but little urine | Estimate actual sodium excretion and assess kidney function and perfusion; concentration alone may mislead. |
| Glucosuria or other osmotic diuresis | Distinguish water output from sodium removal. An SGLT2 inhibitor does not automatically invalidate the measurement. |
| Hypotension, worsening perfusion or important electrolyte disturbance | Reassess the treatment goal and underlying problem before adding further diuretics. |
Serial urine-sodium studies and DIURESIS-AHF describe associations with decongestion and prognosis. They do not validate a rigid urine-sodium map of tubular transport or an automatic drug-selection algorithm. Serial measurements; DIURESIS-AHF.
Loop diuretics can help manage fluid overload in AKI when a diuretic response remains. They do not reverse tubular injury or provide a proven kidney-recovery benefit. Experimental oxygen-demand or cast-clearance mechanisms should not be presented as established clinical cytoprotection. Assess perfusion and volume status before treatment.
The furosemide stress test has been studied to estimate progression risk in selected patients with early AKI. A poor response increases concern for severe AKI; a response does not confirm normal tubular viability or guarantee that dialysis will be unnecessary. Use a standardized local protocol with appropriate volume and hemodynamic assessment. Original study; systematic review.
LIBERATE-D enrolled hemodynamically stable patients who had already started kidney replacement therapy for AKI. It compared dialysis triggered by specified clinical/metabolic indications with conventional scheduled dialysis. Recovery at discharge was 64% versus 50% in the unadjusted comparison; the prespecified adjusted estimate was uncertain and crossed no effect. A larger trial was recommended. Liu et al., JAMA 2026.
The study did not test starting furosemide to prevent initial dialysis, did not validate an FST-selected dialysis-avoidance protocol, and did not prove that withholding indicated dialysis repairs injured kidneys.
| Situation | Clinical interpretation |
|---|---|
| AKI with fluid overload | Use diuretics when appropriate and reassess the response, perfusion and electrolytes. |
| Persistent oliguria or poor FST response | Investigate the cause, follow the trajectory and prepare for possible kidney support; the test alone is not an indication. |
| Stable patient already receiving AKI dialysis | Reassess ongoing need and recovery using clinical/metabolic criteria and specialist oversight. |
| Refractory electrolyte/acid-base disturbance, pulmonary edema or uremic complications | Do not delay indicated kidney replacement therapy to pursue a diuretic response. |
This review was prepared for clinical education purposes. Not intended as a substitute for individualized clinical judgment.
Andrew Bland, MD, FACP, FAAP