CKD Mineral-Bone Disorder (CKD-MBD): Pathophysiology & Management
Visual reference
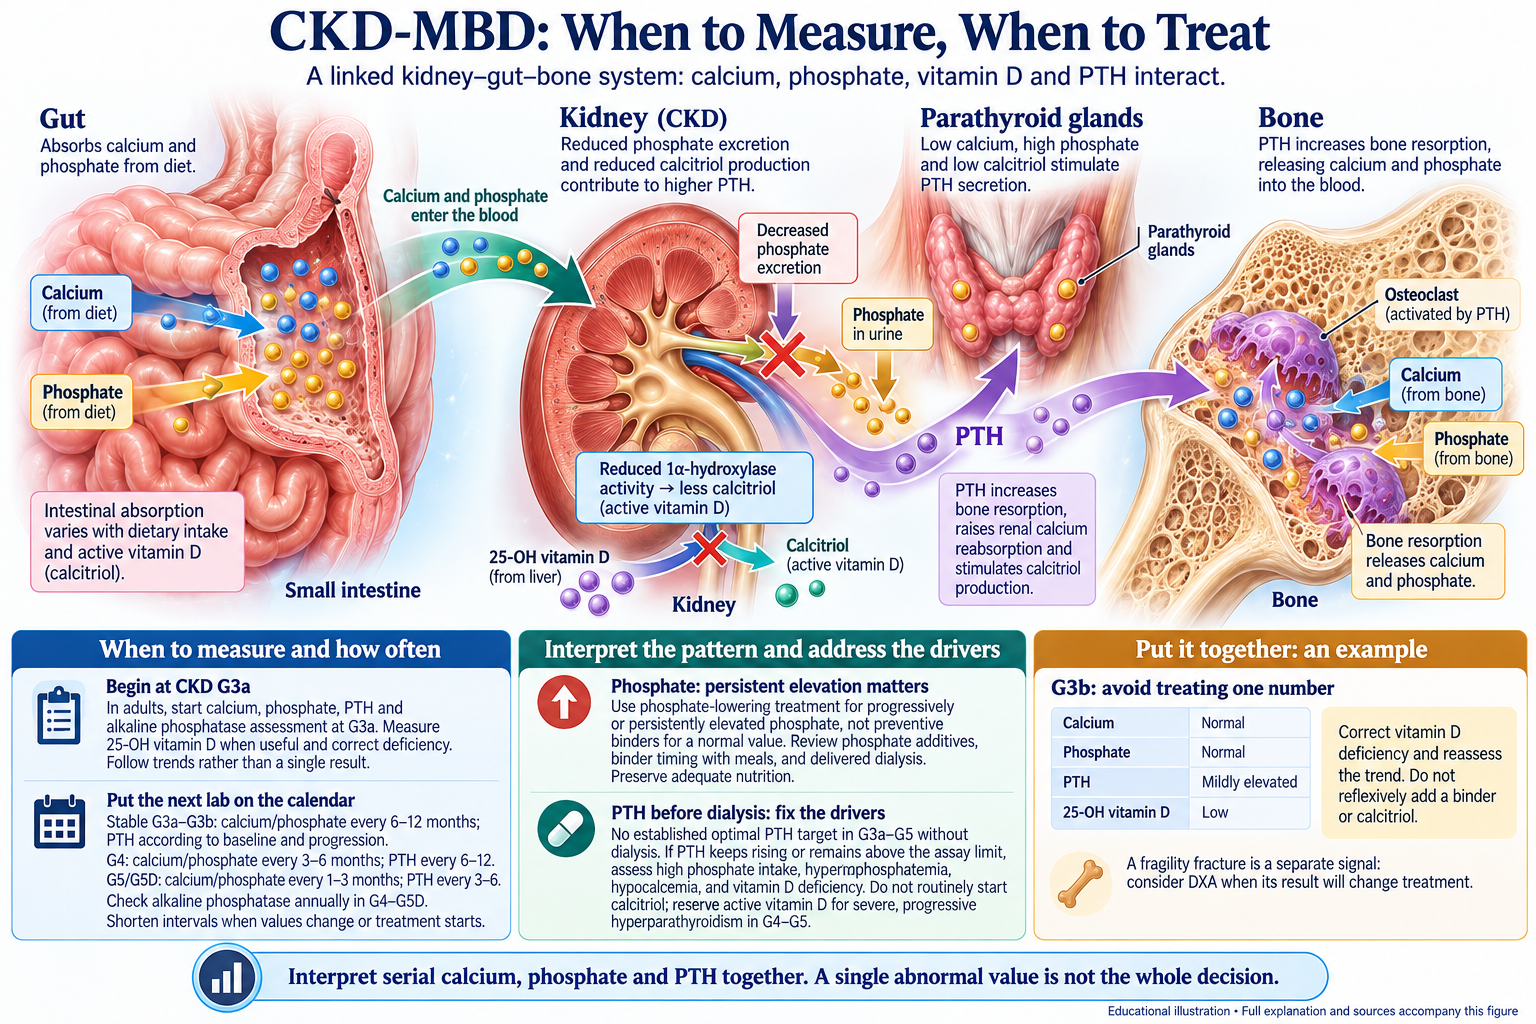
Browse the visual reference library · Download lesson Markdown
Definition & Scope
CKD-MBD is a systemic disorder of mineral homeostasis characterized by: 1. Abnormalities in calcium, phosphate, PTH, vitamin D metabolism 2. Bone disease (abnormal turnover, mineralization, or volume) 3. Vascular and soft-tissue calcification
Present in ~80% of CKD G3b–G5; major driver of cardiovascular mortality in ESRD.
CKD-MBD is NOT just “renal osteodystrophy” — includes vascular calcification, myocardial calcification, and systemic effects of abnormal mineral metabolism.
Pathophysiology: The Phosphate-FGF23-PTH-Vitamin D Axis
Phase 1: Early CKD (G3a, eGFR 45–59)
Trigger: Nephron loss → ↓ filtered load of phosphate
Compensatory response: 1. FGF23 ↑↑ (fibroblast growth factor 23) - Secreted by osteoblasts/osteocytes in response to ↓ GFR + ↑ phosphate - Early marker of dysregulation; may ↑ before serum PO4 rises - Suppresses PTH, ↑ FGF23-mediated phosphate excretion - Inhibits 1,25-(OH)2 vitamin D (active vitamin D) synthesis
- PTH rises slightly (phosphate retention drives PTH)
- ↑ Serum PTH → ↑ phosphate excretion per remaining nephron
- Net effect: Serum PO4 stays NORMAL for longer
- Serum phosphate remains NORMAL (~3.5–4.5 mg/dL)
Clinical pearl — Early CKD: FGF23 and PTH may rise while phosphate remains normal. This supports appropriate monitoring and assessment of modifiable factors, not prophylactic phosphate binders.
Phase 2: Moderate-to-Advanced CKD (G3b–G4, eGFR 15–44)
Worsening phosphate retention: - More nephrons lost → even with ↑↑ FGF23, phosphate accumulates - Serum phosphate begins to rise (>4.5 mg/dL)
PTH escalation: - Combines effects of: hyperphosphatemia + ↓ 1,25(OH)2 vitamin D (low calcium) + persistent FGF23 - PTH ↑↑↑ (may exceed 100 pg/mL)
Vitamin D metabolism disrupted: - ↓ 1,25-(OH)2 vitamin D (active form) - Normally produced by proximal tubule with FGF23 suppression - FGF23 ↑↑ → ↓↓ 1,25(OH)2D synthesis - ↓ 1,25(OH)2D → ↓ intestinal calcium absorption → ↓ serum Ca → ↑ PTH (vicious cycle)
- ↑ 25-OH vitamin D may be normal — stored form less affected (but may be low from poor nutrition/sun exposure)
Result: Secondary hyperparathyroidism (2° HPT) — PTH elevated due to CKD-induced stimuli
Phase 3: Advanced CKD & ESRD (G5, eGFR <15)
Overt hyperphosphatemia: PO4 >5 mg/dL
Tertiary hyperparathyroidism: PTH becomes autonomous - Even if phosphate, calcium normalize, PTH remains ↑ (from years of stimulation + parathyroid gland hyperplasia)
Calcification risk: Calcium/phosphate loading and active vascular mineralization contribute to arterial and valvular disease. Assess calcium and phosphate individually with PTH trends; a calcium–phosphate product of 55 is not a universal risk or treatment threshold.
Bone disease spectrum: 1. High-turnover bone disease (secondary HPT) - Excessive PTH → osteoblast & osteoclast activity ↑ - Rapid remodeling, loss of cortical bone, trabecular preservation 2. Low-turnover bone disease (adynamic bone) - Suppressed PTH (over-treatment with vitamin D, calcimimetics) - Minimal bone remodeling → impaired fracture healing 3. Mixed uremic osteodystrophy — elements of both
Fragility fractures in dialysis patients are common and cause significant morbidity/mortality despite good Ca/PO4 control. Paradox: high PTH → high turnover → weak bone.
Diagnostic Approach: CKD-MBD Screening
When to Start Monitoring
| Stage | Calcium/phosphate | PTH | Other tests |
|---|---|---|---|
| G1–G2 | According to the clinical question | According to the clinical question | No routine adult CKD-MBD schedule solely from stage |
| G3a–G3b | Every 6–12 months when stable | Baseline and interval according to result and CKD progression | Consider 25-OH vitamin D; assess alkaline phosphatase |
| G4 | Every 3–6 months | Every 6–12 months | Alkaline phosphatase annually, more often with high PTH |
| G5/G5D | Every 1–3 months | Every 3–6 months | Alkaline phosphatase annually; vitamin D when useful |
Shorten intervals for changing values, symptoms, or treatment changes. KDIGO CKD-MBD guidance.
Key Lab Parameters
| Test | Normal | Concern in CKD |
|---|---|---|
| Serum Ca | 8.5–10.5 mg/dL | <8.5 (hypocalcemia) or >10.5 (risk if PO4 also ↑) |
| Serum PO4 | 2.5–4.5 mg/dL | Progressively or persistently elevated phosphate prompts treatment assessment; interpret with calcium, PTH, diet, and CKD stage |
| PTH | 15–65 pg/mL | No established optimal PTH target in nondialysis G3a–G5; in G5D, approximately 2–9 times the assay upper limit, interpreted with trends |
| 25-OH VitD | 30–100 ng/mL | <30 (insufficient); <20 (deficiency) |
| Ca-PO4 product | ~35 | Interpret calcium and phosphate separately; no universal product threshold. |
| Alkaline phosphatase | 30–120 U/L | ↑ in high-turnover; ↓ in adynamic |
| FGF23 | <100 RU/mL | ↑ (research marker; not routine but predictive) |
FGF23 as early warning: Rising FGF23 (>100 RU/mL) at G3a predicts future progression to secondary HPT and bone disease. Not routine but valuable in research settings.
Management Strategy by Stage
CKD G3a–G3b (eGFR 30–59)
Goal: Prevent secondary HPT development
- Phosphate restriction
- Diet: Review phosphate additives and overall intake with a renal dietitian while preserving adequate nutrition; individualize restriction when phosphate is persistently elevated.
- No binders needed yet if serum PO4 normal
- Vitamin D repletion (if 25-OH VitD <30)
- Ergocalciferol (Vitamin D2) 50,000 IU weekly × 12 weeks, then monthly
- OR Cholecalciferol (Vitamin D3) 1,000–2,000 IU daily
- Goal: 25-OH VitD 30–100 ng/mL
- Monitor PTH trend
- If PTH rises progressively or remains above the assay limit, assess phosphate intake, phosphate, calcium, and vitamin D. A mild single rise is not an automatic calcitriol indication.
- Calcium neutral approach — avoid hypercalcemia
CKD G4 (eGFR 15–29)
Goal: Control PTH, phosphate; prevent vascular calcification
- Phosphate-lowering treatment: Base initiation on progressively or persistently elevated phosphate, assessed together with calcium and PTH; do not use one phosphate value as an automatic binder order.
- Calcium-based: Calcium carbonate, calcium acetate
- Pro: Inexpensive, help with acidosis
- Con: Calcium loading can increase hypercalcemia and calcification risk; restrict calcium-based binder exposure in adults and individualize selection without a calcium–phosphate product cutoff.
- Non-calcium: Sevelamer, lanthanum, sucroferric oxyhydroxide
- Pro: Don’t ↑ Ca; may ↓ phosphate absorption better
- Con: Expensive, GI tolerability, multiple daily doses
Key PointModern trend: Avoid calcium-based binders in late CKD; prefer non-calcium agents to minimize Ca load and vascular calcification risk.
- Calcium-based: Calcium carbonate, calcium acetate
- Active vitamin D: Do not use routinely in adult nondialysis CKD. In G4–G5, reserve consideration for severe, progressive hyperparathyroidism after addressing modifiable factors; individualize dose and monitor calcium/phosphate. A PTH cutoff of 110 or a calcium–phosphate product below 55 is not a treatment rule.
- Calcimimetics: Principally a G5D PTH-lowering option with calcium monitoring. Do not automatically apply a dialysis regimen to nondialysis G4; specialist selection considers the indication, calcium/phosphate, treatment effects, and product labeling.
- Monitoring in G4: Calcium/phosphate generally every 3–6 months and PTH every 6–12 months; assess more often when abnormalities or treatment changes warrant it.
CKD G5D (dialysis): distinguish dialysis treatment from G5 not receiving dialysis.
Goal in G5D: Evaluate PTH against the assay upper limit and its trajectory; avoid treatment oversuppression while addressing persistently elevated phosphate and calcium loading.
- Dialysis phosphate removal
- Depends on GFR, urine output, residual kidney function
- Phosphate removal varies with delivered dialysis duration/frequency, rebound, intake and residual kidney function; assess adequacy in the individual patient.
- Aggressive phosphate management
- Binders with meals: Non-calcium preferred (sevelamer, lanthanum)
- Dietary PO4 restriction <1,000 mg/day
- Avoid high-phosphate foods (colas, processed meats, dairy)
- Dialysis PTH framework: Approximately 2–9 times the assay upper limit, with substantial directional changes prompting reassessment; no universal 150–300 pg/mL target applies to every assay.
- Calcium balance
- Avoid hypercalcemia (Ca >10 mg/dL)
- Consider low-Ca dialysate if hypercalcemia
- Bone biopsy (if unexplained bone pain, fractures, or concern for adynamic bone)
- Tetracycline labeling → assess turnover, mineralization
- Guides intensity of therapy
Newer Agents (Emerging in CKD G3b–G4)
FGF23 Antagonists (Research phase)
- Direct FGF23 blockade is not established routine treatment for CKD-MBD. Do not extrapolate therapies for hypophosphatemic disorders to CKD phosphate retention.
Phosphate Binders (Newer generation)
- Sucroferric oxyhydroxide is an iron-based phosphate binder administered with meals according to its label; it is not a once-daily regimen.
- Patiromer treats hyperkalemia; it is not a substitute for an indicated phosphate-lowering treatment.
Bone Health: Fracture Prevention
Screening for Osteoporosis in CKD
- DXA/BMD testing: In G3a–G5D with CKD-MBD or osteoporosis risk factors, obtain BMD testing when the result will affect treatment decisions. DXA does not determine the renal bone-turnover subtype; assess that question separately.
- Combine fracture history, falls risk, relevant biochemistry, and BMD when it will change management; consider specialist bone-turnover assessment when needed.
Management
- Exercise and nutrition: Encourage safe weight-bearing activity and adequate nutrition. Protein needs differ between nondialysis CKD and dialysis; individualize with a renal dietitian.
- Calcium balance: Avoid both hypo- and hypercalcemia
- Vitamin D: Maintain 25-OH VitD >30 ng/mL
- Antifracture therapy in advanced CKD requires assessment of kidney function, CKD-MBD, likely turnover and the selected drug label; use specialist input rather than a blanket regimen.
- Consider anabolic agents (PTH analogues) if documented low-turnover bone on biopsy (rare, specialized)
Vascular Calcification & Cardiovascular Risk
Coronary artery calcification in ESRD: Present in 40–80% of dialysis patients; major predictor of CV death (more predictive than Framingham risk).
Mechanisms of Vascular Calcification in CKD
- Mineral deposition: Calcium and phosphate loading contribute to vascular mineral deposition, but a product of 55 is not a universal precipitation or treatment threshold.
- Active osteogenic conversion: Vascular smooth muscle cells transdifferentiate → osteoblast-like → produce mineralization matrix
- Loss of calcification inhibitors: ↓ Fetuin-A, matrix Gla protein (MGP)
- Oxidative stress & inflammation from uremia
Prevention
- Treat progressively or persistently elevated phosphate, aiming to lower elevated values toward the normal range while considering calcium and PTH together.
- Use the individual calcium and phosphate values rather than a calcium–phosphate product target.
- Avoid excess calcium supplementation
- Use non-calcium binders
- Manage inflammation (dialysis adequacy)
Clinical pearl: Established vascular calcification identifies high cardiovascular risk. Avoid excessive calcium loading and treat persistent mineral abnormalities; prophylactic binders in normophosphatemic early CKD have not been established to prevent future calcification.
Self-Test Questions
- 50M, GFR 40, serum Ca 8.2, PO4 4.6, PTH 95, 25-OH VitD 28
- CKD-MBD stage: Mild 2° HPT (early)
- Intervention: Vitamin D2 to target >30; dietary PO4 reduction; recheck PTH Q3 months
- If PTH continues rising, reassess modifiable factors and the trend; do not reflexively prescribe calcitriol for mild G3b hyperparathyroidism.
- 72F, GFR 18, Ca 9.8, PO4 6.2, PTH 450, Ca-PO4 product 61
- CKD-MBD stage: Advanced 2° HPT with calcification risk
- Intervention: Confirm persistent phosphate elevation, review intake and select phosphate-lowering treatment. For G4, consider active vitamin D only for severe, progressive hyperparathyroidism after addressing modifiable factors, with calcium/phosphate monitoring.
- If hypercalcemia develops, reassess calcium-containing treatments and active vitamin D. Do not automatically add a calcimimetic to a nondialysis G4 regimen.
- Dialysis patient, PTH 120 (LOW)
- Risk: Adynamic bone disease (suppressed turnover)
- Intervention: Reduce vitamin D, consider bone biopsy, hold calcimimetics
- Goal: Review treatment oversuppression using the assay upper limit and trends, rather than forcing PTH into a universal 150–300 interval.
Version 1.0 | PA/Medical student level | Updated 2026-02-28
References: KDIGO 2009 CKD–Mineral and Bone Disorder guideline (Kidney Int Suppl. 2009;113:S1–S130); KDIGO 2017 CKD-MBD update.
Also on this topic
The same subject at other levels of depth.
- Interactive case: CKD-Mineral and Bone Disorder
- Clinical Mastery deep dive: CKD Mineral and Bone Disease