Visual summary
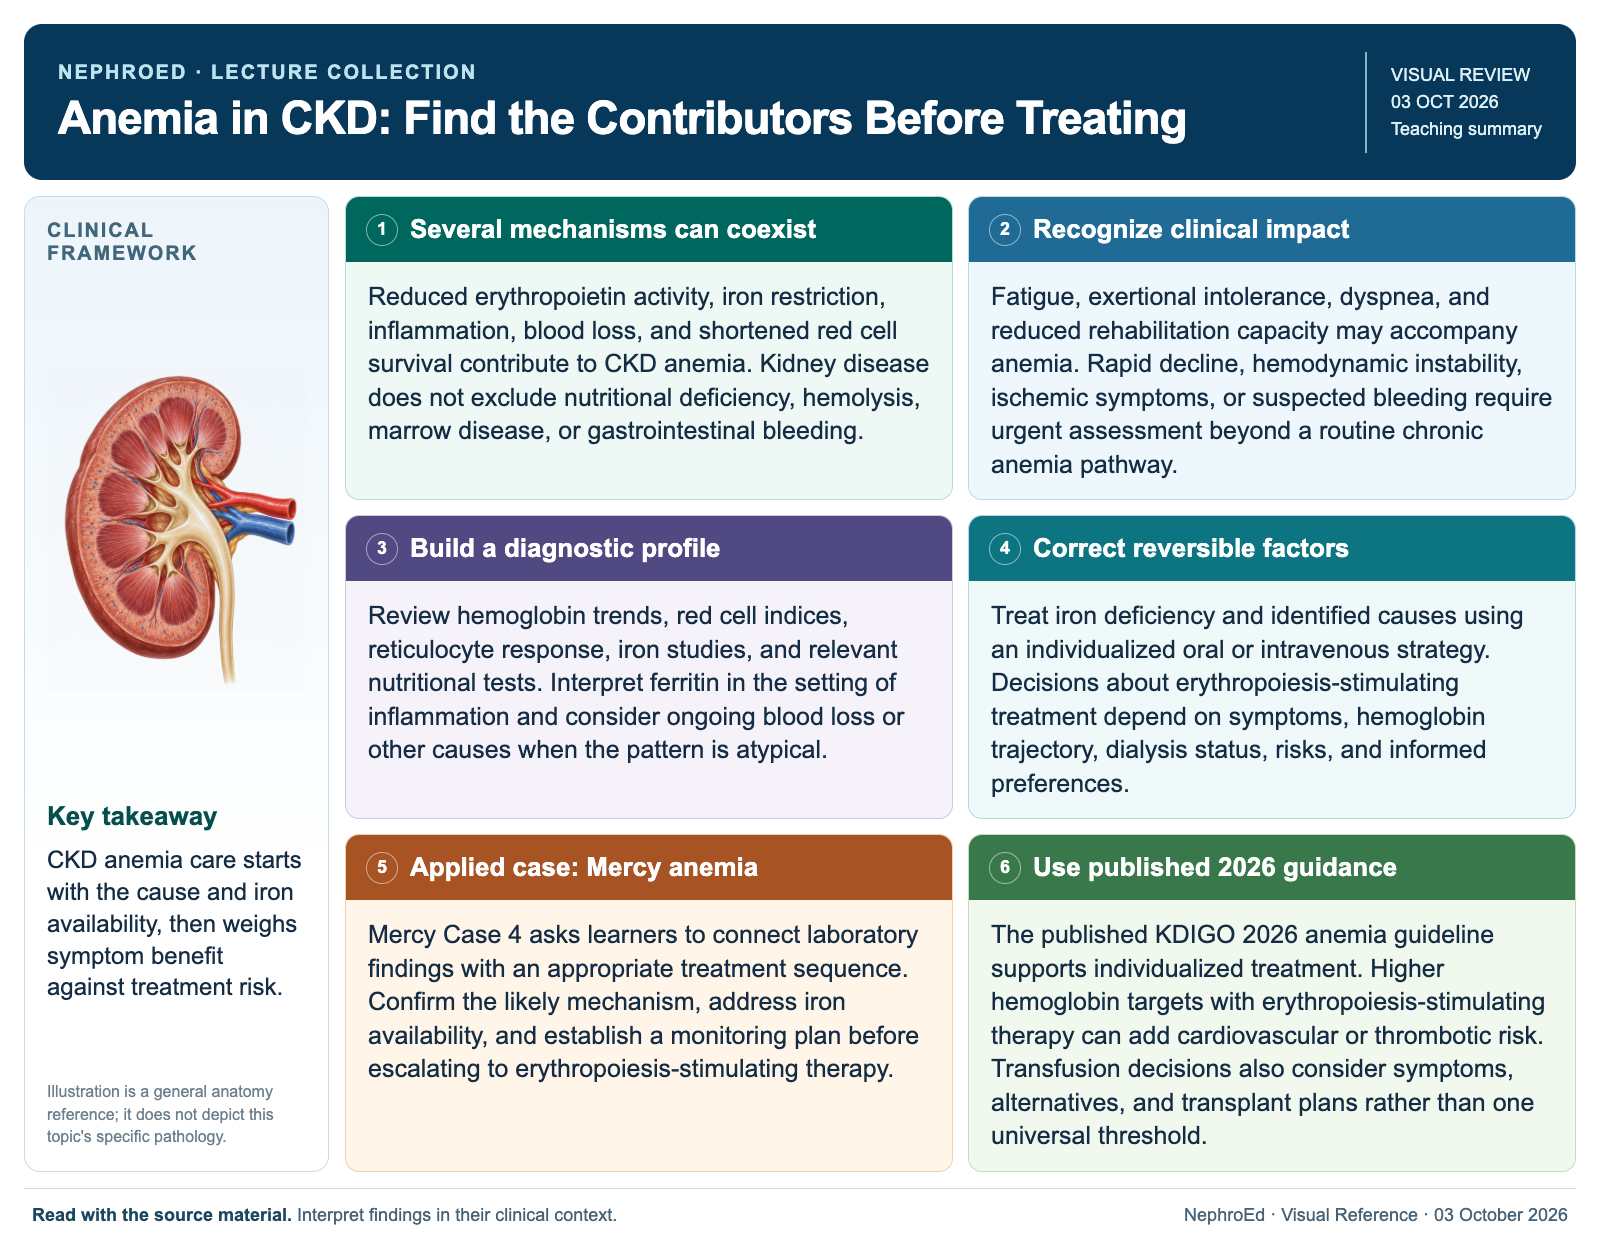
CKD anemia care starts with the cause and iron availability, then weighs symptom benefit against treatment risk.
Text version
Several mechanisms can coexist
Reduced erythropoietin activity, iron restriction, inflammation, blood loss, and shortened red cell survival contribute to CKD anemia. Kidney disease does not exclude nutritional deficiency, hemolysis, marrow disease, or gastrointestinal bleeding.
Recognize clinical impact
Fatigue, exertional intolerance, dyspnea, and reduced rehabilitation capacity may accompany anemia. Rapid decline, hemodynamic instability, ischemic symptoms, or suspected bleeding require urgent assessment beyond a routine chronic anemia pathway.
Build a diagnostic profile
Review hemoglobin trends, red cell indices, reticulocyte response, iron studies, and relevant nutritional tests. Interpret ferritin in the setting of inflammation and consider ongoing blood loss or other causes when the pattern is atypical.
Correct reversible factors
Treat iron deficiency and identified causes using an individualized oral or intravenous strategy. Decisions about erythropoiesis-stimulating treatment depend on symptoms, hemoglobin trajectory, dialysis status, risks, and informed preferences.
Applied case: Mercy anemia
Mercy Case 4 asks learners to connect laboratory findings with an appropriate treatment sequence. Confirm the likely mechanism, address iron availability, and establish a monitoring plan before escalating to erythropoiesis-stimulating therapy.
Use published 2026 guidance
The published KDIGO 2026 anemia guideline supports individualized treatment. Higher hemoglobin targets with erythropoiesis-stimulating therapy can add cardiovascular or thrombotic risk. Transfusion decisions also consider symptoms, alternatives, and transplant plans rather than one universal threshold.
Continue learning
This graphic summarizes a topic. The full educational pages provide the broader discussion and references.