Visual summary
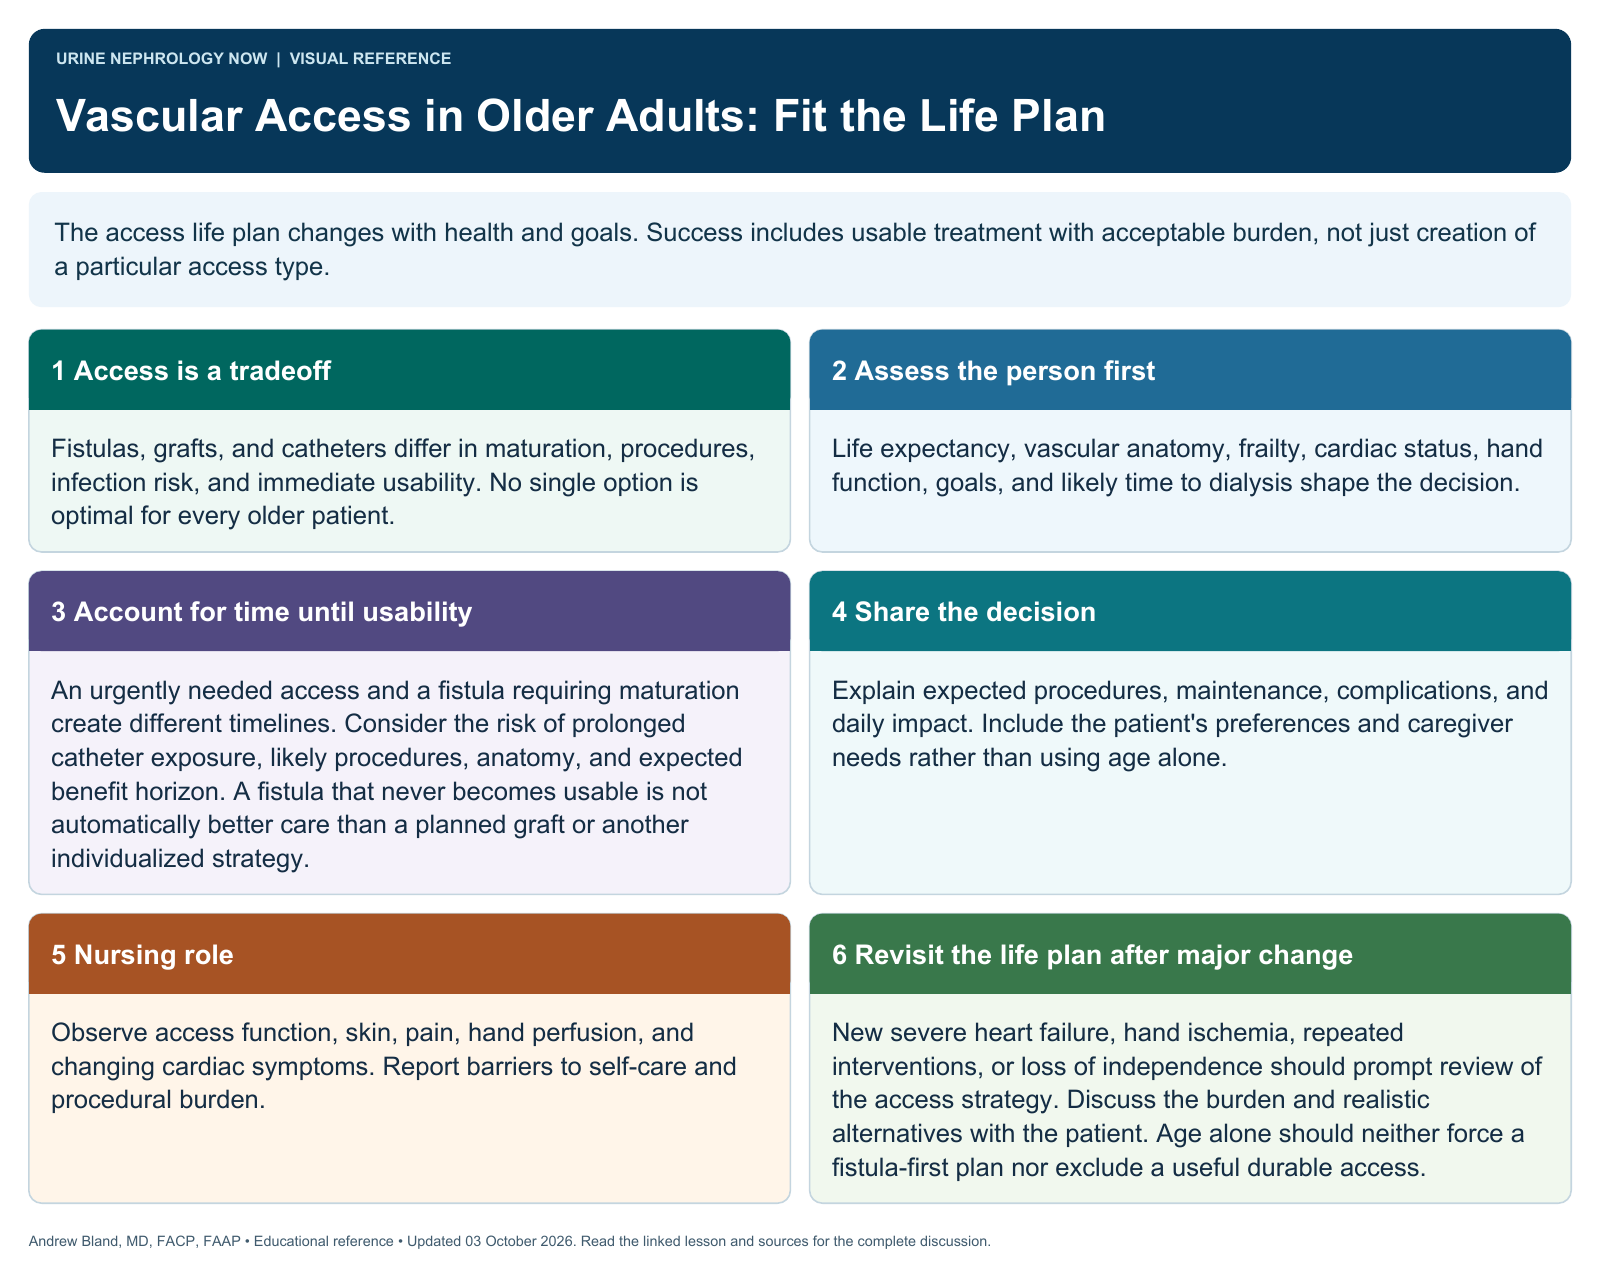
The access life plan changes with health and goals. Success includes usable treatment with acceptable burden, not just creation of a particular access type.
Text version
Access is a tradeoff
Fistulas, grafts, and catheters differ in maturation, procedures, infection risk, and immediate usability. No single option is optimal for every older patient.
Assess the person first
Life expectancy, vascular anatomy, frailty, cardiac status, hand function, goals, and likely time to dialysis shape the decision.
Account for time until usability
An urgently needed access and a fistula requiring maturation create different timelines. Consider the risk of prolonged catheter exposure, likely procedures, anatomy, and expected benefit horizon. A fistula that never becomes usable is not automatically better care than a planned graft or another individualized strategy.
Share the decision
Explain expected procedures, maintenance, complications, and daily impact. Include the patient's preferences and caregiver needs rather than using age alone.
Nursing role
Observe access function, skin, pain, hand perfusion, and changing cardiac symptoms. Report barriers to self-care and procedural burden.
Revisit the life plan after major change
New severe heart failure, hand ischemia, repeated interventions, or loss of independence should prompt review of the access strategy. Discuss the burden and realistic alternatives with the patient. Age alone should neither force a fistula-first plan nor exclude a useful durable access.