Visual summary
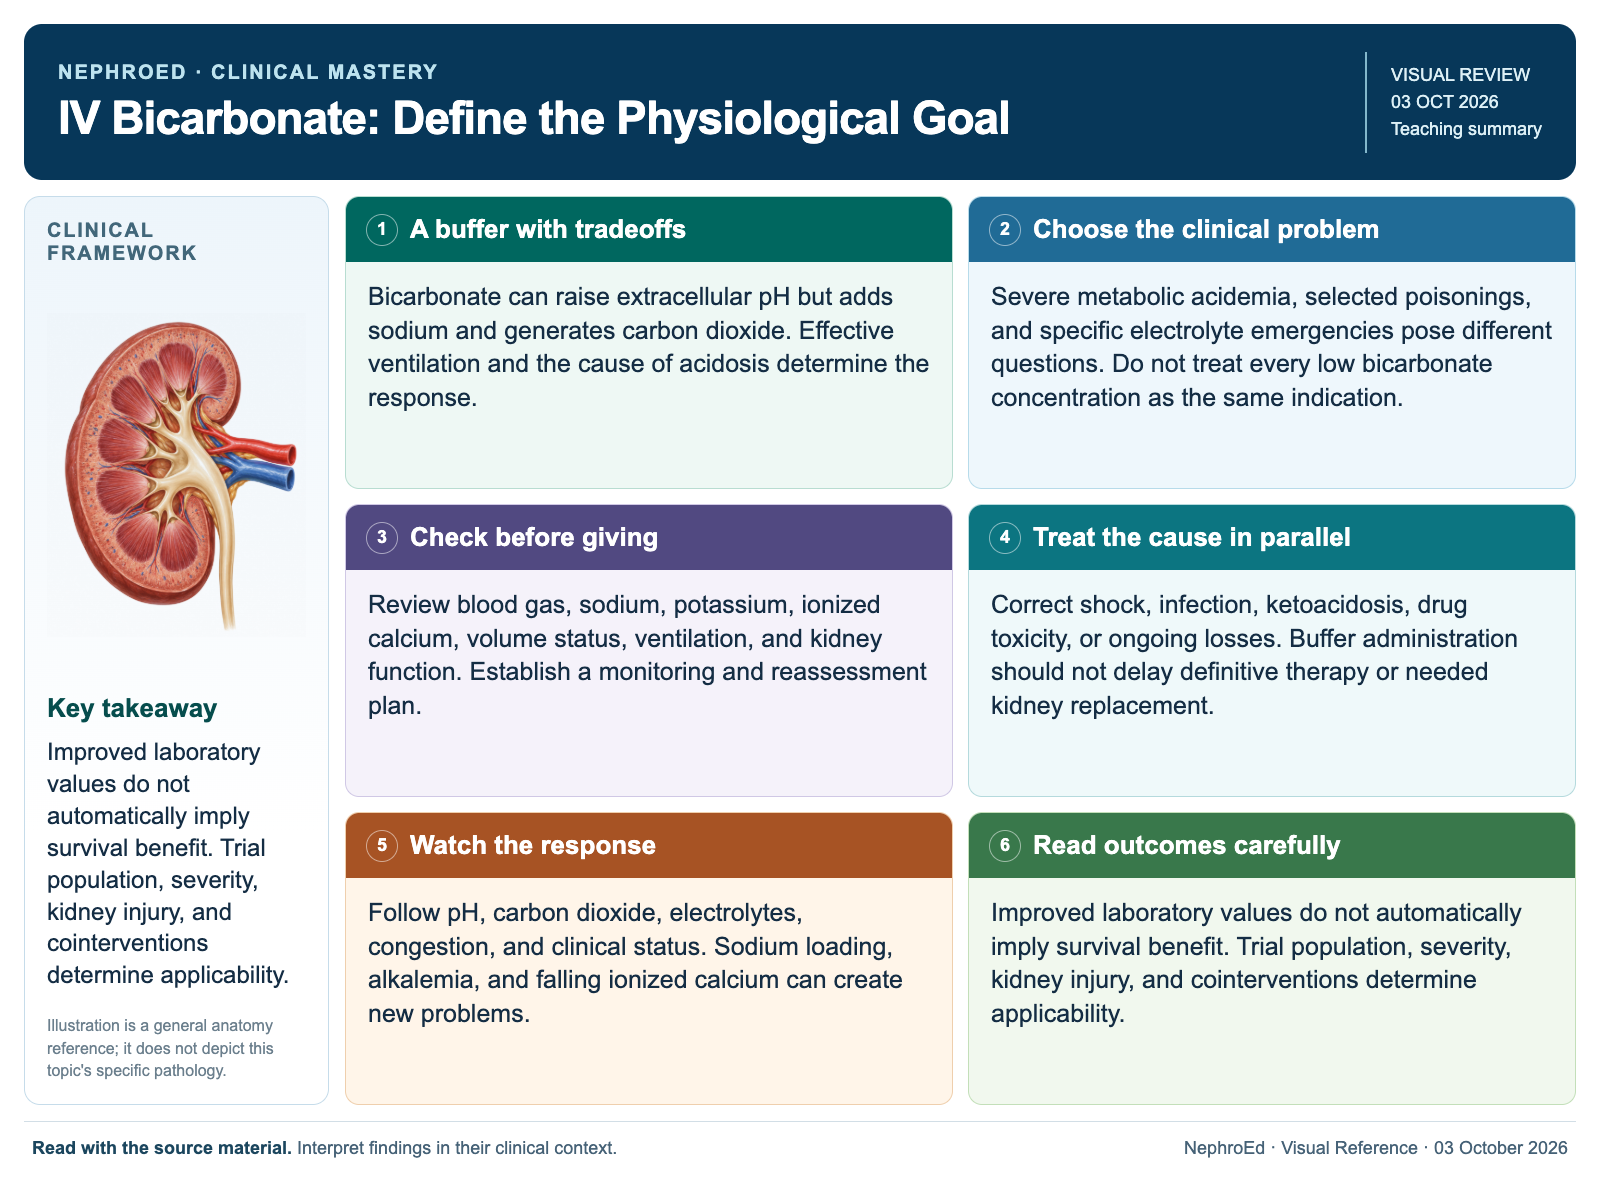
Improved laboratory values do not automatically imply survival benefit. Trial population, severity, kidney injury, and cointerventions determine applicability.
Text version
A buffer with tradeoffs
Bicarbonate can raise extracellular pH but adds sodium and generates carbon dioxide. Effective ventilation and the cause of acidosis determine the response.
Choose the clinical problem
Severe metabolic acidemia, selected poisonings, and specific electrolyte emergencies pose different questions. Do not treat every low bicarbonate concentration as the same indication.
Check before giving
Review blood gas, sodium, potassium, ionized calcium, volume status, ventilation, and kidney function. Establish a monitoring and reassessment plan.
Treat the cause in parallel
Correct shock, infection, ketoacidosis, drug toxicity, or ongoing losses. Buffer administration should not delay definitive therapy or needed kidney replacement.
Watch the response
Follow pH, carbon dioxide, electrolytes, congestion, and clinical status. Sodium loading, alkalemia, and falling ionized calcium can create new problems.
Read outcomes carefully
Improved laboratory values do not automatically imply survival benefit. Trial population, severity, kidney injury, and cointerventions determine applicability.
Continue learning
This graphic summarizes a topic. The full educational pages provide the broader discussion and references.