IV Sodium Bicarbonate in Critical Care
Effectiveness, Risks, and Interaction with Vasopressors — Clinical Evidence and Important Limitations (updated 2026)
Author: Andrew Bland, MD, FACP, FAAP
Visual reference
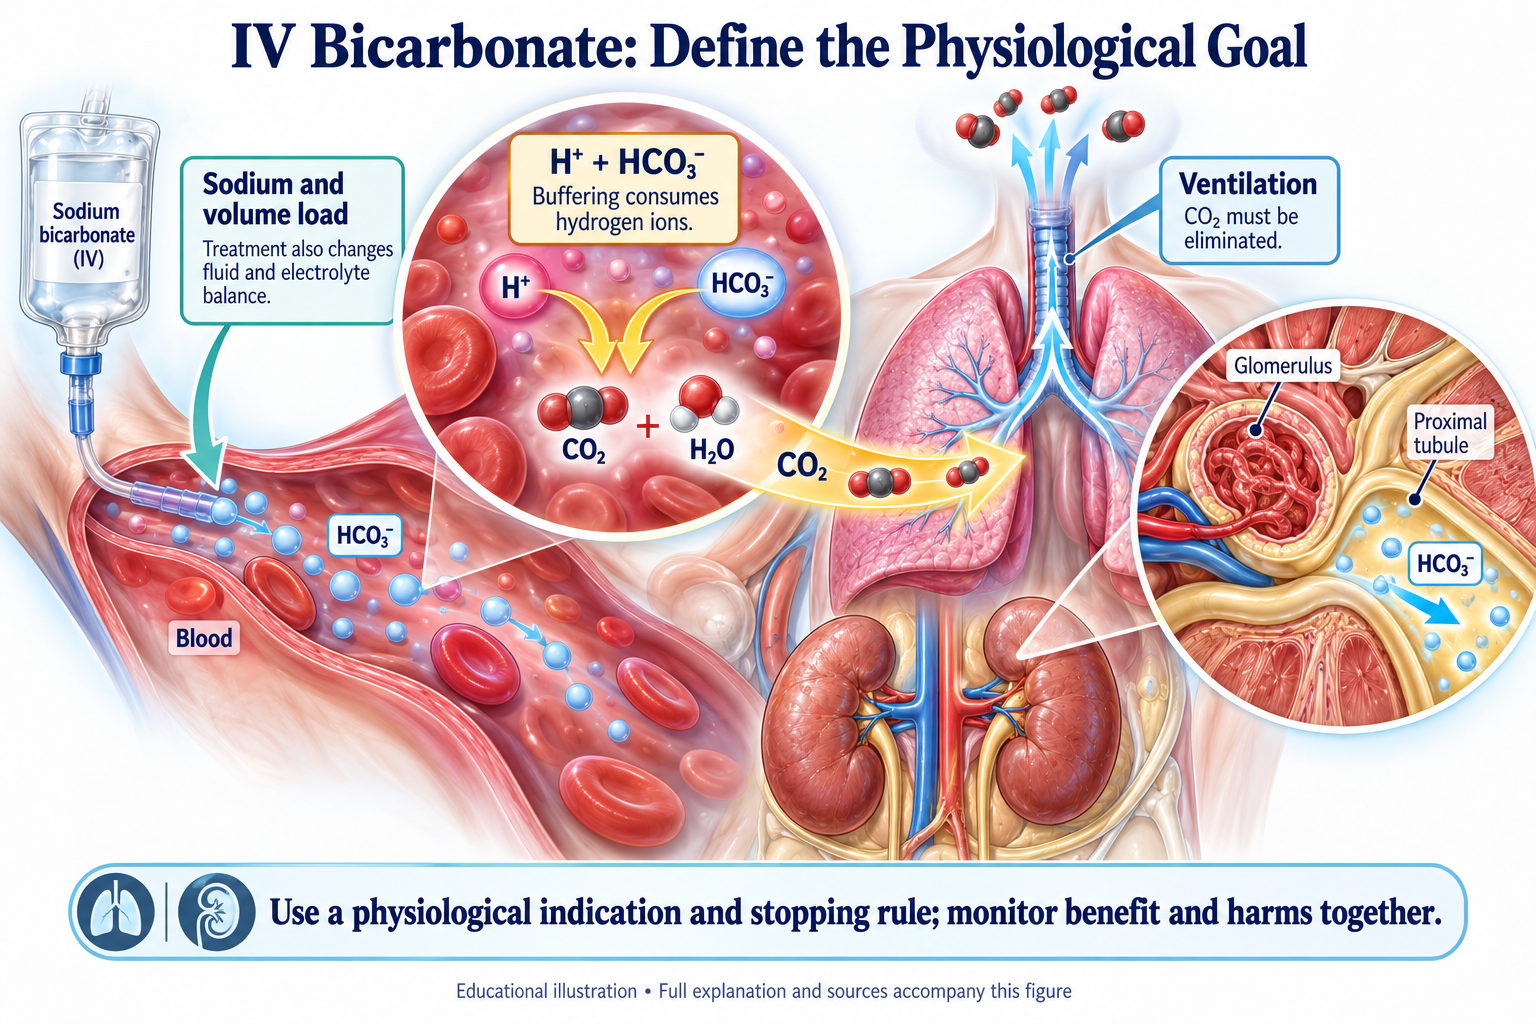
Browse the visual reference library · Download lesson Markdown
Executive Summary
- Bicarbonate raises blood pH. BICARICU-2 found no 90-day survival benefit in severe acidemia with moderate-to-severe AKI, but fewer patients received kidney replacement therapy
- CO2 generation, sodium and volume loading, alkalosis, and electrolyte shifts require monitoring; laboratory intracellular-pH findings do not establish clinical safety
- Lower pH is associated with poorer vasopressin response in observational septic-shock data; this does not prove that bicarbonate reverses shock
- Treat the cause of acidosis and individualize bicarbonate use; a lower dialysis rate is a different outcome from improved survival
Introduction
Metabolic acidosis is a common complication in critically ill patients that carries significant morbidity and mortality. The management of this condition remains controversial, particularly regarding the use of intravenous sodium bicarbonate as a therapeutic intervention.
This review examines clinical trials, reviews, and mechanistic studies to evaluate three critical aspects:
- The clinical effectiveness of IV sodium bicarbonate in improving patient outcomes
- The risks associated with bicarbonate therapy, with particular attention to paradoxical intracellular acidosis
- The relationship between blood pH and vasopressor effectiveness, especially at pH levels below 7.20
Effectiveness of IV Sodium Bicarbonate Therapy
Sodium bicarbonate administration in critically ill patients may facilitate rapid normalization of arterial blood gas parameters. However, the evidence for clinical outcome benefits remains limited.
Biochemical Effects
A scoping review and systematic review assessing the biochemical and physiological effects of IV sodium bicarbonate in critically ill patients with metabolic acidosis found that it:
| Parameter | Effect |
|---|---|
| Blood pH | Increased |
| Base excess | Increased |
| Serum bicarbonate | Increased |
| Serum sodium | Increased |
| PaCO2 | Increased |
| Anion gap | Decreased |
| Potassium | Decreased |
The 2019 review predates later trials. Biochemical improvement alone does not establish patient benefit; current outcome interpretation should include BICARICU-2.
Randomized Evidence in Severe Acidemia and AKI
A 2026 patient-level meta-analysis of BICAR-ICU and BICARICU-2 likewise found no overall 90-day mortality reduction and less KRT use. A signal in the most acidemic subgroup (pH ≤7.10) requires cautious interpretation and does not establish a universal treatment threshold. Patient-level meta-analysis.
Risks of Sodium Bicarbonate Therapy
Paradoxical Intracellular Acidosis
One of the primary concerns with bicarbonate therapy is paradoxical intracellular acidosis. The mechanism occurs because sodium bicarbonate reacts with hydrogen ions to form carbonic acid, which dissociates into water and carbon dioxide. While bicarbonate ions diffuse slowly across cell membranes, CO2 diffuses rapidly, potentially leading to a transient intracellular acidosis as CO2 combines with water to form carbonic acid intracellularly.
Additional Risks
- Increased PaCO2 — especially problematic in patients with limited pulmonary reserve who cannot eliminate the increased CO2 load
- Hyperosmolality and hypernatremia
- Volume overload
- pH overcorrection resulting in metabolic alkalosis
- Hypocalcemia
- Decreased tissue oxygenation
- Hypokalemia
Cerebral Effects
Rapid changes in CO2 and pH can affect cerebral physiology. Evidence from specific experimental and clinical settings should not be generalized to every ICU patient. Monitor ventilation and neurologic status, and follow disease-specific protocols when cerebral injury or ketoacidosis is present.
Effect of Blood pH on Vasopressor Effectiveness
Acidemia may contribute to vascular hyporesponsiveness. Human observational data show an association between lower pH and poorer vasopressin response, without proving causation or a sharp pH threshold.
Effects on Vasopressin
A retrospective, multicenter, observational cohort study found that compared with higher arterial pH, patients with septic shock and low arterial pH had lower odds of vasopressin response and higher catecholamine doses after vasopressin initiation.
For each 0.1 unit arterial pH below 7.40:
• Vasopressin response OR: 0.79 (95% CI 0.72–0.87)
• Norepinephrine-equivalent dose increase at 1 hr: +1.5 μg/min (95% CI 0.5–2.5)
• Norepinephrine-equivalent dose increase at 6 hr: +2.5 μg/min (95% CI 1.4–3.5)
These estimates describe associations in a retrospective cohort and should not be used to calculate an individual patient's vasopressor dose. Bauer et al., 2022
Effects on Catecholamines
Experimental evidence suggests that in tightly controlled conditions, acidosis decreases the response of adrenergic receptors to agonists through several mechanisms:
- Direct effects on adrenergic receptor function
- Altered calcium handling in vascular smooth muscle
- Impaired signal transduction pathways
- Decreased cardiac contractility
Conclusion and Clinical Implications
The use of IV sodium bicarbonate in critically ill patients remains a complex therapeutic decision.
- Severe acidemia with AKI: Consider the trial population, cause of acidosis, trajectory, and risks. Bicarbonate may reduce KRT use in selected patients; an overall survival benefit has not been demonstrated
- Shock: Restore perfusion and treat its cause. Observational pH-response associations do not establish bicarbonate as a vasopressor-sparing therapy
- Ventilatory monitoring: Careful attention to ventilatory status to ensure adequate CO2 elimination, as well as to electrolyte balance (including sodium, potassium, and ionized calcium)
- Individualized approach: The decision to administer bicarbonate should be individualized based on the patient's clinical condition, the cause of acidosis, and the presence of organ dysfunction
References
- Eraky AM, Yerramalla Y, Khan A, et al. Complexities, Benefits, Risks, and Clinical Implications of Sodium Bicarbonate Administration in Critically Ill Patients: A State-of-the-Art Review. J Clin Med 2024;13(24):. PubMed 39768744
- Yagi K, Fujii T. Management of acute metabolic acidosis in the ICU: sodium bicarbonate and renal replacement therapy. Crit Care 2021;25(1):314. PubMed 34461963
- Forni LG, Hodgson LE, Selby NM. The Janus faces of bicarbonate therapy in the ICU: not sure! Intensive Care Med 2020;46(3):522. PubMed 31820031
- Fujii T, Udy A, Licari E, et al. Sodium bicarbonate therapy for critically ill patients with metabolic acidosis: A scoping and a systematic review. J Crit Care 2019;51():184. PubMed 30852347
- Waskowski J, Hess B, Cioccari L, et al. Effects of sodium bicarbonate infusion on mortality in medical-surgical ICU patients with metabolic acidosis-A single-center propensity score matched analysis. Med Intensiva (Engl Ed) 2022;46(12):690. PubMed 34120787
- Jaber S, Paugam C, Futier E, et al. Sodium bicarbonate therapy for patients with severe metabolic acidaemia in the intensive care unit (BICAR-ICU): a multicentre, open-label, randomised controlled, phase 3 trial. Lancet 2018;392(10141):31. PubMed 29910040
- Jung B, Jabaudon M, De Jong A, et al. Sodium Bicarbonate for Severe Metabolic Acidemia and Acute Kidney Injury: The BICARICU-2 Randomized Clinical Trial. JAMA 2025;334(22):2000. PubMed 41159812
- Fosset M, Pensier J, Jabaudon M, et al. Sodium bicarbonate therapy in severe metabolic acidemia: an individual patient data meta-analysis of the BICAR-ICU and BICAR-ICU2 trials. Crit Care 2026;30(1):. PubMed 42472834
- Fujii T, Udy AA, Nichol A, et al. Incidence and management of metabolic acidosis with sodium bicarbonate in the ICU: An international observational study. Crit Care 2021;25(1):45. PubMed 33531020
- Velissaris D, Karamouzos V, Ktenopoulos N, et al. The Use of Sodium Bicarbonate in the Treatment of Acidosis in Sepsis: A Literature Update on a Long Term Debate. Crit Care Res Pract 2015;2015():605830. PubMed 26294968
- Levraut J, Labib Y, Chave S, et al. Effect of sodium bicarbonate on intracellular pH under different buffering conditions. Kidney Int 1996;49(5):1262. PubMed 8731089
- Kotani Y, Di Gioia A, Landoni G, et al. An updated "norepinephrine equivalent" score in intensive care as a marker of shock severity. Crit Care 2023;27(1):29. PubMed 36670410
- Bauer SR, Sacha GL, Siuba MT, et al. Association of Arterial pH With Hemodynamic Response to Vasopressin in Patients With Septic Shock: An Observational Cohort Study. Crit Care Explor 2022;4(2):e0634. PubMed 35156051
- Russell JA. Vasopressor therapy in critically ill patients with shock. Intensive Care Med 2019;45(11):1503. PubMed 31646370
- Shi R, Hamzaoui O, De Vita N, et al. Vasopressors in septic shock: which, when, and how much? Ann Transl Med 2020;8(12):794. PubMed 32647719
© 2025 Andrew Bland, MD, FACP, FAAP — Urine Nephrology Now