Visual summary
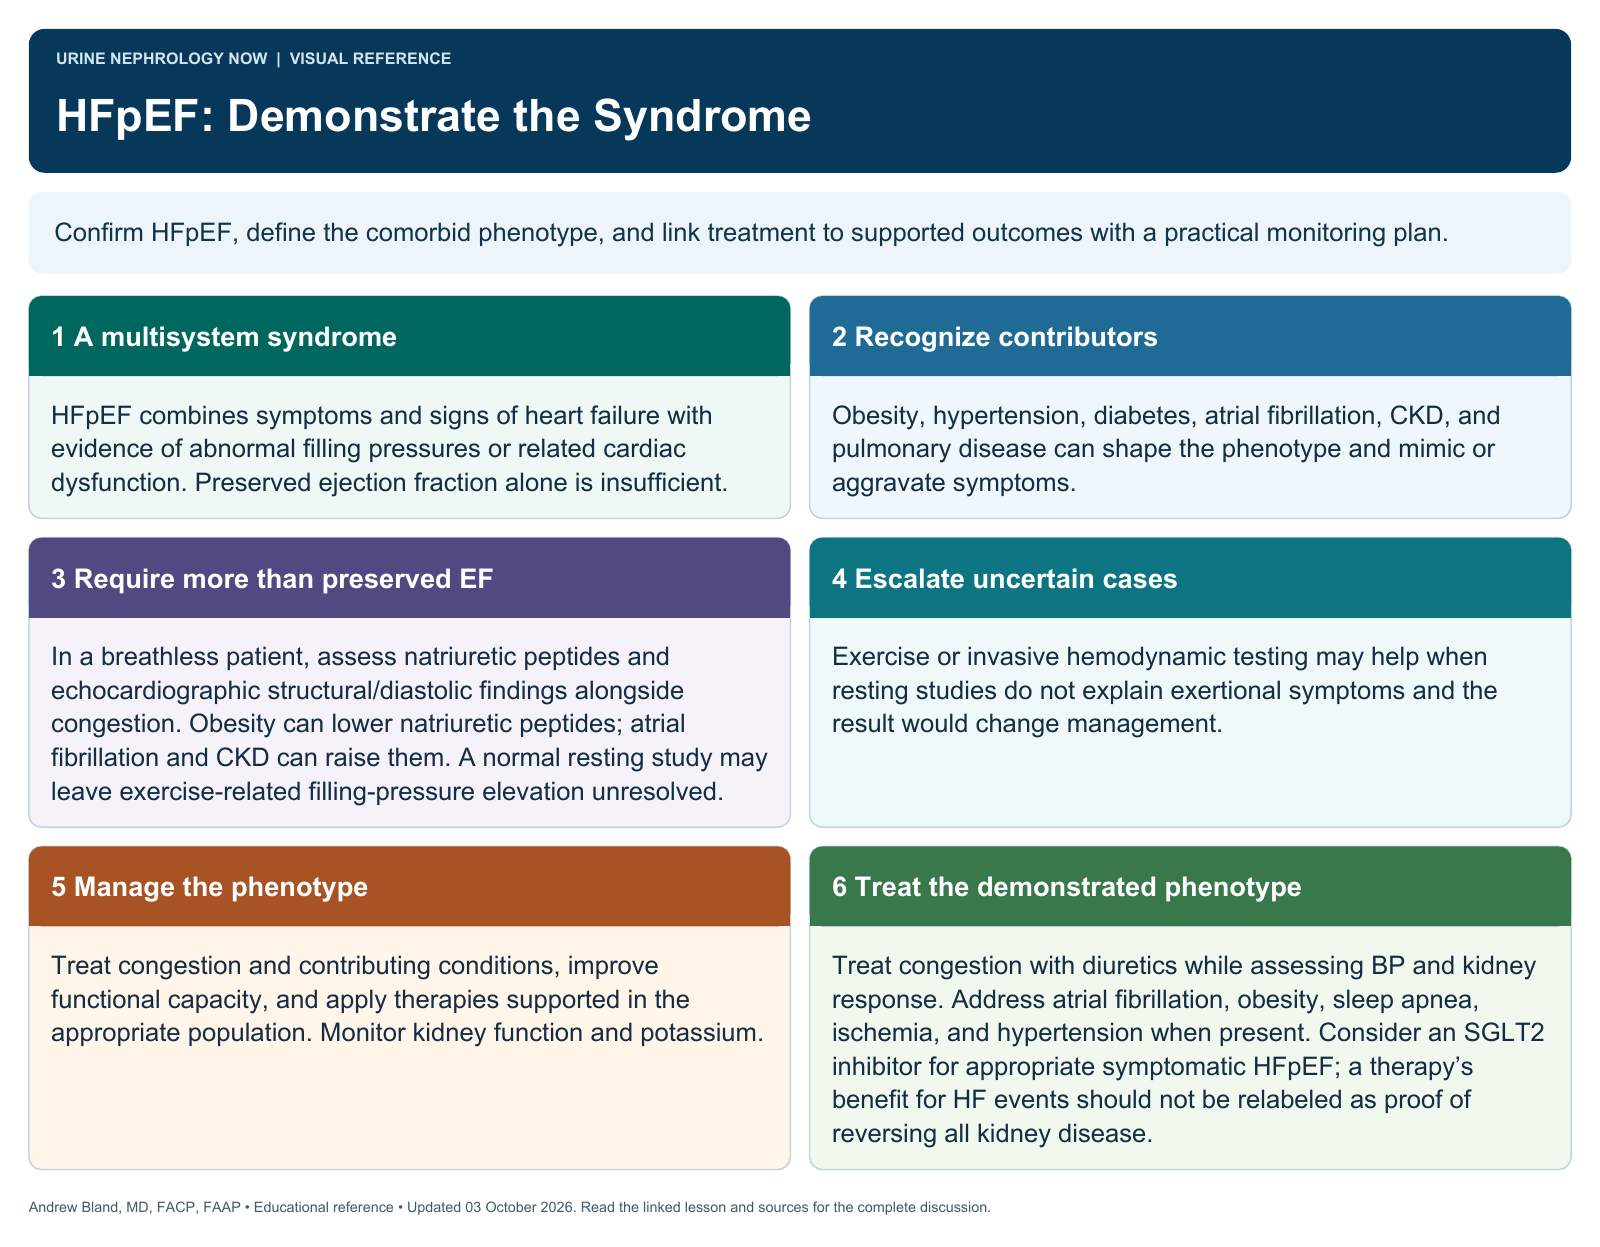
Confirm HFpEF, define the comorbid phenotype, and link treatment to supported outcomes with a practical monitoring plan.
Text version
A multisystem syndrome
HFpEF combines symptoms and signs of heart failure with evidence of abnormal filling pressures or related cardiac dysfunction. Preserved ejection fraction alone is insufficient.
Recognize contributors
Obesity, hypertension, diabetes, atrial fibrillation, CKD, and pulmonary disease can shape the phenotype and mimic or aggravate symptoms.
Require more than preserved EF
In a breathless patient, assess natriuretic peptides and echocardiographic structural/diastolic findings alongside congestion. Obesity can lower natriuretic peptides; atrial fibrillation and CKD can raise them. A normal resting study may leave exercise-related filling-pressure elevation unresolved.
Escalate uncertain cases
Exercise or invasive hemodynamic testing may help when resting studies do not explain exertional symptoms and the result would change management.
Manage the phenotype
Treat congestion and contributing conditions, improve functional capacity, and apply therapies supported in the appropriate population. Monitor kidney function and potassium.
Treat the demonstrated phenotype
Treat congestion with diuretics while assessing BP and kidney response. Address atrial fibrillation, obesity, sleep apnea, ischemia, and hypertension when present. Consider an SGLT2 inhibitor for appropriate symptomatic HFpEF; a therapy’s benefit for HF events should not be relabeled as proof of reversing all kidney disease.