Visual summary
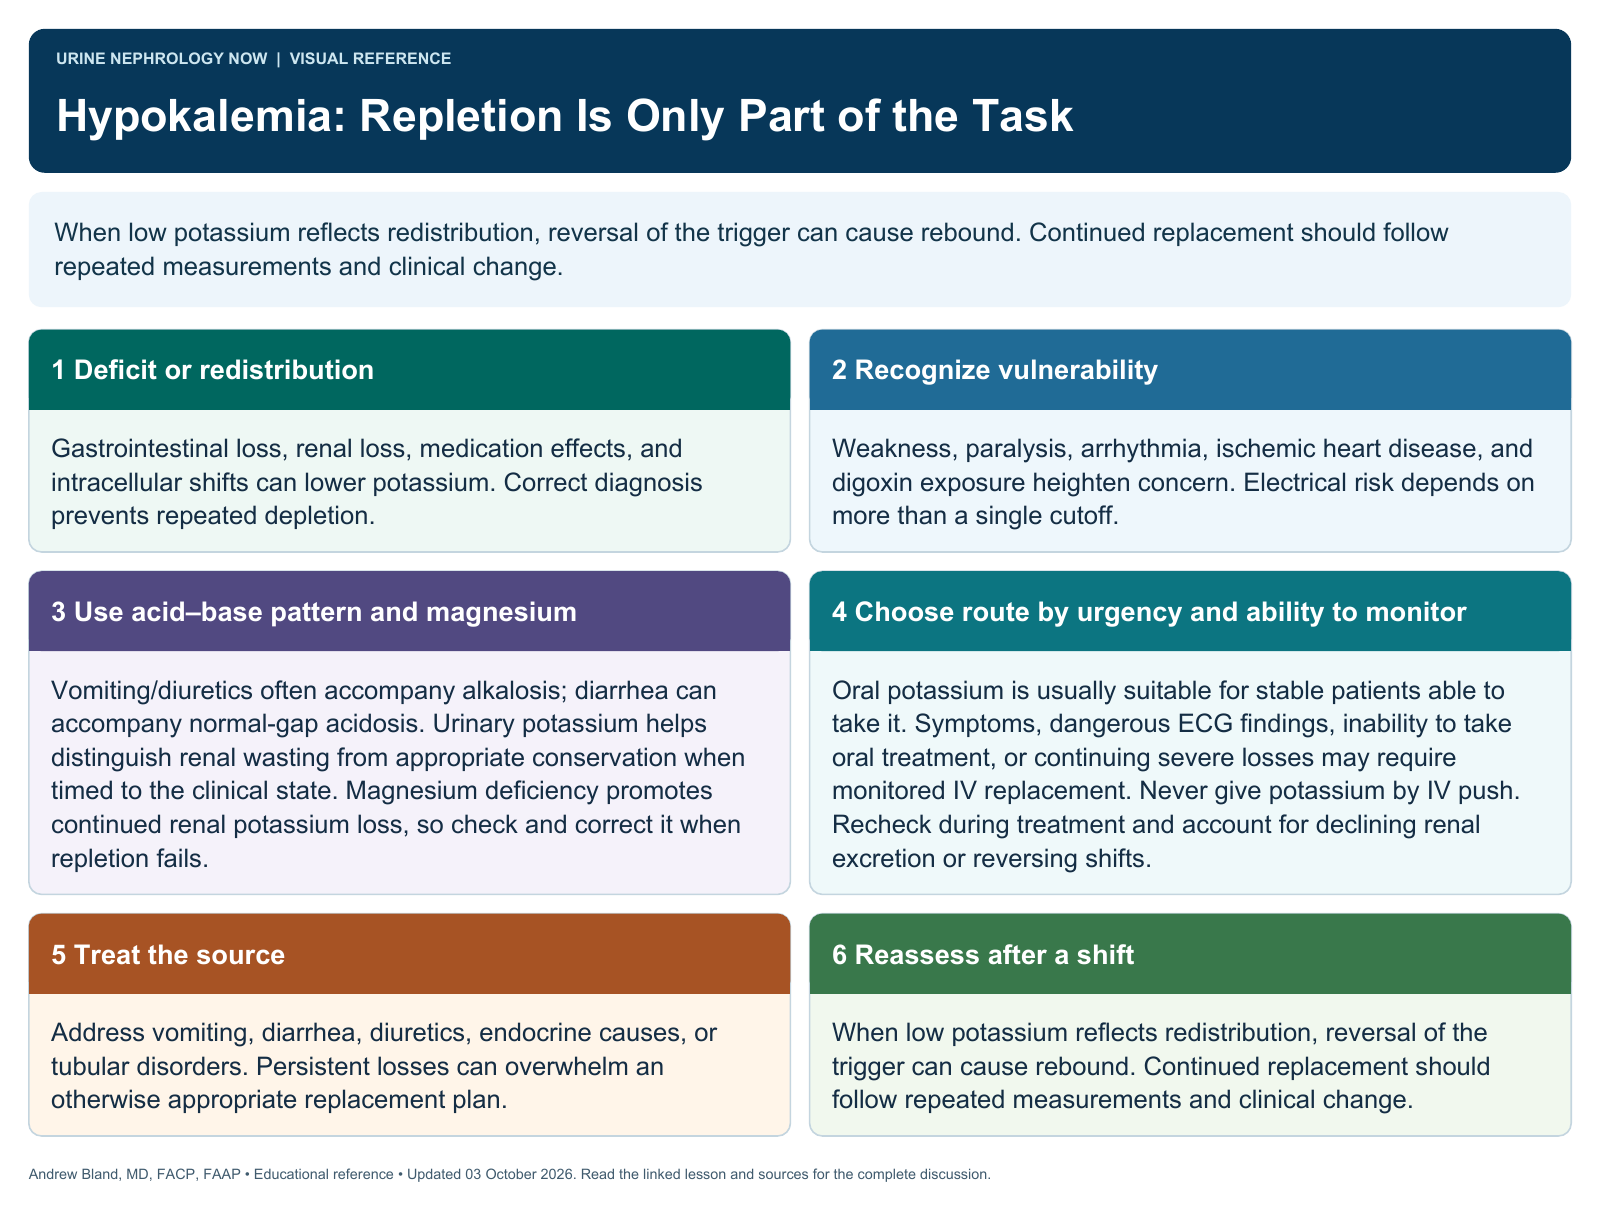
When low potassium reflects redistribution, reversal of the trigger can cause rebound. Continued replacement should follow repeated measurements and clinical change.
Text version
Deficit or redistribution
Gastrointestinal loss, renal loss, medication effects, and intracellular shifts can lower potassium. Correct diagnosis prevents repeated depletion.
Recognize vulnerability
Weakness, paralysis, arrhythmia, ischemic heart disease, and digoxin exposure heighten concern. Electrical risk depends on more than a single cutoff.
Check associated physiology
Assess magnesium, acid–base status, kidney function, medication history, and urinary potassium when useful. Magnesium deficiency can hinder correction.
Replace carefully
Choose route and intensity according to severity, symptoms, ongoing losses, and kidney function. Monitor during treatment and avoid unobserved rapid correction.
Treat the source
Address vomiting, diarrhea, diuretics, endocrine causes, or tubular disorders. Persistent losses can overwhelm an otherwise appropriate replacement plan.
Reassess after a shift
When low potassium reflects redistribution, reversal of the trigger can cause rebound. Continued replacement should follow repeated measurements and clinical change.
Continue learning
This graphic summarizes a topic. The full educational pages provide the broader discussion and references.