Visual summary
Failure to respond as expected should prompt review of diagnosis, adherence, secondary causes, and whether additional pathology is present.
Text version
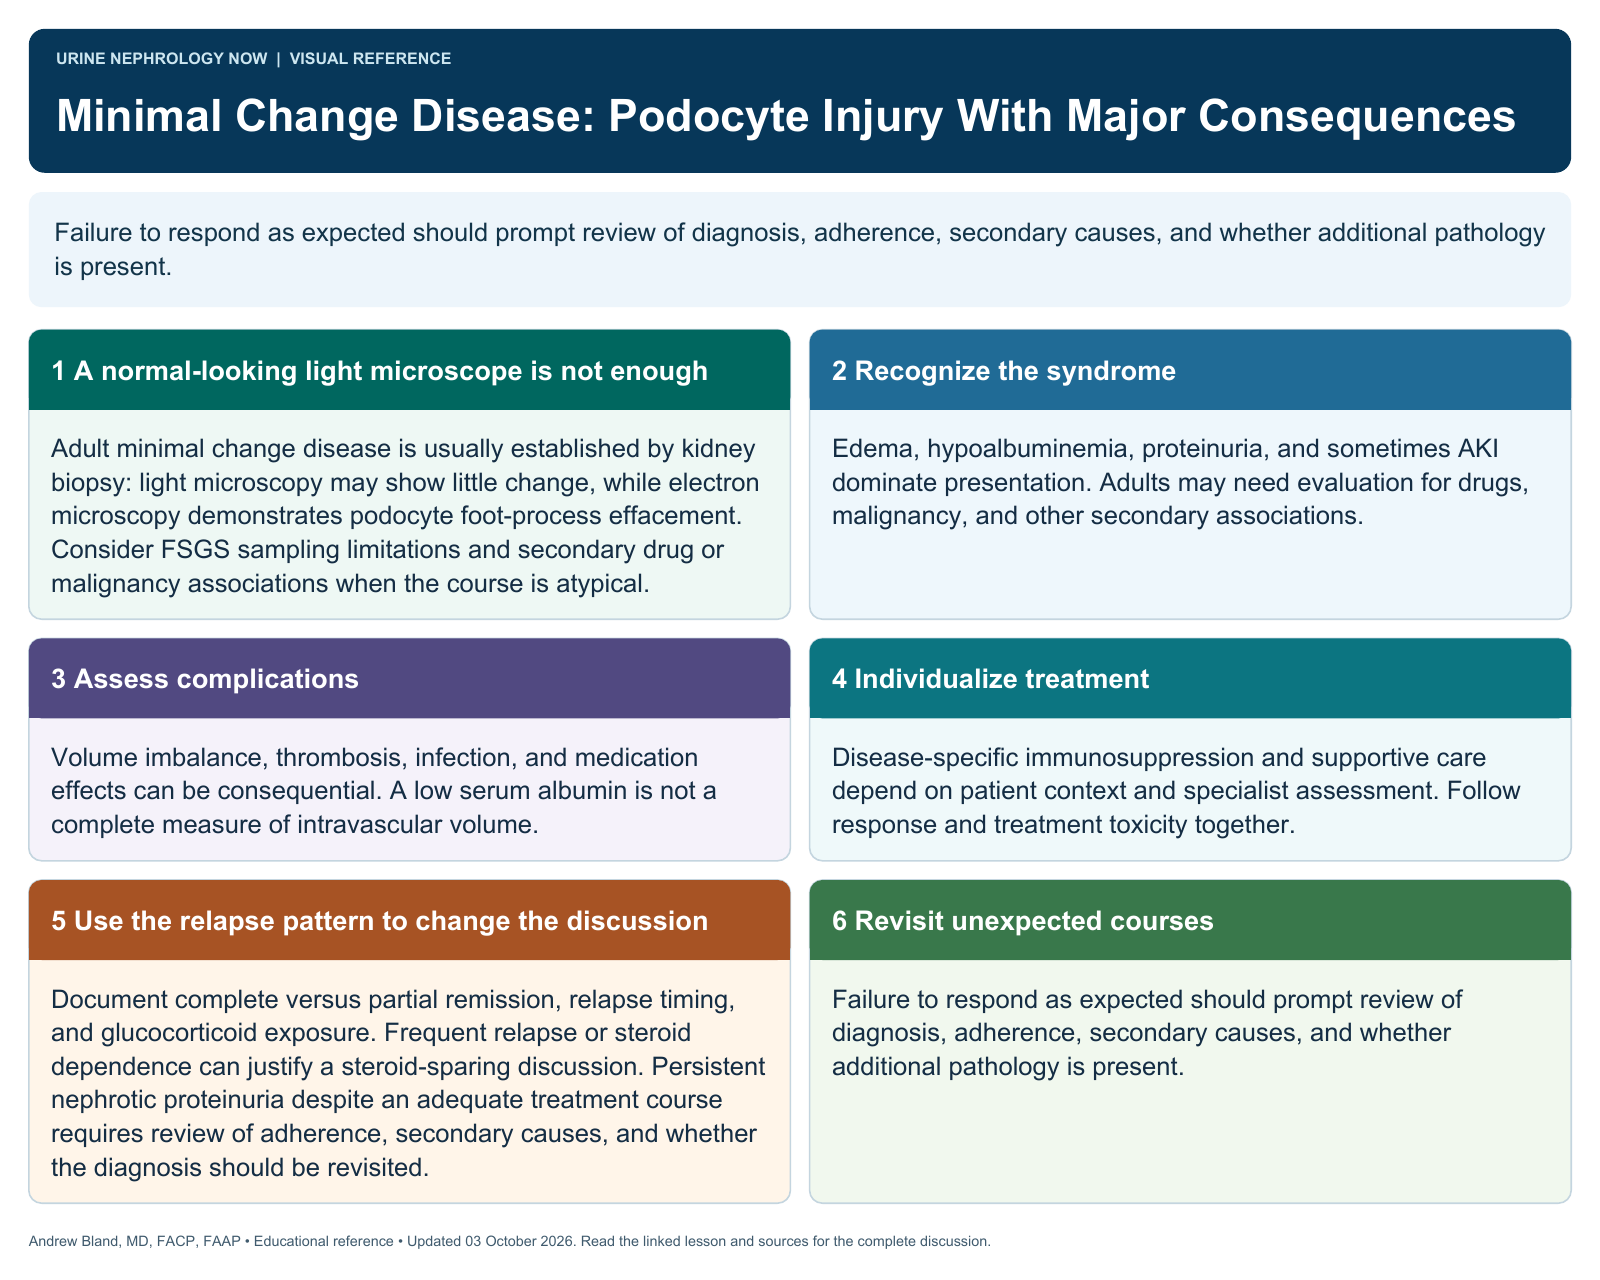
A normal-looking light microscope is not enough
Adult minimal change disease is usually established by kidney biopsy: light microscopy may show little change, while electron microscopy demonstrates podocyte foot-process effacement. Consider FSGS sampling limitations and secondary drug or malignancy associations when the course is atypical.
Recognize the syndrome
Edema, hypoalbuminemia, proteinuria, and sometimes AKI dominate presentation. Adults may need evaluation for drugs, malignancy, and other secondary associations.
Assess complications
Volume imbalance, thrombosis, infection, and medication effects can be consequential. A low serum albumin is not a complete measure of intravascular volume.
Individualize treatment
Disease-specific immunosuppression and supportive care depend on patient context and specialist assessment. Follow response and treatment toxicity together.
Use the relapse pattern to change the discussion
Document complete versus partial remission, relapse timing, and glucocorticoid exposure. Frequent relapse or steroid dependence can justify a steroid-sparing discussion. Persistent nephrotic proteinuria despite an adequate treatment course requires review of adherence, secondary causes, and whether the diagnosis should be revisited.
Revisit unexpected courses
Failure to respond as expected should prompt review of diagnosis, adherence, secondary causes, and whether additional pathology is present.