Visual summary
Confirm the amyloid type before assigning prognosis or selecting disease-specific therapy.
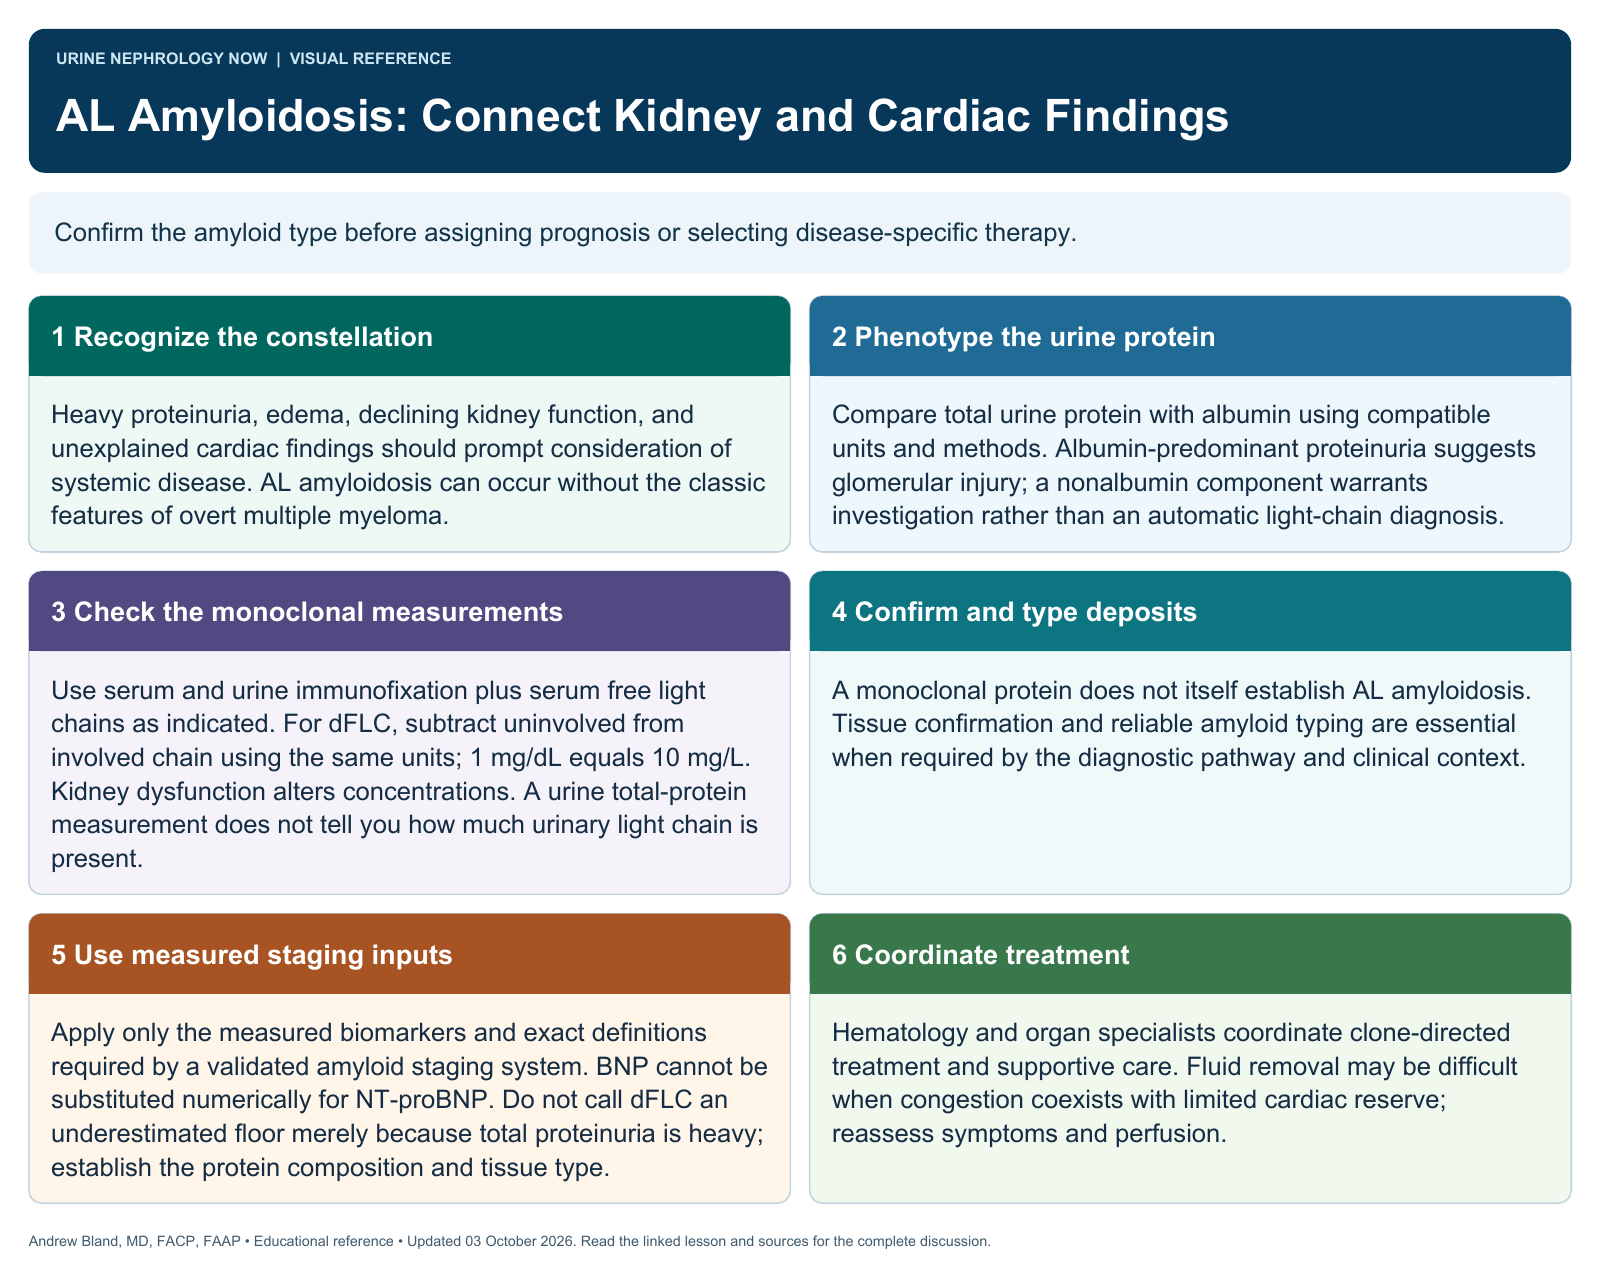
Text version
Recognize the constellation
Heavy proteinuria, edema, declining kidney function, and unexplained cardiac findings should prompt consideration of systemic disease. AL amyloidosis can occur without the classic features of overt multiple myeloma.
Phenotype the urine protein
Compare total urine protein with albumin using compatible units and methods. Albumin-predominant proteinuria suggests glomerular injury; a nonalbumin component warrants investigation rather than an automatic light-chain diagnosis.
Interpret monoclonal tests
Use serum and urine immunofixation with free light chains as appropriate. Kidney dysfunction changes light-chain concentrations and reference intervals. Check units before calculating ratios or differences.
Confirm and type deposits
A monoclonal protein does not itself establish AL amyloidosis. Tissue confirmation and reliable amyloid typing are essential when required by the diagnostic pathway and clinical context.
Assess organ involvement
Integrate cardiac imaging, biomarkers, hemodynamics, and kidney findings. BNP and NT-proBNP are not interchangeable. Use the exact assays and definitions required by a validated staging system.
Coordinate treatment
Hematology and organ specialists coordinate clone-directed treatment and supportive care. Fluid removal may be difficult when congestion coexists with limited cardiac reserve; reassess symptoms and perfusion.
Continue learning
This graphic summarizes a topic. The full educational pages provide the broader discussion and references.