KDIGO 2024 CKD · AHA/ACC/HFSA 2022 heart failure guidance · PARADIGM-HF — PubMed · ONTARGET — PubMed · ENTRESTO prescribing information
Read diagram text and evidence
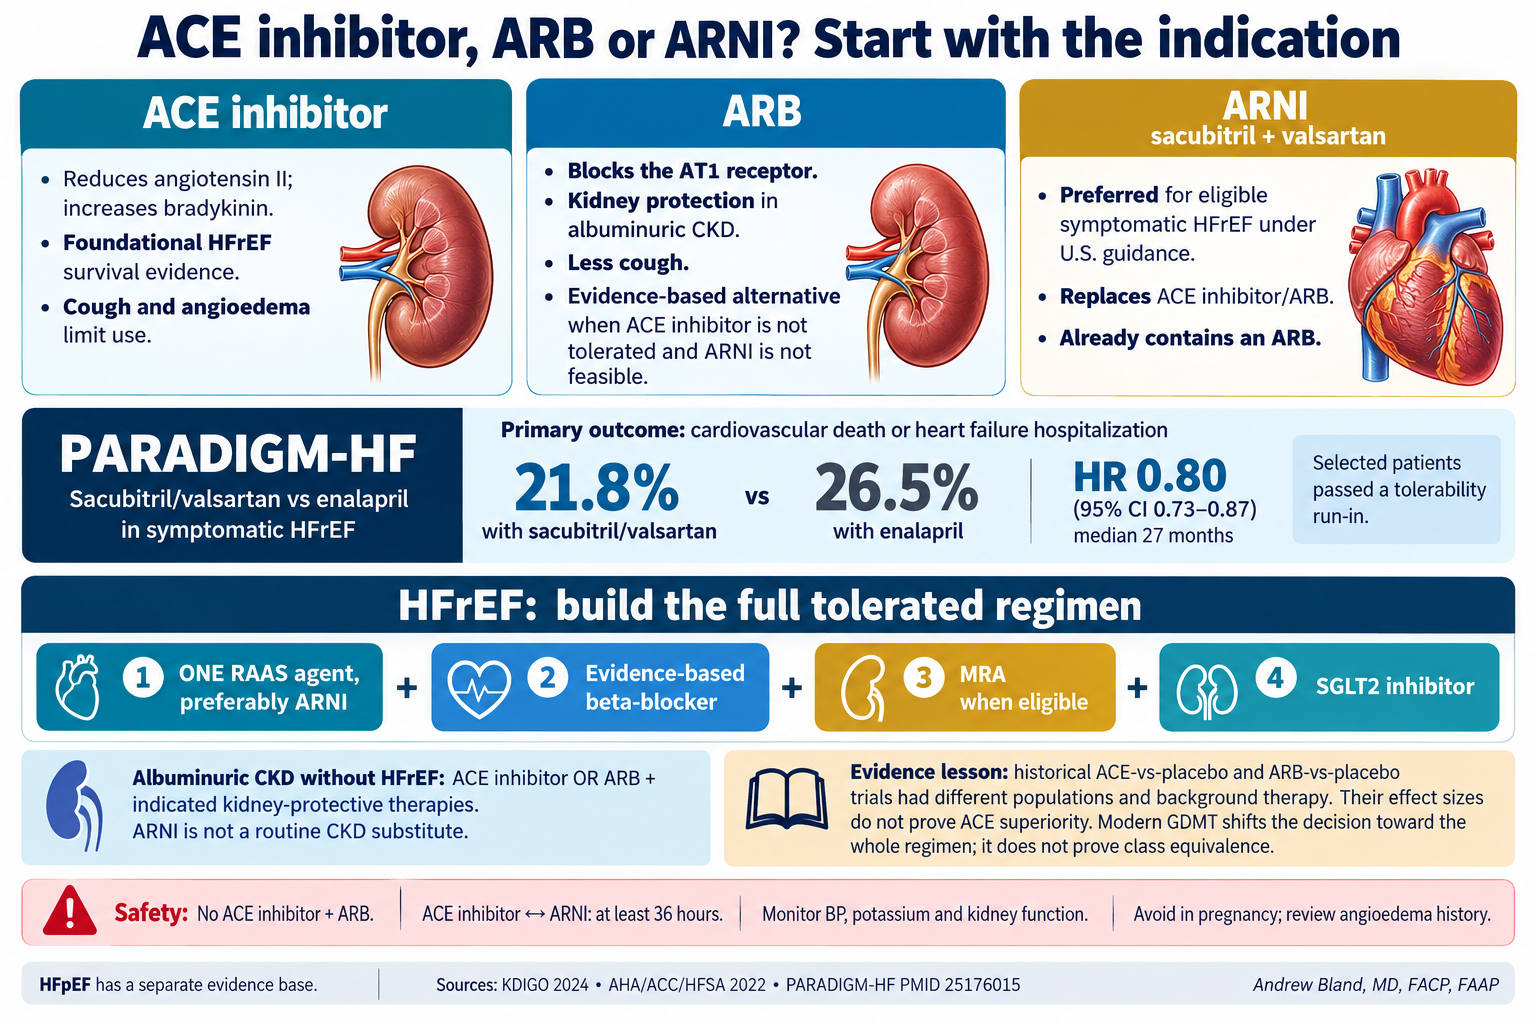
ACE inhibitors and ARBs are alternatives for indicated albuminuric CKD. ACE inhibitors increase bradykinin, contributing to cough and angioedema; ARBs generally cause less cough. For eligible symptomatic HFrEF, U.S. guidance prefers sacubitril/valsartan (ARNI), with an evidence-based beta-blocker, an eligible MRA and an SGLT2 inhibitor. An ARNI replaces the ACE inhibitor/ARB; it already contains valsartan. An ACE inhibitor remains an effective option when ARNI is not feasible, and an evidence-based ARB is an option when ACE inhibition is not tolerated. HFpEF has a separate evidence base.
PARADIGM-HF compared sacubitril/valsartan directly with enalapril: cardiovascular death or HF hospitalization occurred in 21.8% versus 26.5%, HR 0.80 (95% CI 0.73–0.87), over median 27 months, in patients who passed a tolerability run-in. It predated routine SGLT2 use. Historical ACE-versus-placebo and ARB-versus-placebo trials differ in populations, endpoints and background care, so comparing their effect sizes does not prove ACE superiority. Modern GDMT shifts the clinical focus to a complete tolerated regimen; it does not prove that its other drugs erase every possible ACE–ARB difference. ONTARGET supports telmisartan’s noninferiority to ramipril in its high vascular-risk population without heart failure, not universal class equivalence.
Do not combine ACE inhibitor and ARB or add a separate ARB to ARNI. Allow at least 36 hours between ACE inhibitor and ARNI in either direction. Review angioedema history and pregnancy, and monitor BP, potassium and kidney function. eGFR below 30 is not itself an ENTRESTO contraindication: the label specifies a reduced starting dose and close monitoring. For CKD without HFrEF, ARNI is not a routine substitute for ACE inhibitor/ARB solely to protect the kidney.
Andrew Bland, MD, FACP, FAAP