Follow the edema: locate the problem before escalating diuretics
Levick and Michel, revised Starling principle — PubMed · Ellison, 2019 — PubMed
Read diagram text and evidence
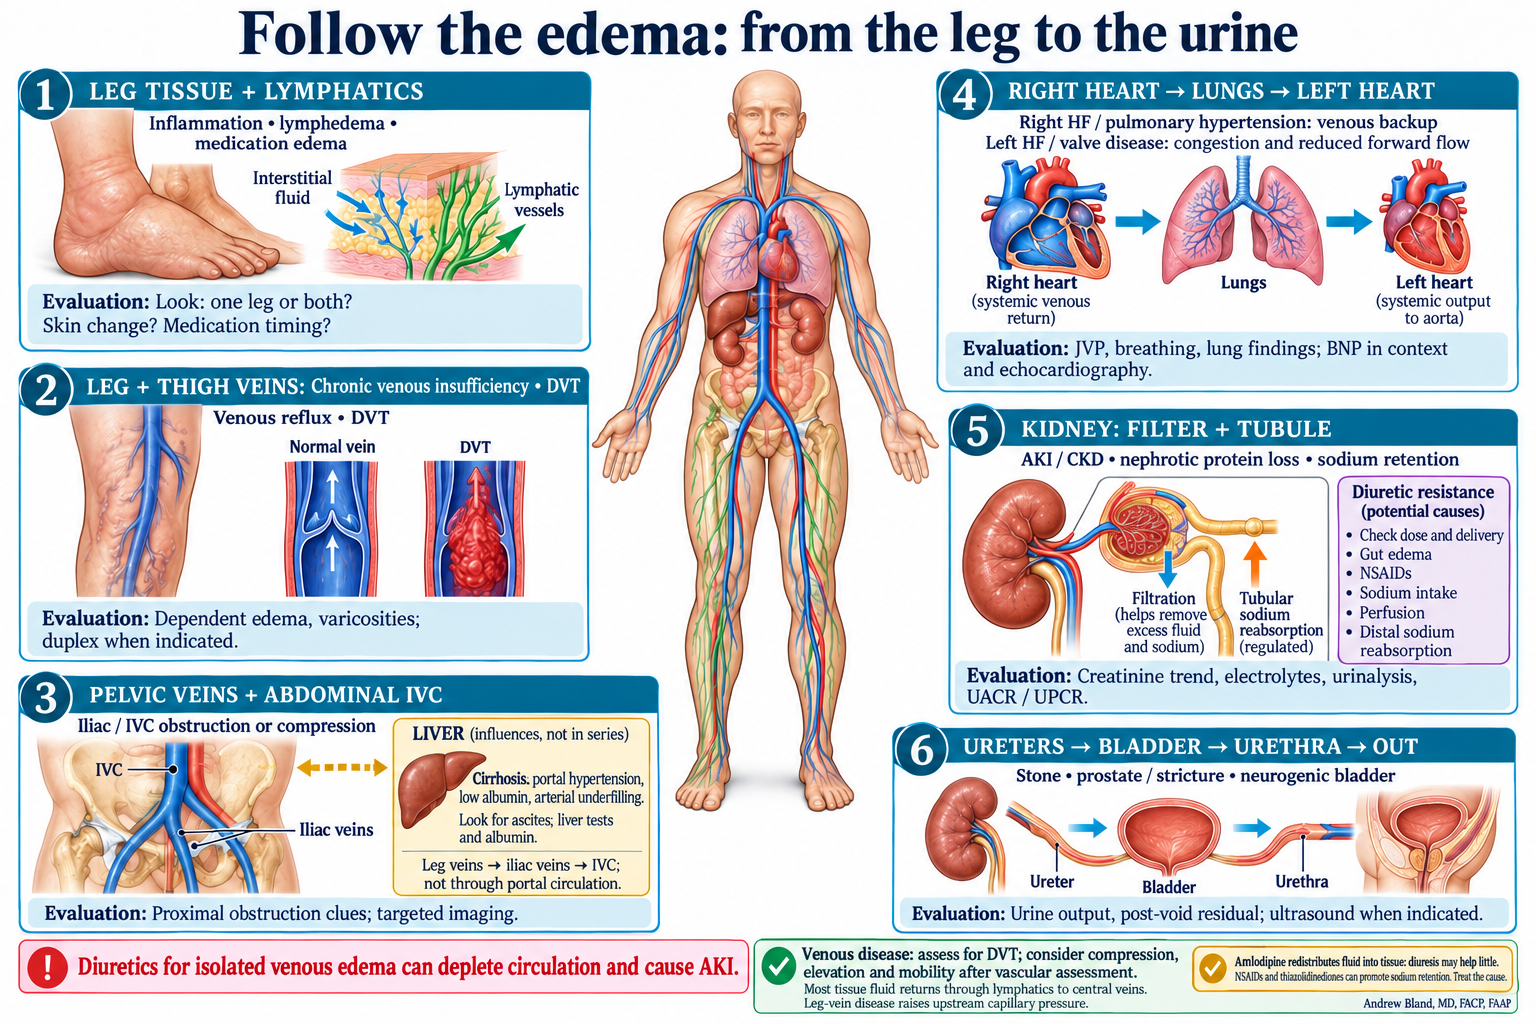
Follow the anatomical assessment sequence: leg interstitium and lymphatics; leg and thigh veins; pelvic veins and abdominal IVC; right heart, lungs and left heart; kidney filtration and tubules; ureters, bladder and urethra. This is an evaluation map, not a literal claim that tissue fluid is normally reabsorbed into local leg veins. Most filtered tissue fluid returns through lymphatics to central veins. Leg venous blood travels through the iliac veins and IVC, not through the portal liver in series.
Look for medication-related edema, inflammation and lymphatic failure; chronic venous insufficiency, DVT or proximal venous obstruction; cirrhosis with portal hypertension, reduced albumin and arterial underfilling; right or left heart failure; kidney disease and sodium retention; impaired diuretic delivery or response; and urinary obstruction including neurogenic bladder. Amlodipine can redistribute fluid into tissues; NSAIDs and thiazolidinediones can promote sodium retention. Match treatment to mechanism.
Assess onset, one leg versus both, pain, skin changes and medication timing. Suspected acute DVT needs prompt clinical assessment and an appropriate diagnostic pathway, often venous duplex; dyspnea or chest pain raises concern for pulmonary embolism. For chronic venous insufficiency, consider elevation, mobility and appropriately selected compression after vascular assessment. Diuretics for isolated venous edema without systemic volume overload can deplete the circulation and cause AKI. Venous disease and systemic congestion can coexist, so reassess rather than treating edema or creatinine alone.
Andrew Bland, MD, FACP, FAAP
Levick and Michel, revised Starling principle — PubMed · Ellison, 2019 — PubMed
Read diagram text and evidence
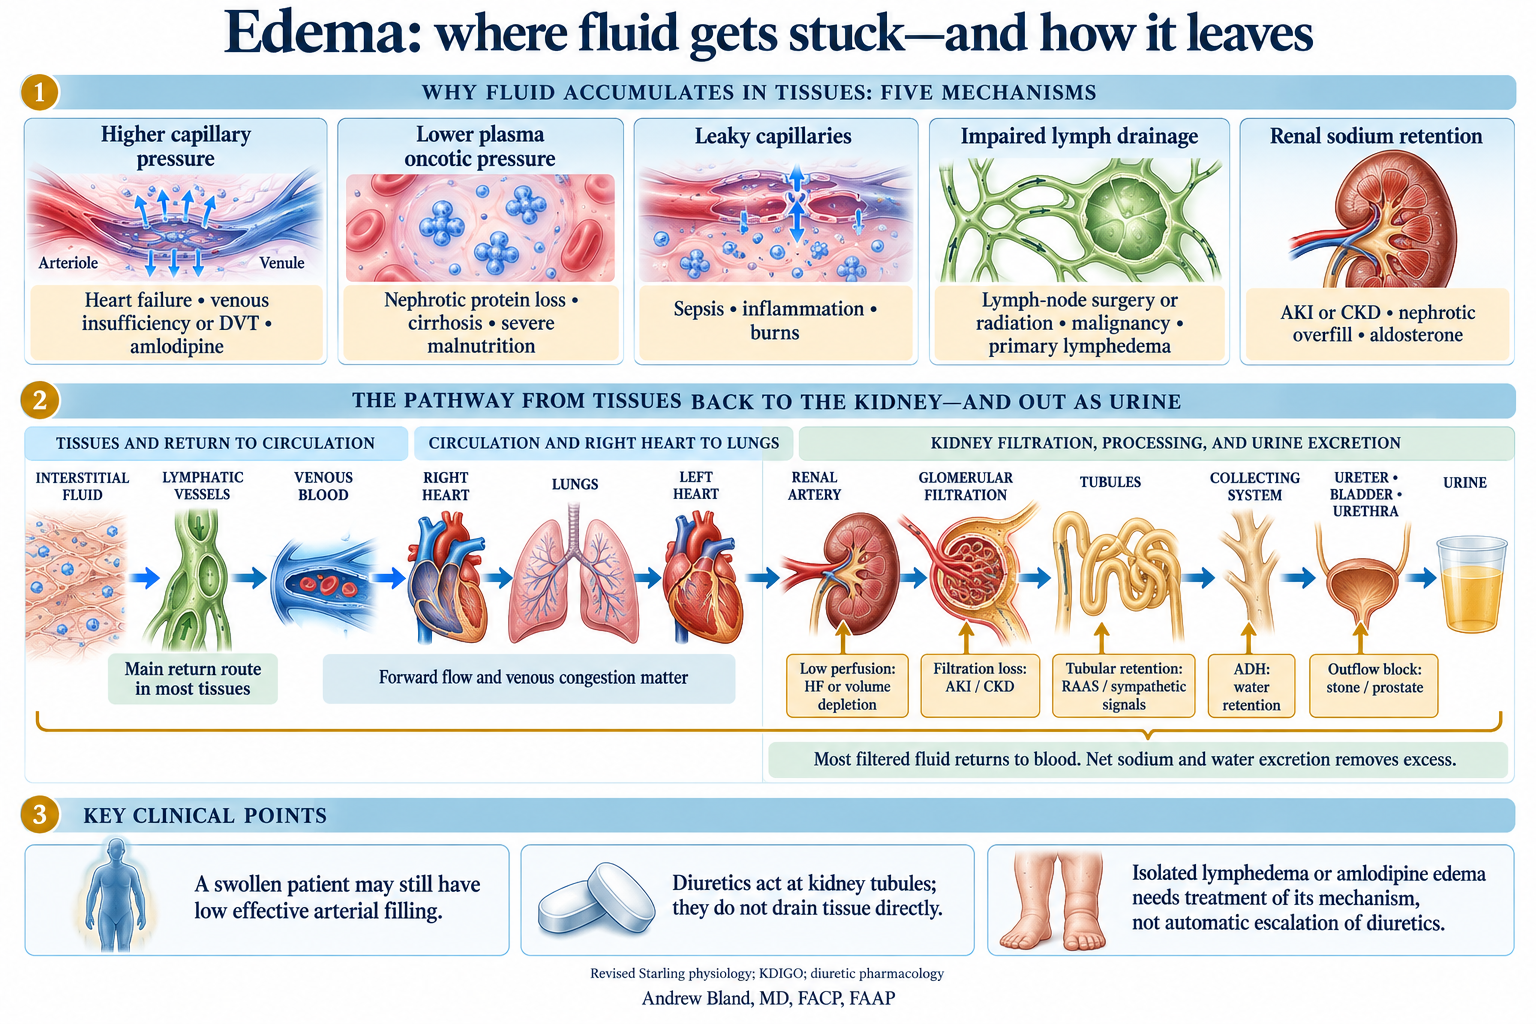
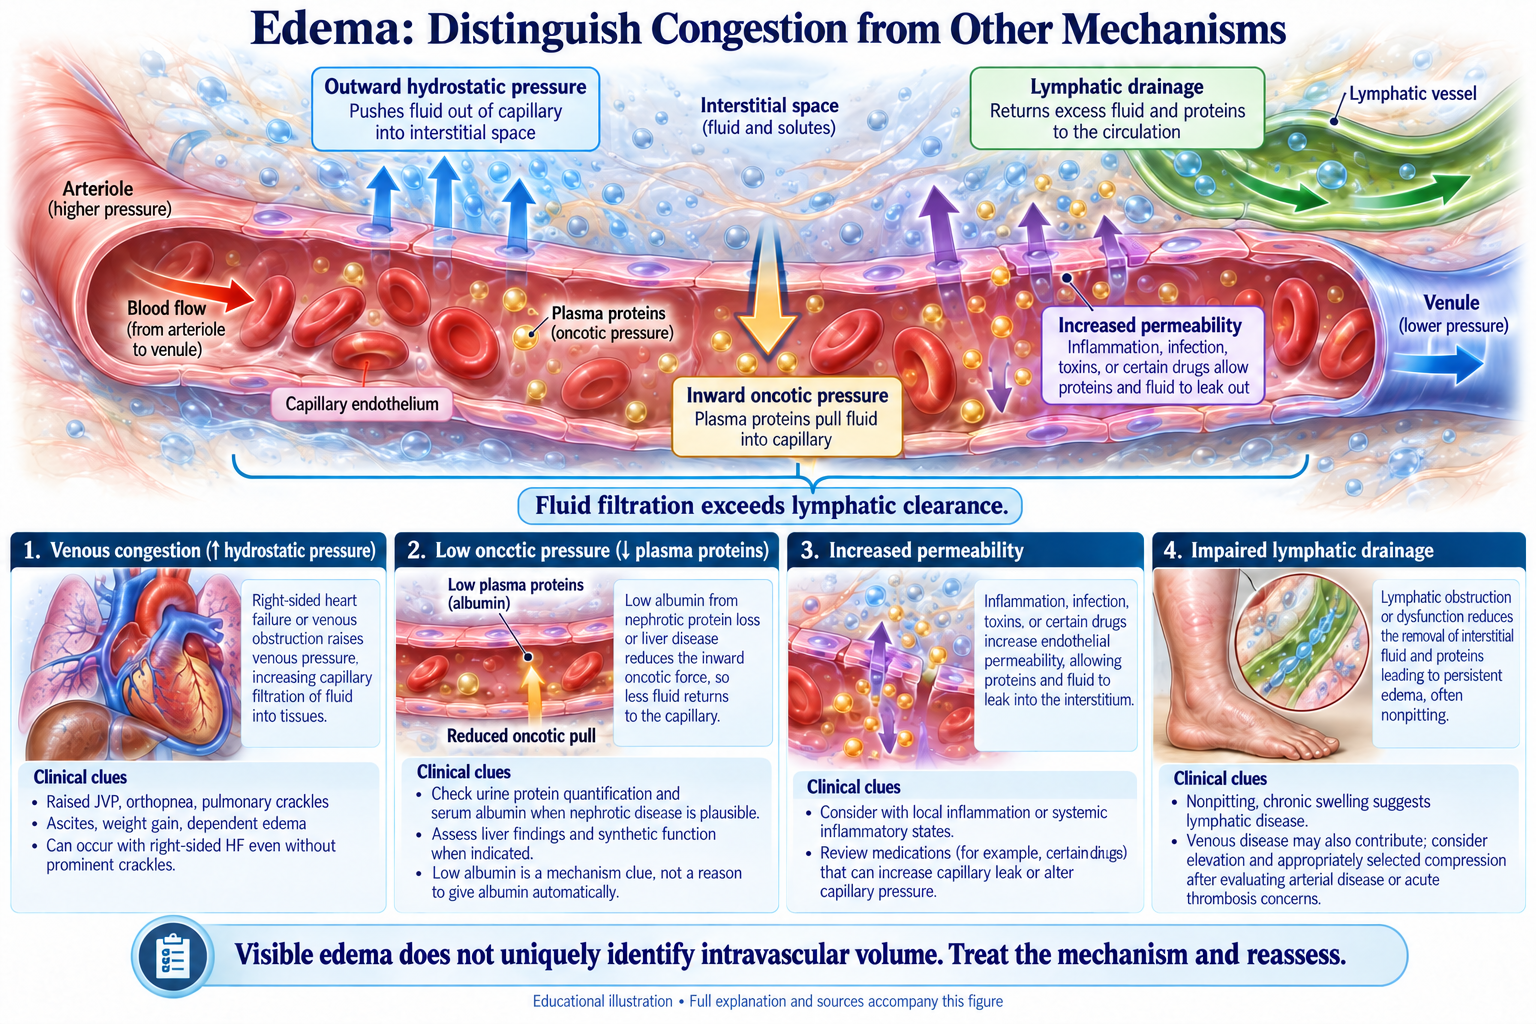
Edema reflects excess filtration or inadequate lymphatic return: increased hydrostatic pressure, reduced plasma oncotic pressure, increased permeability, lymphatic obstruction, and renal sodium retention can overlap. Fluid must return to the circulation before the kidneys can excrete it. Assess the circulation, kidney response and urinary outflow; more diuretic is not a universal answer.
Andrew Bland, MD, FACP, FAAP
💧 Edema: The Circulation Cycle Approach
Understanding edema through the fluid return pathway to the kidneys
Visual reference
Browse the visual reference library · Download lesson Markdown
Three routes to edema
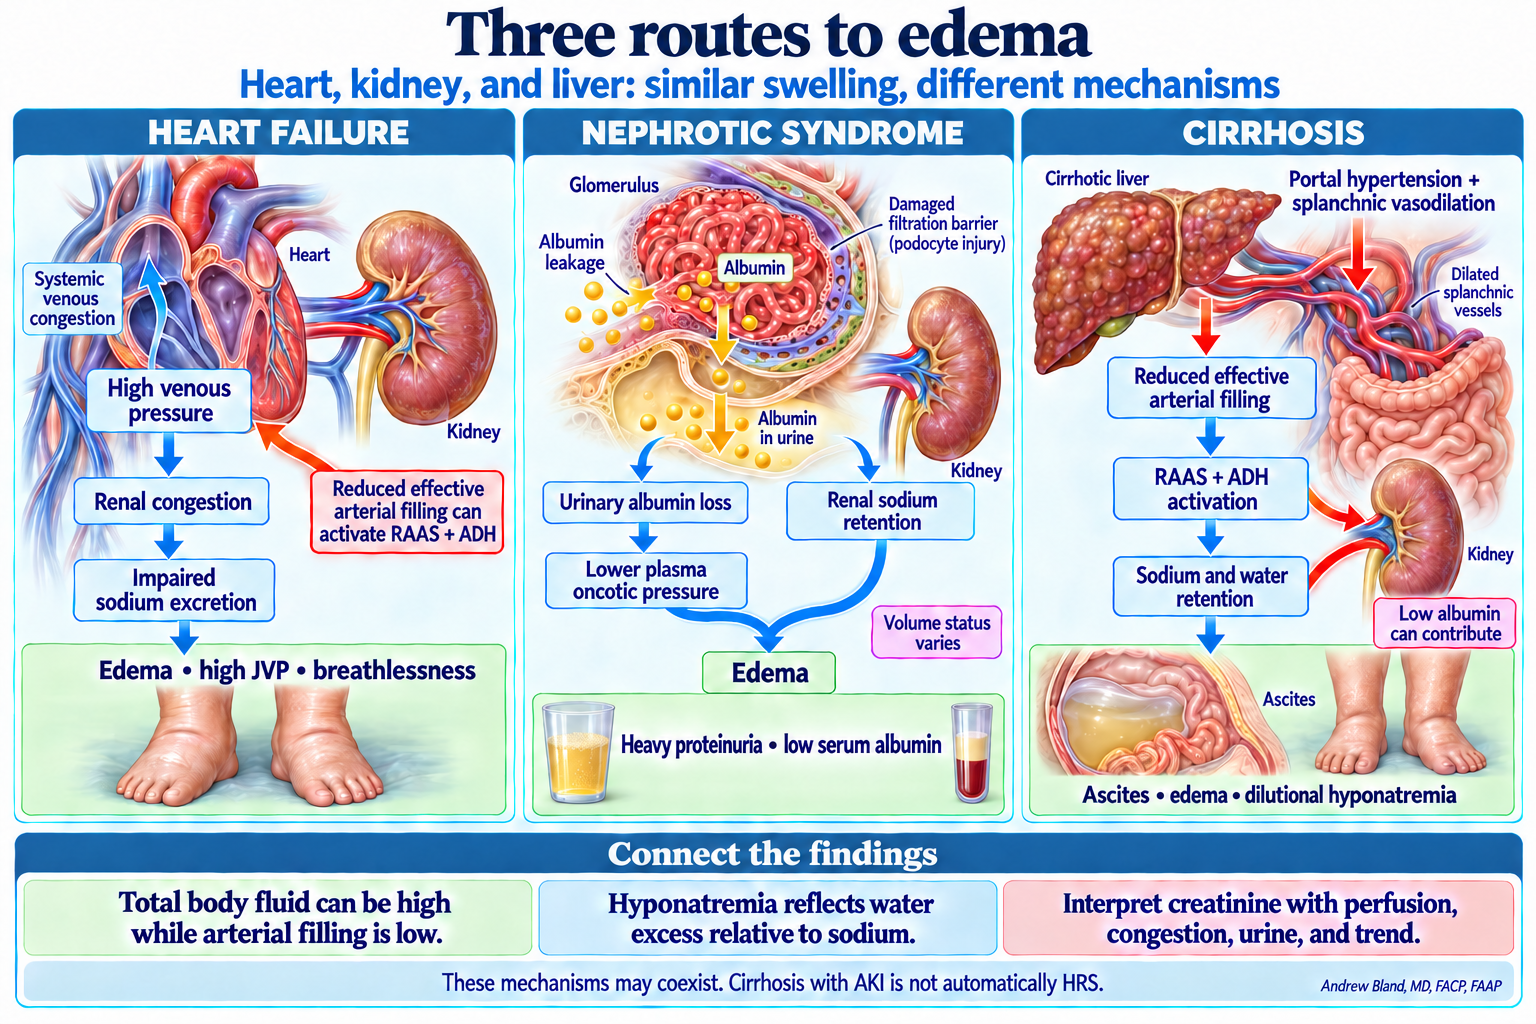
Compare the mechanisms behind a swollen patient before deciding what the creatinine rise means.
🎯 Learning Objectives
Upon completion, you will be able to:
- Trace the complete circulation pathway from leg edema to kidney
- Identify where disruptions cause AKI before edema resolution
- Analyze how each pathological condition interrupts fluid circulation
- Predict which patients are at highest risk for diuretic-induced AKI
Advanced Clinical Skills:
- Assess circulation integrity before initiating diuretics
- Recognize high-risk scenarios for renal compromise
- Apply targeted therapy based on circulation bottlenecks
- Monitor for AKI during edema treatment
🔄 The Central Concept: Fluid Must Complete the Full Circulation Cycle
The Complete Journey from Leg to Urine
1️⃣ LEG
Interstitial fluid
Starting point
2️⃣ VEINS & LYMPH
Uptake into circulation
Critical first step
3️⃣ THIGH
Venous return
Gravity challenge
4️⃣ ABDOMEN
IVC transport
Compression risk
5️⃣ RIGHT HEART
Venous processing
Volume handling
6️⃣ LEFT HEART
Systemic circulation
Pressure generation
7️⃣ KIDNEYS
Filtration & processing
Final elimination
8️⃣ URINE
Fluid elimination
Mission accomplished
⚠️ Critical Clinical Insight
Any disruption in this pathway can cause AKI BEFORE the edema resolves. When we give diuretics, we're asking the kidneys to eliminate fluid that may not be able to reach them due to circulation bottlenecks. This creates a dangerous scenario where we worsen kidney function while the edema persists.
⚠️ Where AKI Develops Before Edema Resolution
High-Risk Circulation Bottlenecks
🚫 Venous Outflow Obstruction
- Severe venous insufficiency
- IVC compression/thrombosis
- Massive ascites with abdominal compartment syndrome
❤️ Right Heart Failure
- Severe tricuspid regurgitation
- Pulmonary hypertension (COPD, sleep apnea)
- RV dysfunction from any cause
Moderate-Risk Scenarios
🔄 Left Heart Limitations
- Severe systolic dysfunction (EF <30%)
- Diastolic dysfunction with elevated filling pressures
- Critical aortic stenosis
🧪 Low Oncotic Pressure
- Severe hypoalbuminemia (<2.5 g/dL)
- Nephrotic syndrome
- Liver failure
🎯 Clinical Decision Point
Before starting diuretics, assess: Can this patient's circulation system handle the fluid mobilization and transport to the kidneys? If not, address the bottleneck first or use extreme caution with gradual diuresis and frequent monitoring.
🔍 How Specific Conditions Disrupt the Circulation Cycle
Venous Insufficiency
Pathophysiology:
- Incompetent venous valves
- Elevated venous pressure in legs
- Impaired venous return against gravity
- Chronic venous hypertension
Portal Hypertension
Pathophysiology:
- Increased portal venous pressure
- Splanchnic vasodilation
- Ascites formation and third-spacing
- Effective arterial blood volume depletion
Bladder Obstruction
Pathophysiology:
- Elevated bladder pressure
- Increased tubular pressure
- Reduced net filtration pressure
- Progressive renal dysfunction
Right Heart Failure
Pathophysiology:
- Elevated right atrial pressure
- Systemic venous congestion
- Renal venous congestion
- Reduced cardiac output
Tricuspid Regurgitation
Pathophysiology:
- Volume overload of right ventricle
- Progressive annular dilation
- Worsening regurgitant fraction
- Ineffective forward flow
Pulmonary Hypertension (COPD/OSA)
Pathophysiology:
- Elevated pulmonary vascular resistance
- Right heart strain and failure
- Impaired left heart filling
- Reduced systemic cardiac output
Left Heart Failure
Pathophysiology:
- Reduced systolic function
- Elevated filling pressures
- Neurohormonal activation
- Renal hypoperfusion
Diuretic Resistance/Renal Disease
Pathophysiology:
- Reduced nephron mass
- Impaired sodium excretion
- Tubular adaptation to diuretics
- Gut edema reducing oral absorption
💊 Drug-Induced Edema: Circulation Perspective
⚠️ Understanding Drug Edema Through Circulation Disruption
Drug-induced edema typically disrupts the circulation cycle at specific points, making it important to understand the mechanism before choosing treatment.
NSAIDs
- Frequency: Usually mild, 1-2 kg weight gain
- Onset: Within first week of use
- AKI Risk: Low in healthy patients, higher with CKD
- Treatment: Discontinuation usually resolves both edema and any renal impairment
Calcium Channel Blockers
- Amlodipine: ~16% experience swollen feet
- Dose-related: approximately 3% at 2.5 mg, approximately 10% at 5 mg, up to 25-40% at 10 mg (per prescribing information and published data)
- AKI Risk: Very low (circulation upstream is intact)
- Treatment: ARB/ACEi combination reduces risk; diuretics usually effective
Thiazolidinediones (TZDs)
- Frequency: <5% overall, 15% when combined with insulin
- Risk: Both TZDs carry similar HF risk (pooled RR 1.72, Lago 2007 PMID 17905165); rosiglitazone withdrawn for CV risk but HF signal was comparable
- AKI Risk: Moderate, especially in heart failure patients
- Treatment: Diuretics effective but monitor for volume depletion
Gabapentinoids
- Gabapentin: 1-10% frequency (common side effect)
- Pregabalin: Higher rates than gabapentin
- AKI Risk: Very low
- Treatment: Often resolves with dose reduction; diuretics if needed
Alpha Blockers
- Common agents: Doxazosin, prazosin, terazosin
- Frequency: 5-10% of patients, dose-dependent
- Pattern: Dependent edema, worse with prolonged standing
- AKI Risk: Low to moderate (can cause hypotension)
Less Common but Important Causes
Hormonal Agents
- Estrogen-containing contraceptives: Enhanced sodium retention
- Corticosteroids: Mineralocorticoid effects (facial, abdominal, legs)
Antineoplastic Drugs
- Variable mechanisms by drug class
- Generally mild, resolves post-treatment
- Diuretics: Limited effectiveness, focus on supportive care
Unusual Causes
- Dopamine agonists (pramipexole) - vascular effects
- IL-6 inhibitors (tocilizumab) - inflammatory modulation
- PDE inhibitors (sildenafil) - vasodilation
- Anti-VEGF agents - paradoxical edema
- MAOIs (phenelzine) - vascular permeability
🩺 Comprehensive Edema Workup
🎯 Clinical Approach
Before initiating diuretics, perform a systematic evaluation to identify circulation bottlenecks and optimize treatment strategy.
📸 Essential Imaging
🫀 Echocardiogram (Priority #1)
- Right heart function: RV size, function, TAPSE, tricuspid regurgitation
- Left heart function: EF, diastolic function, wall motion
- Valvular disease: Especially tricuspid and mitral regurgitation
- Filling pressures: E/e' ratio, IVC size and respiratory variation
🫘 Renal Ultrasound with PVR
- Kidney size/echogenicity: CKD assessment
- Hydronephrosis: Obstruction evaluation
- Post-void residual (PVR): Bladder emptying function
- Renal artery Doppler: If renovascular disease suspected
🧪 Laboratory Assessment
🩸 Renal Function Panel (RFP)
- Creatinine & eGFR: Baseline kidney function
- BUN: Volume status assessment (BUN/Cr ratio)
- Electrolytes: Na, K, Cl, CO2 - baseline before diuretics
- Phosphorus & Magnesium: CKD-MBD evaluation
🧬 Liver Function Tests
- ALT, AST: Hepatocellular injury
- Alkaline phosphatase, GGT: Cholestatic pattern
- Total bilirubin: Liver synthetic function
- Albumin: Synthetic function & oncotic pressure assessment
- PT/INR: Synthetic function assessment
💧 Urinalysis (UA) with Microscopy
- Proteinuria: Nephropathy/glomerular disease
- Hematuria: Glomerulonephritis vs. other causes
- Casts: RBC casts (glomerular), granular casts (tubular)
- Specific gravity: Concentrating ability
🥛 Protein & Oncotic Pressure
📊 Albumin/Creatinine Ratio (ACR)
- <30 mg/g: Normal
- 30-300 mg/g: Microalbuminuria
- >300 mg/g: Macroalbuminuria
- >3000 mg/g: Nephrotic range
🧪 Serum Albumin
- >3.5 g/dL: Normal oncotic pressure
- 2.5-3.5 g/dL: Mild hypoalbuminemia
- <2.5 g/dL: Significant - consider albumin co-administration
- <2.0 g/dL: Severe - albumin replacement indicated
👩⚕️ Clinical Evaluation
💊 Comprehensive Medication Review
- Calcium channel blockers: Amlodipine, nifedipine
- NSAIDs: Including selective COX-2 inhibitors
- Thiazolidinediones: Pioglitazone, rosiglitazone
- Gabapentinoids: Gabapentin, pregabalin
- Alpha blockers: Doxazosin, prazosin
- Hormones: Estrogen, corticosteroids
🦵 Venous Insufficiency Assessment
- Skin changes: Hyperpigmentation, lipodermatosclerosis
- Varicose veins: Superficial and deep system
- Edema pattern: Unilateral vs bilateral, pitting quality
- Pulses: Arterial adequacy assessment
- Unilateral edema
- Skin changes present
- History of DVT/PE
- Poor response to standard therapy
🔬 Additional Testing (When Indicated)
🫁 Pulmonary Assessment
- Chest X-ray: Pulmonary edema, pleural effusions
- BNP/NT-proBNP: Heart failure biomarker
- ABG: If hypoxemic or hypercapnic
- Sleep study: OSA contributing to pulmonary HTN
🧬 Specialized Testing
- Thyroid function: Hypothyroidism causing edema
- Protein electrophoresis: Nephrotic syndrome workup
- ANA, complement: Autoimmune glomerulonephritis
- Hepatitis panel: Viral hepatitis causing cirrhosis
⚖️ AKI Risk Stratification
🟢 LOW RISK
- Normal echo (EF >50%, normal RV function)
- eGFR >45 mL/min/1.73m²
- Albumin >2.5 g/dL
- No venous congestion signs
- Drug-induced edema
🟡 MODERATE RISK
- Mild heart failure (EF 35-50%)
- eGFR 30-45 mL/min/1.73m²
- Albumin 2.0-2.5 g/dL
- Mild venous congestion
🔴 HIGH RISK
- Severe heart failure (EF <35% or RV dysfunction)
- eGFR <30 mL/min/1.73m²
- Albumin <2.0 g/dL
- Severe venous congestion/ascites
- Cirrhosis or obstruction
📋 Edema Workup Checklist
🎯 Circulation-Based Treatment Strategy
Assess Circulation Integrity
Risk-Based Treatment Approach
🚨 Stop Diuretics If:
🧮 Albumin Co-administration Decision Tool
Recommendation will appear here
Clinical Evidence by Albumin Level
💎 Circulation-Based Clinical Pearls
Pre-Diuretic Assessment
Always assess the complete circulation pathway before starting diuretics. Ask: "Can the fluid physically reach the kidneys for elimination?"
AKI Warning Signs
Rising creatinine with persistent edema suggests circulation bottleneck. The problem isn't kidney function—it's fluid delivery to the kidneys.
Right Heart Priority
In bilateral edema, assess right heart function first. Right heart failure creates the highest AKI risk with diuretic therapy.
Venous Congestion Recognition
Elevated JVD with peripheral edema suggests venous congestion may be more important than low cardiac output in causing renal dysfunction.
📚 Sources
- Lago RM, Singh PP, Nesto RW. Congestive heart failure and cardiovascular death in patients with prediabetes and type 2 diabetes given thiazolidinediones: a meta-analysis of randomised clinical trials. Lancet. 2007;370(9593):1129-1136. PMID: 17905165. — TZD heart-failure risk meta-analysis; pooled HF risk RR 1.72 (95% CI 1.21-2.42) — applies similarly to rosiglitazone and pioglitazone, no significant inter-drug differential. Replaces the lecture's unsourced "OR 3.75 vs 2.42" claim with the actual published numbers.
- Heidenreich PA, Bozkurt B, Aguilar D, et al. 2022 AHA/ACC/HFSA Guideline for the Management of Heart Failure. J Am Coll Cardiol. 2022;79(17):e263-e421. PMID: 35379503. — Diuretic management framework, edema management in HF.
- Mullens W, Damman K, Harjola VP, et al. The use of diuretics in heart failure with congestion. Eur J Heart Fail. 2019;21(2):137-155. PMID: 30600580. — HFA position paper on diuretic use in HF; sequential nephron blockade framework.
- Felker GM, Ellison DH, Mullens W, et al. Diuretic Therapy for Patients with Heart Failure: JACC State-of-the-Art Review. J Am Coll Cardiol. 2020;75(10):1178-1195. PMID: 32164892. — Diuretic resistance, sequential blockade, albumin co-administration.
- Lee TH, Kuo G, Chang CH, et al. Diuretic effect of co-administration of furosemide and albumin: an updated systematic review and meta-analysis. PLoS One. 2021;16(12):e0260312. PMID: 34851962. — Albumin + furosemide co-administration evidence; +31 mL/hr urine output benefit; informs the lecture's albumin-replacement thresholds.
Drug-associated edema risk varies by agent, dose, comorbidity, and ascertainment. Compare the actual study population and endpoint; peripheral edema and heart-failure hospitalization are different outcomes.