SGLT2 Inhibitor-Associated Euglycemic Diabetic Ketoacidosis
Comprehensive Literature Review
Author: Andrew Bland, MD, FACP, FAAP
Visual reference
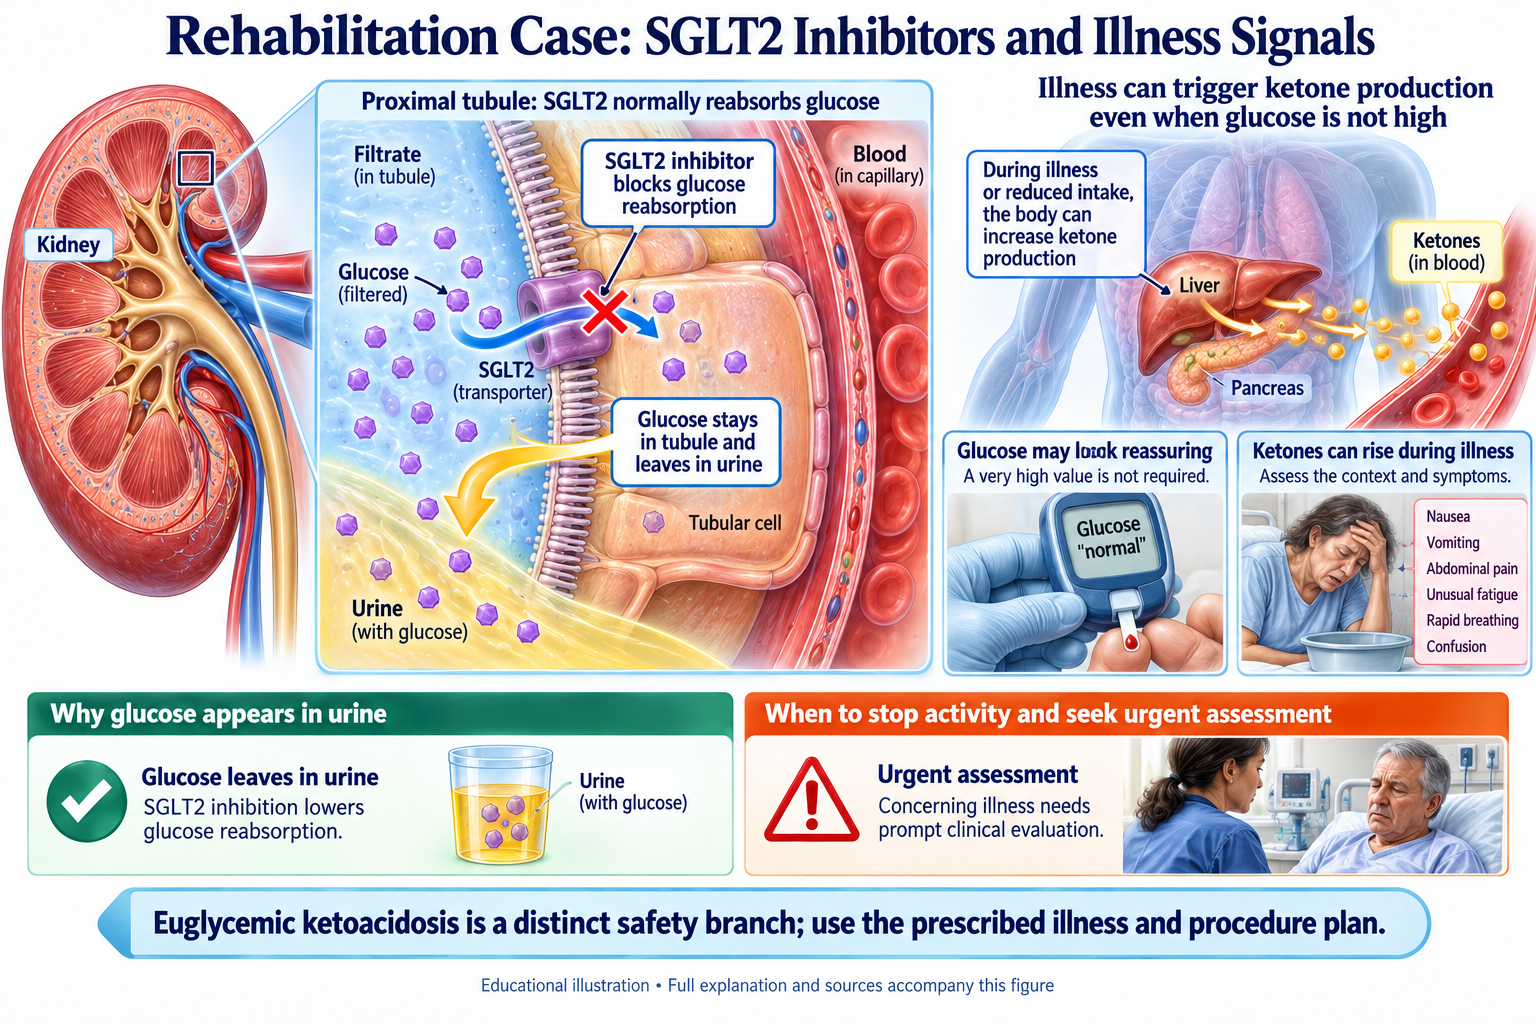
Browse the visual reference library · Download lesson Markdown
Abstract
This comprehensive literature review examines SGLT2 inhibitor-associated euglycemic diabetic ketoacidosis (euDKA), a rare but potentially life-threatening complication. The review synthesizes evidence from systematic reviews, meta-analyses, clinical trials, and case series to provide current understanding of epidemiology, pathophysiology, clinical manifestations, risk factors, prevention strategies, and management approaches.
Introduction
Sodium-glucose cotransporter-2 (SGLT2) inhibitors have emerged as cornerstone therapies not only for type 2 diabetes mellitus but also for heart failure and chronic kidney disease management. However, the incidence of euglycemic DKA (EDKA) has grown with the introduction of SGLT2 inhibitors. It presents a diagnostic challenge for physicians due to the variety of etiologies and normal blood glucose levels, often resulting in delayed diagnosis.
Euglycemic diabetic ketoacidosis (euDKA) represents a rare but potentially life-threatening complication characterized by:
- Euglycemia (blood glucose <250 mg/dL)
- Severe metabolic acidosis (arterial pH <7.3, serum bicarbonate <18 mEq/L)
- Ketonemia
Epidemiology and Incidence
Overall Incidence Rates
DKA associated with SGLT2 inhibitors has rates ranging from 0.16 to 0.76 events per 1,000 patient-years in patients with type 2 diabetes. A comprehensive systematic review and meta-analysis by Dutta et al. demonstrated a pooled relative risk of 3.70 (95% CI 2.58–5.29), with I² = 0% and statistically significant overall effect (P < 0.00001).
Real-World Data
A multicenter cohort study from Qatar reported that out of 9,940 T2D patients on SGLT2 inhibitors during 2015–2020, 43 developed DKA (0.43%). Of these, 25 developed euDKA whereas 18 had hyperglycemic DKA. Euglycemic presentations accounted for 58% of all SGLT2 inhibitor-associated DKA cases.
Meta-Analysis Findings
| Study | Population | Finding |
|---|---|---|
| 16-study systematic review (31,256 patients) | T2DM | DKA risk approximately 3× higher with SGLT2i (95% CI 1.36–3.63) |
| Colacci et al. (350,000+ subjects) | T2DM | 2× risk of DKA vs placebo; absolute rate ~1 per 1,000 person-years |
| Dutta et al. meta-analysis | T2DM | Pooled RR 3.70 (95% CI 2.58–5.29) |
Pathophysiology and Mechanism
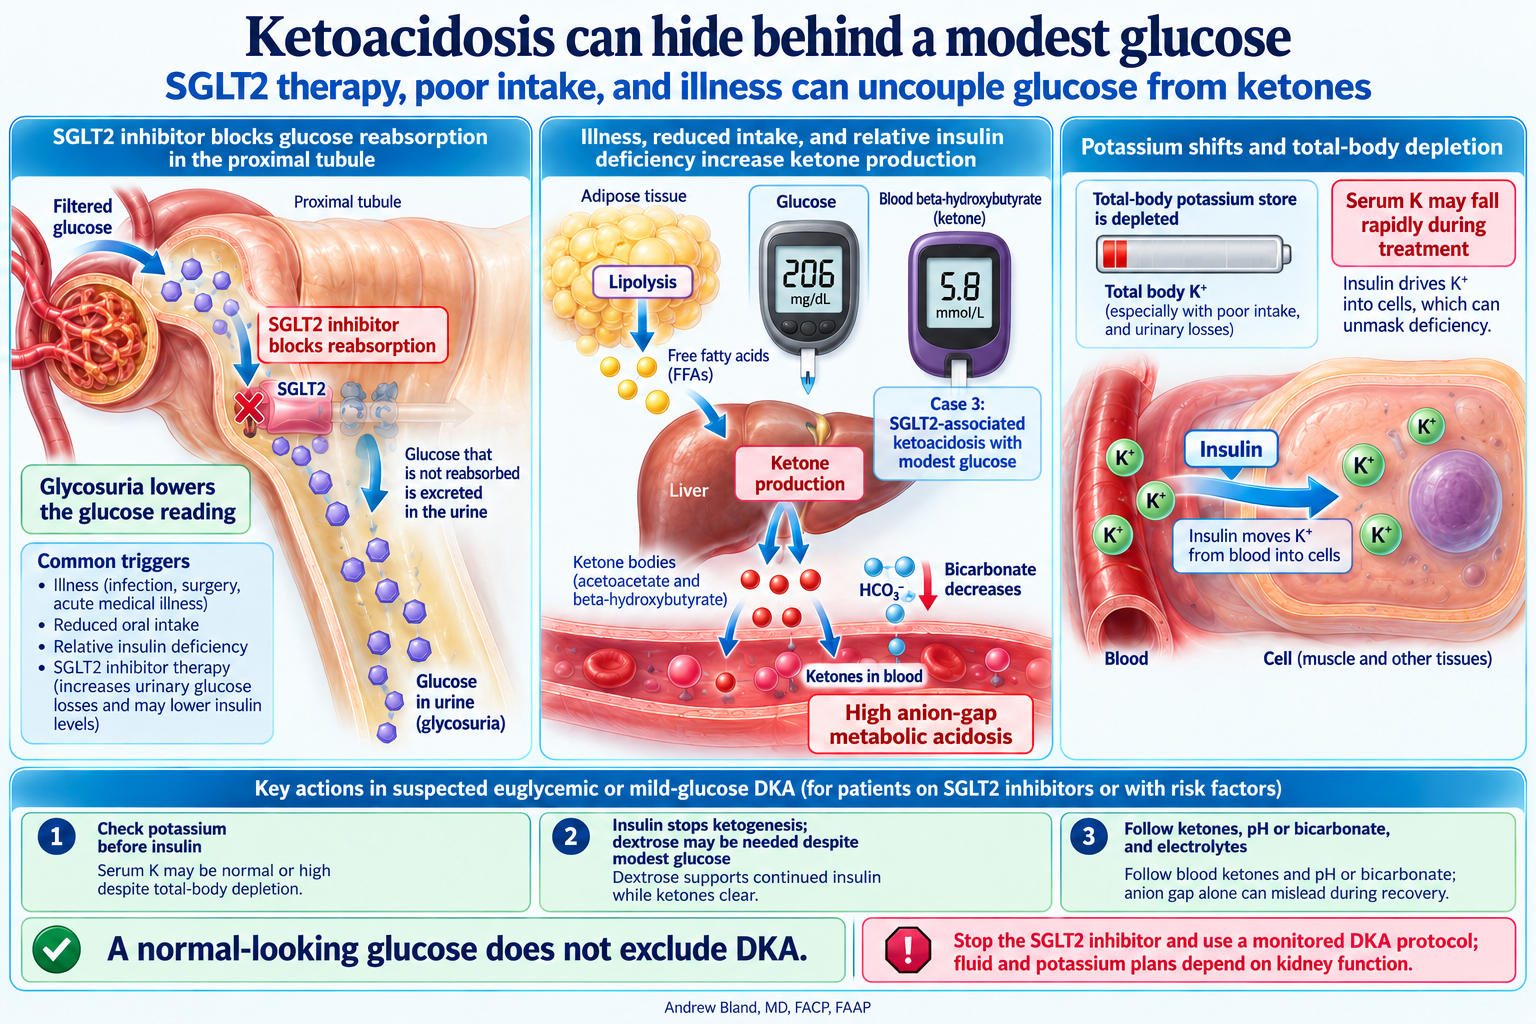
SGLT2 therapy, poor intake, and illness can uncouple glucose from ketones
Fundamental Mechanism
The pathophysiology involves a complex interplay of metabolic alterations. As glucose is the chief stimulus for insulin release, plasma insulin levels fall (by ~10 pmol/L fasting and ~60 pmol/L postmeal). Plasma glucagon concentrations increase significantly, partly because of diminished paracrine inhibition by insulin and possibly also because of decreased SGLT2-mediated glucose transport into alpha-cells.
Hormonal Changes
Ketogenesis Process
A decrease in blood glucose reduces insulin secretion from pancreatic beta-cells and stimulates glucagon secretion from alpha-cells. The increased glucagon-to-insulin ratio enhances gluconeogenesis along with lipolysis at the expense of carbohydrate oxidation, ultimately facilitating ketogenesis by shifting substrate usage from carbohydrates to lipids and ketone bodies.
The Glucose Paradox
Renal glucose clearance in standard DKA: 0.3 mL/min/kg
Renal glucose clearance is 2× higher with euDKA than with standard DKA — explaining the euglycemia
Clinical Manifestations
Diagnostic Challenges
Common Symptoms
euDKA could occur at any time during SGLT2 inhibitor treatment, with the main symptoms being:
- Nausea
- Abdominal pain
- Vomiting
- Generalized weakness
- Polyuria
- Fatigue
Diagnostic Criteria
pH ≤ 7.3
Bicarbonate ≤ 15 mmol/L
Anion gap > 12 mmol/L
Blood glucose < 14 mmol/L (<250 mg/dL)
Ketonemia present
Risk Factors
Patient Demographics
euDKA is commonly seen in middle-aged female T2DM patients taking SGLT2 inhibitors along with metformin.
Clinical Risk Factors
- Surgery (perioperative period is particularly high-risk)
- Infection / urosepsis
- Trauma or major illness
- Reduced food intake / starvation
- Persistent vomiting / gastroparesis
- Dehydration
- Reduction or discontinuation of insulin
- Low carbohydrate / ketogenic diet
- Heavy physical exercise (e.g., marathon)
- Excessive alcohol intake
Risk Stratification Factors
- Prior episodes of DKA
- Ketogenic diet
- Possible undiagnosed type 1 diabetes
- Current insulin requirement
Prevention Strategies
General Principles
SGLT2 inhibitor-associated DKA may be prevented by:
- Withholding SGLT2 inhibitors when precipitants develop
- Avoiding insulin omission or inappropriate insulin dose reduction
- Following sick day protocols as recommended
Patient Education
Patients should be counseled about activities that increase risk, such as intense exercise and excessive alcohol consumption. Patients should also be aware of the symptoms of DKA and know when to present to the emergency department.
Perioperative Management
Dose Considerations
International consensus recommendations suggest initiating SGLT2 inhibitor therapy at the lowest dose available. Some suggest even splitting tablets for currently marketed SGLT2 inhibitors to achieve lower-than-marketed doses for high-risk patients.
Management and Treatment
Acute Management
- Discontinue SGLT2 inhibitor immediately
- Early IV crystalloid resuscitation
- Prompt initiation of insulin infusion
- Concurrent dextrose infusion (critical difference from standard DKA — prevents hypoglycemia while maintaining insulin for ketoacidosis resolution)
Hospital Protocol Considerations
Monitoring Requirements
Guidelines and Recommendations
Professional Society Guidance
The current guidelines from the Endocrine Society and the American Diabetes Association advise providers to stop giving SGLT2 inhibitors to acutely hospitalized patients and to consider individual risk factors for DKA.
International Consensus
When initiating SGLT inhibitor therapy in individuals with type 1 diabetes, insulin must be reduced cautiously to prevent ketosis and DKA. These principles apply broadly to type 2 diabetes management as well.
Special Populations
Non-Diabetic Patients
Type 1 Diabetes
The use of SGLT2 inhibitors in T1DM is not recommended in the U.S. Studies consistently show higher risk in this population compared to type 2 diabetes patients.
Clinical Outcomes and Prognosis
While rare, euglycemic DKA can be life-threatening if unrecognized. EDKA can lead to serious complications, including significant dehydration, if not recognized early and treated appropriately with fluids, dextrose, and insulin. Early recognition and appropriate treatment typically result in favorable outcomes.
Most patients can safely resume SGLT2 inhibitor therapy after addressing precipitating factors, though this requires careful individual assessment.
Current Research and Future Directions
Animal studies suggest that low insulin levels and dehydration promote euDKA by raising serum catecholamine and corticosterone levels, leading to increased white adipose tissue lipolysis. Future research should focus on developing validated clinical prediction models to identify high-risk patients and optimize prevention strategies.
Conclusions
- The risk of DKA in patients receiving SGLT2 inhibitors increases by 3.7 times compared to other medications
- Normal or only mildly elevated glucose levels make traditional glucose-based screening insufficient
- Comprehensive patient education, careful risk stratification, and appropriate perioperative management are essential
- Before elective surgery, hold canagliflozin, dapagliflozin, or empagliflozin for at least 3 days and ertugliflozin for at least 4 days; resume only when clinically stable, eating, and free of ongoing ketoacidosis risk factors
- Despite associated risks, substantial cardiovascular and renal benefits support continued use with appropriate precautions
References
Primary Research and Systematic Reviews
- Dutta S, Kumar T, Singh S, Ambwani S, Charan J, Varthya SB. Euglycemic diabetic ketoacidosis associated with SGLT2 inhibitors: A systematic review and quantitative analysis. J Family Med Prim Care. 2022 Mar;11(3):927–940. PMID: 35495849
- Rosenstock J, Ferrannini E. Euglycemic Diabetic Ketoacidosis: A Predictable, Detectable, and Preventable Safety Concern With SGLT2 Inhibitors. Diabetes Care. 2015 Sep;38(9):1638–42. PMID: 26294774
- Peters AL, Buschur EO, Buse JB, Cohan P, Diner JC, Hirsch IB. Euglycemic Diabetic Ketoacidosis: A Potential Complication of Treatment With Sodium-Glucose Cotransporter 2 Inhibition. Diabetes Care. 2015 Sep;38(9):1687–93. PMID: 26078479
- Colacci M, Fralick J, Odutayo A, Fralick M. Sodium-Glucose Cotransporter-2 Inhibitors and Risk of Diabetic Ketoacidosis Among Adults With Type 2 Diabetes: A Systematic Review and Meta-Analysis. Can J Diabetes. 2022 Feb;46(1):10–15.e2. PMID: 34116926
- Ata N, Sahoo S, Huang S, et al. SGLT-2 inhibitors associated euglycemic and hyperglycemic DKA in a multicentric cohort. Sci Rep. 2021;11:11579. DOI: 10.1038/s41598-021-89752-w
Educational and Clinical Resources
- Euglycemic Diabetic Ketoacidosis. In: StatPearls [Internet]. Treasure Island (FL): StatPearls Publishing; 2024. NBK554570
- Yang S, Liu Y, Zhang S, et al. Risk of diabetic ketoacidosis of SGLT2 inhibitors in patients with type 2 diabetes: a systematic review and network meta-analysis of randomized controlled trials. Front Pharmacol. 2023;14:1145587. PubMed source
- Umapathysivam MM, Gunton J, Stranks SN, Jesudason D. Euglycemic Ketoacidosis in Two Patients Without Diabetes After Introduction of SGLT2 Inhibitor for Heart Failure. Diabetes Care. 2024 Jan 2;47(1):140–143. PMID: 37988720
Clinical Guidelines
- Danne T, Garg S, Peters AL, et al. International Consensus on Risk Management of Diabetic Ketoacidosis in Patients With Type 1 Diabetes Treated With SGLT Inhibitors. Diabetes Care. 2019 Jun;42(6):1147–1154. PMID: 30728224
- Goldenberg RM, Berard LD, Cheng AYY, et al. SGLT2 Inhibitor-associated Diabetic Ketoacidosis: Clinical Review and Recommendations for Prevention and Diagnosis. Clin Ther. 2016 Dec;38(12):2654–2664.e1. PMID: 28003053
© 2025 Andrew Bland, MD, FACP, FAAP — Urine Nephrology Now