Visual summary
Read urine osmolality as the kidney's response to water
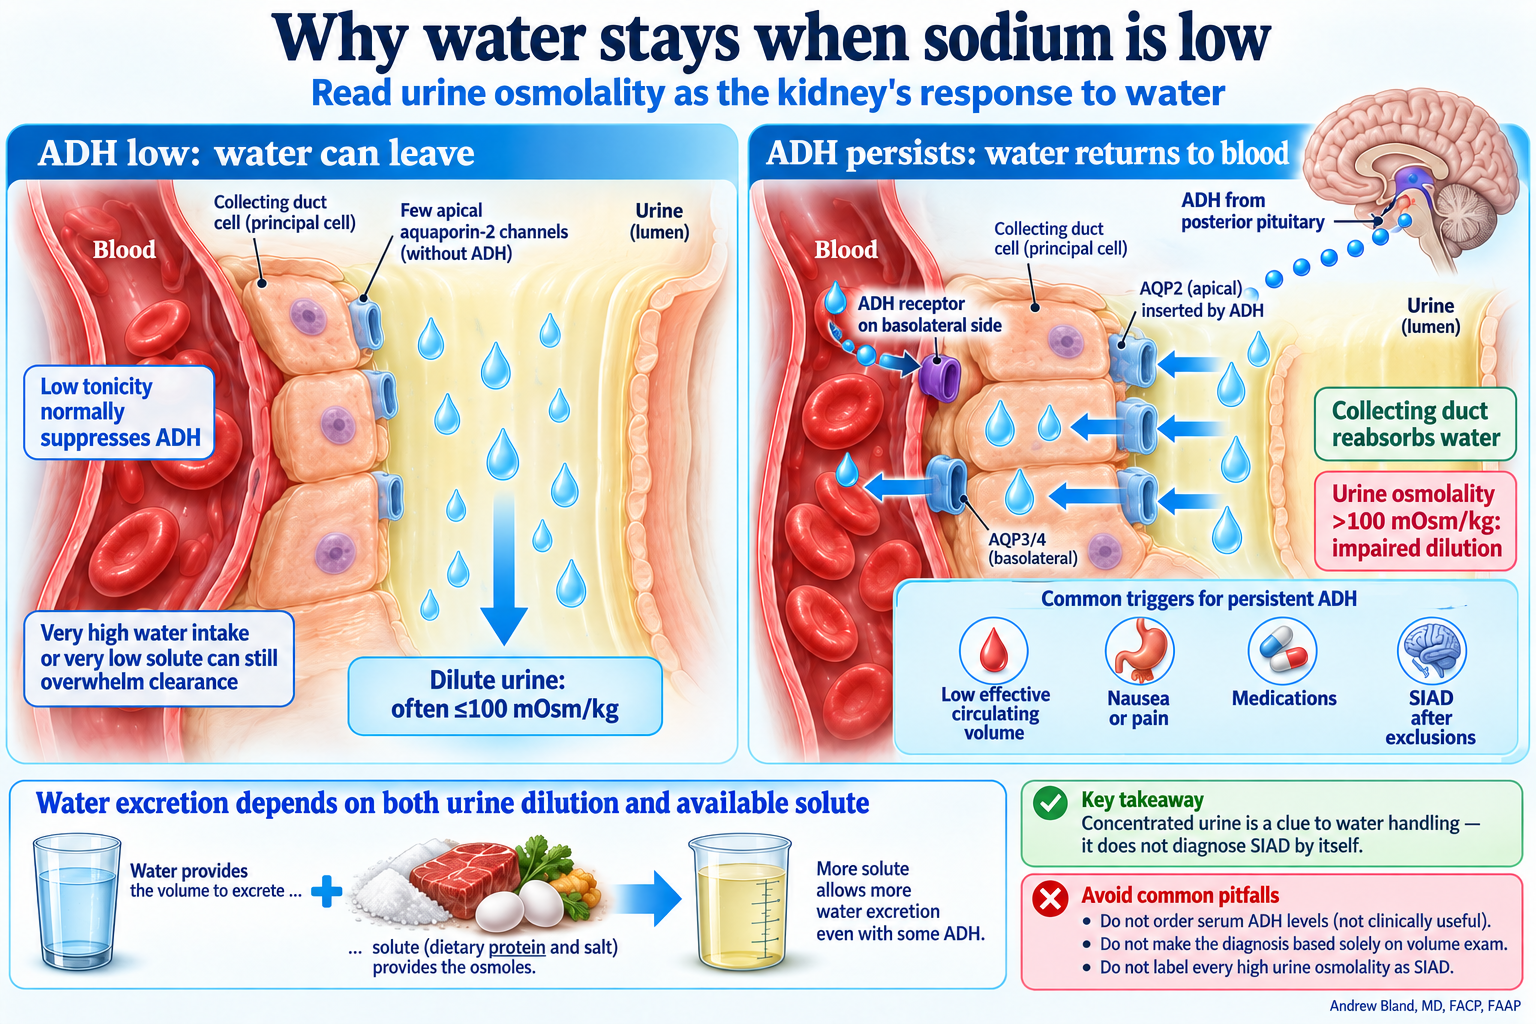
Read urine osmolality as the kidney's response to water
Text version
ADH low: water can leave
Low plasma tonicity normally suppresses ADH. With intact diluting capacity, urine can become very dilute, often at or below 100 mOsm/kg. Water remains in the tubular lumen rather than being actively secreted into it. Very high intake or very little dietary solute can still overwhelm the available water clearance.
Persistent ADH: water returns to blood
ADH signals a basolateral V2 receptor and promotes apical aquaporin-2 insertion in collecting-duct principal cells. Water then moves from urine through the cell and into blood. Low effective circulating volume, nausea, pain and medications are common triggers. Thiazides or intrinsic kidney disease can also impair dilution.
Use the whole case
Case 2 pairs hypotonic blood with concentrated urine in a patient taking a thiazide who is volume depleted and eating poorly. This is a water-handling problem with several contributors. A concentrated urine, even with a high urine sodium, does not independently establish SIAD.
What changes when volume restoration removes the ADH stimulus?
Collecting-duct water permeability falls. If renal dilution recovers, a large dilute urine flow can appear and raise serum sodium much faster than expected. Follow both urine output and sodium.
Cases and related lectures
The linked case and lecture content provide the teaching sequence and patient data.