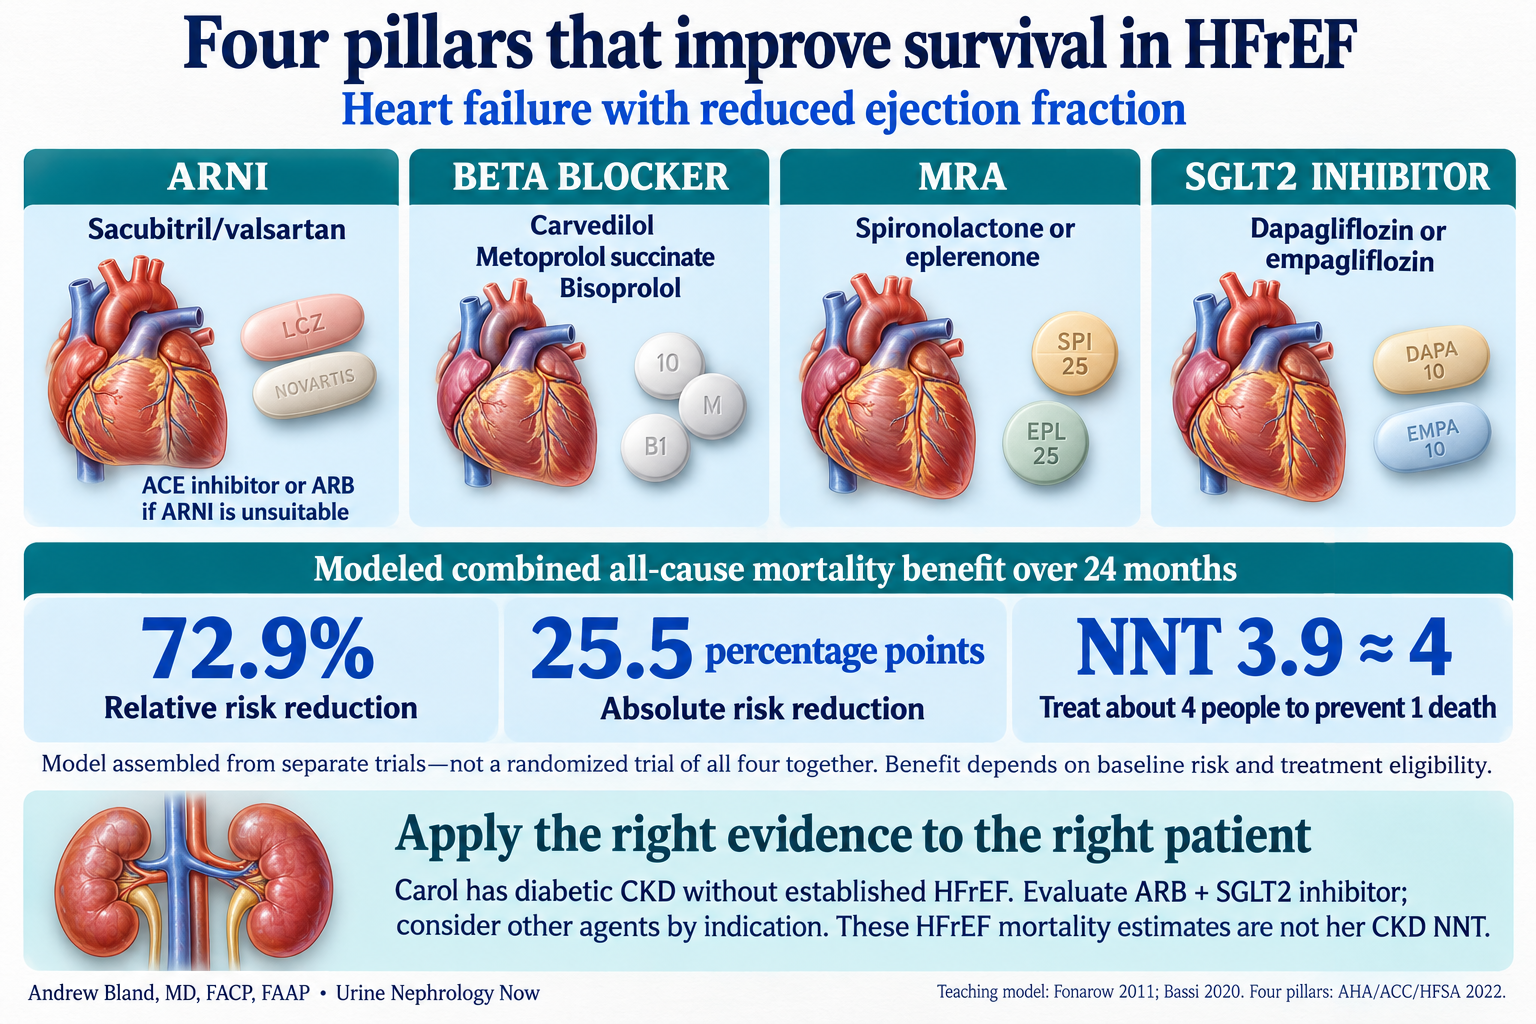
Modeled combined all-cause mortality benefit in HFrEF over 24 months: RRR 72.9%, ARR 25.5 percentage points, NNT 3.9 (about 4). These estimates are not a CKD-specific NNT.
Teaching text and evidence
Four complementary classes
For eligible HFrEF, use sacubitril/valsartan (ARNI; ACE inhibitor or ARB if ARNI is unsuitable), an evidence-based beta blocker (carvedilol, metoprolol succinate or bisoprolol), spironolactone or eplerenone (MRA), and dapagliflozin or empagliflozin (SGLT2 inhibitor). Assess each drug’s indications, contraindications and tolerability.
What the numbers mean
The Saving Lives and Stamping Out Disease presentation uses a cumulative model: all-cause mortality RRR 72.9%, ARR 25.5 percentage points and NNT 3.9, approximately 4, over 24 months. NNT is approximately 1/0.255. These estimates combine effects from separate trials and depend on baseline risk and model assumptions; they are not an observed randomized comparison of the entire four-drug package.
Apply this to Carol
Carol has type 2 diabetes and albuminuric CKD without established HFrEF. Evaluate ARB plus SGLT2 inhibitor therapy and consider additional agents by their CKD or cardiovascular indications. Do not assign the HFrEF mortality NNT to her. Finerenone has a distinct diabetic CKD evidence base and is not the steroidal MRA used in this HFrEF model.