Visual summary
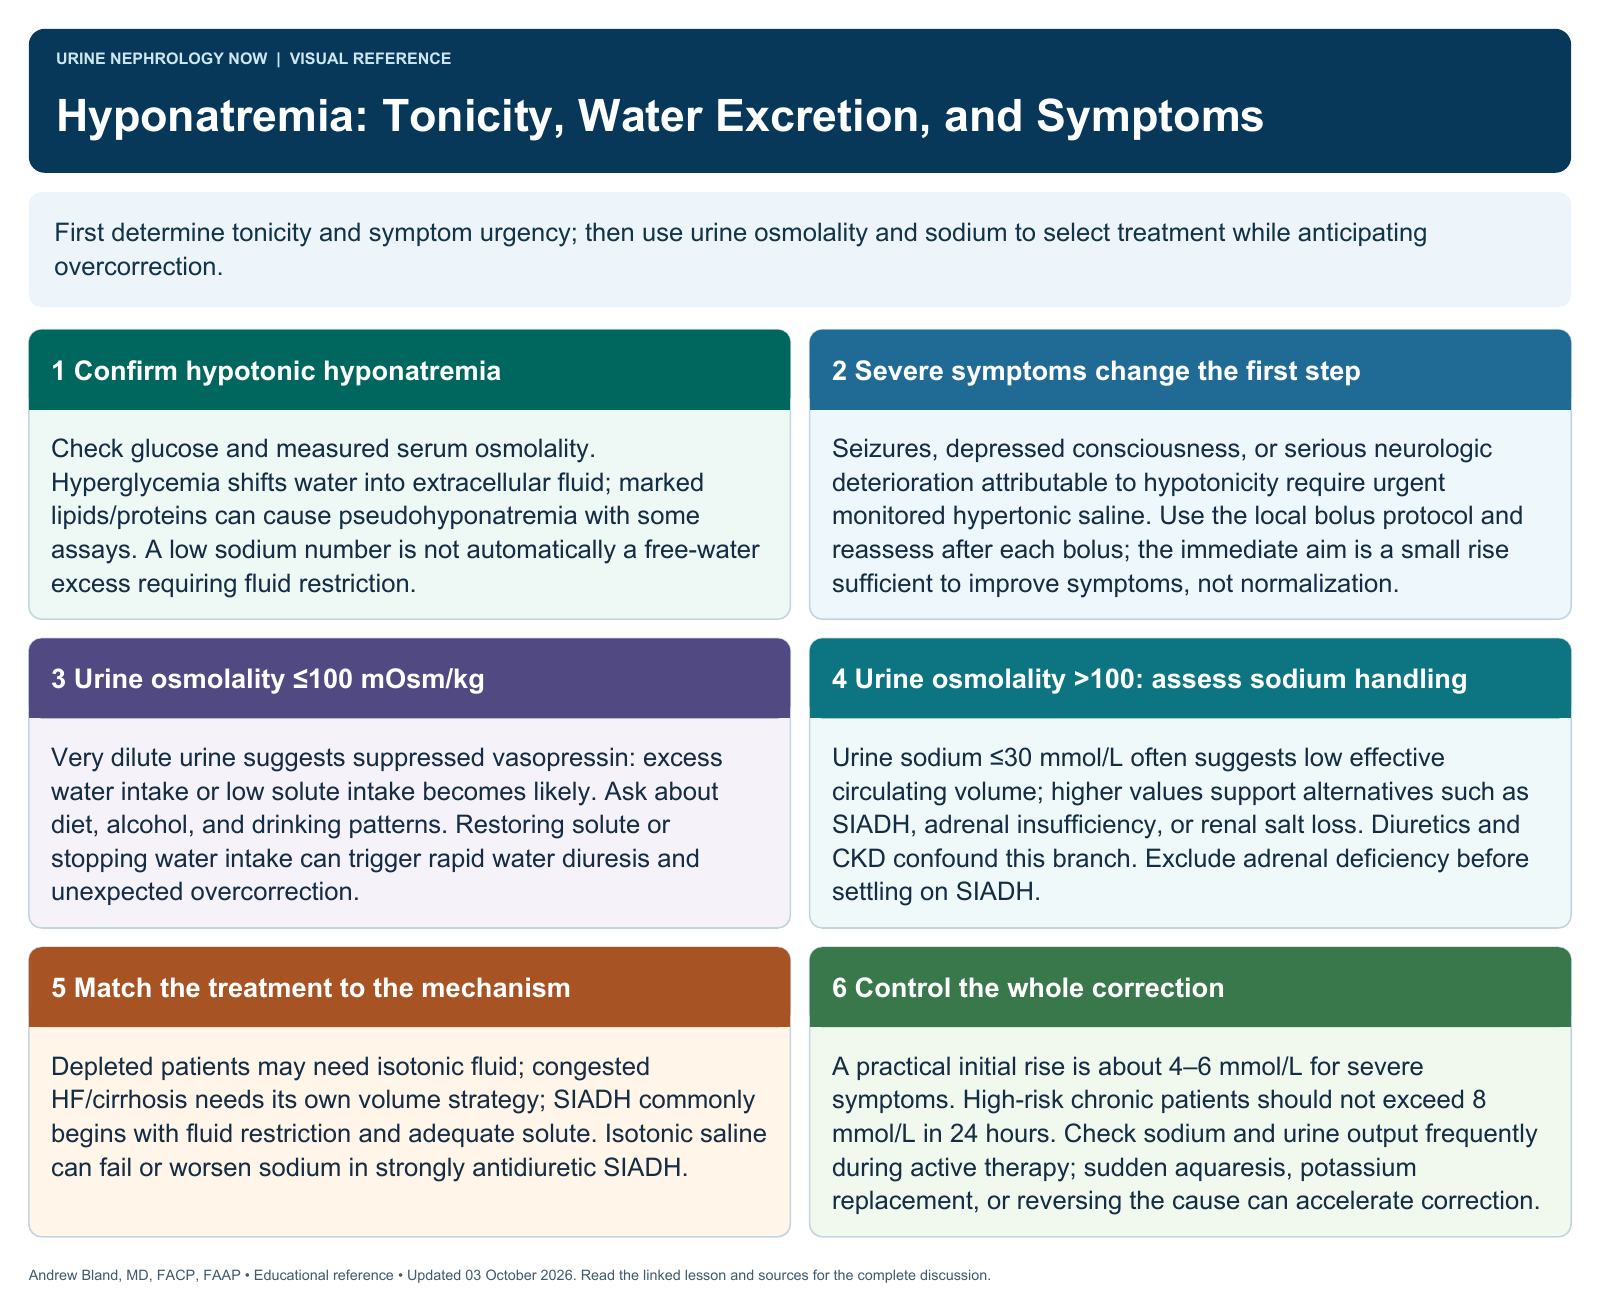
First determine tonicity and symptom urgency; then use urine osmolality and sodium to select treatment while anticipating overcorrection.
Text version
Confirm hypotonic hyponatremia
Check glucose and measured serum osmolality. Hyperglycemia shifts water into extracellular fluid; marked lipids/proteins can cause pseudohyponatremia with some assays. A low sodium number is not automatically a free-water excess requiring fluid restriction.
Severe symptoms change the first step
Seizures, depressed consciousness, or serious neurologic deterioration attributable to hypotonicity require urgent monitored hypertonic saline. Use the local bolus protocol and reassess after each bolus; the immediate aim is a small rise sufficient to improve symptoms, not normalization.
Urine osmolality ≤100 mOsm/kg
Very dilute urine suggests suppressed vasopressin: excess water intake or low solute intake becomes likely. Ask about diet, alcohol, and drinking patterns. Restoring solute or stopping water intake can trigger rapid water diuresis and unexpected overcorrection.
Urine osmolality >100: assess sodium handling
Urine sodium ≤30 mmol/L often suggests low effective circulating volume; higher values support alternatives such as SIADH, adrenal insufficiency, or renal salt loss. Diuretics and CKD confound this branch. Exclude adrenal deficiency before settling on SIADH.
Match the treatment to the mechanism
Depleted patients may need isotonic fluid; congested HF/cirrhosis needs its own volume strategy; SIADH commonly begins with fluid restriction and adequate solute. Isotonic saline can fail or worsen sodium in strongly antidiuretic SIADH.
Control the whole correction
A practical initial rise is about 4–6 mmol/L for severe symptoms. High-risk chronic patients should not exceed 8 mmol/L in 24 hours. Check sodium and urine output frequently during active therapy; sudden aquaresis, potassium replacement, or reversing the cause can accelerate correction.