Visual summary
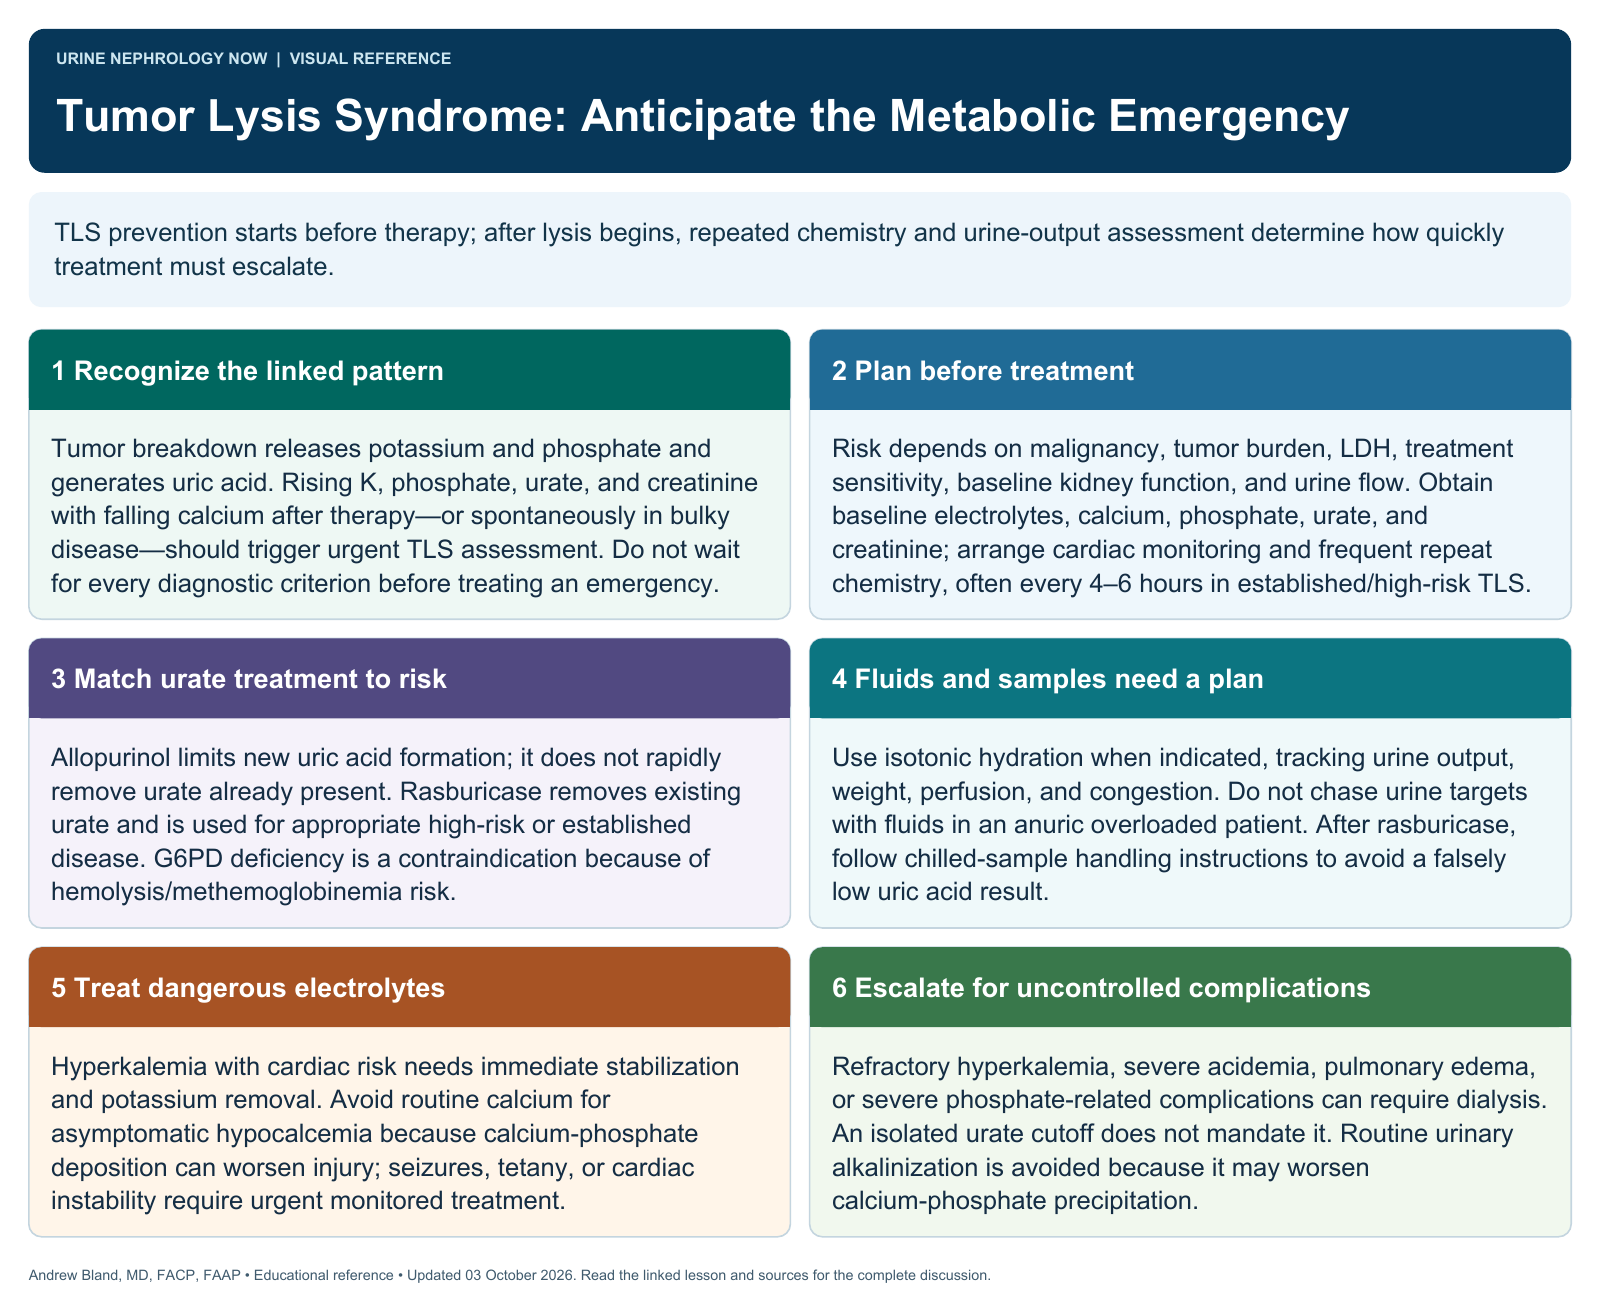
TLS care starts before treatment: anticipate risk, monitor closely, and act rapidly when dangerous electrolyte abnormalities emerge.
Text version
Rapid cell breakdown
Tumor cell lysis releases potassium, phosphate, and nucleic acid metabolites. Hyperkalemia threatens cardiac conduction; phosphate and uric acid disturbances contribute to kidney injury. TLS can follow treatment or occur spontaneously.
Recognize the cluster
Consider TLS with high tumor burden, susceptible malignancy, recent therapy, falling urine output, AKI, rising potassium and phosphate, and calcium changes. Symptoms may include weakness, arrhythmia, confusion, or seizures.
Assess risk before treatment
Coordinate oncology and kidney teams to identify risk, establish baseline laboratory values, and plan monitoring. Follow electrolytes, uric acid, creatinine, fluid balance, and ECG findings according to clinical severity.
Prevent and treat
Individualize hydration to perfusion and congestion. Urate-lowering therapy depends on risk and established disease. Rasburicase requires G6PD safety assessment; laboratory handling affects the accuracy of post-treatment uric acid measurements.
Applied case: sudden deterioration
Case 12 integrates malignant cell breakdown, kidney dysfunction, and emergency electrolyte management. Prioritize life-threatening hyperkalemia, assess symptomatic hypocalcemia, and escalate to kidney replacement therapy when medical treatment cannot control complications.
Avoid rigid shortcuts
Do not give routine urinary alkalinization or asymptomatic calcium replacement without considering precipitation risk. Conversely, symptomatic hypocalcemia or life-threatening cardiac instability needs urgent treatment. Dialysis decisions follow the full clinical picture.
Continue learning
This graphic summarizes a topic. The full educational pages provide the broader discussion and references.