Day 2 · CKD and cardiorenal disease
Look for hyperkalemic cardiac toxicity, hypoxemic pulmonary edema and uremic complications. A stable CKD stage or an isolated office BP value calls for context and follow-up, not reflex emergency treatment.
A recurring safety checkpoint for Days 2–5, classroom cases and self-study.
Andrew Bland, MD, FACP, FAAP · October 21, 2026
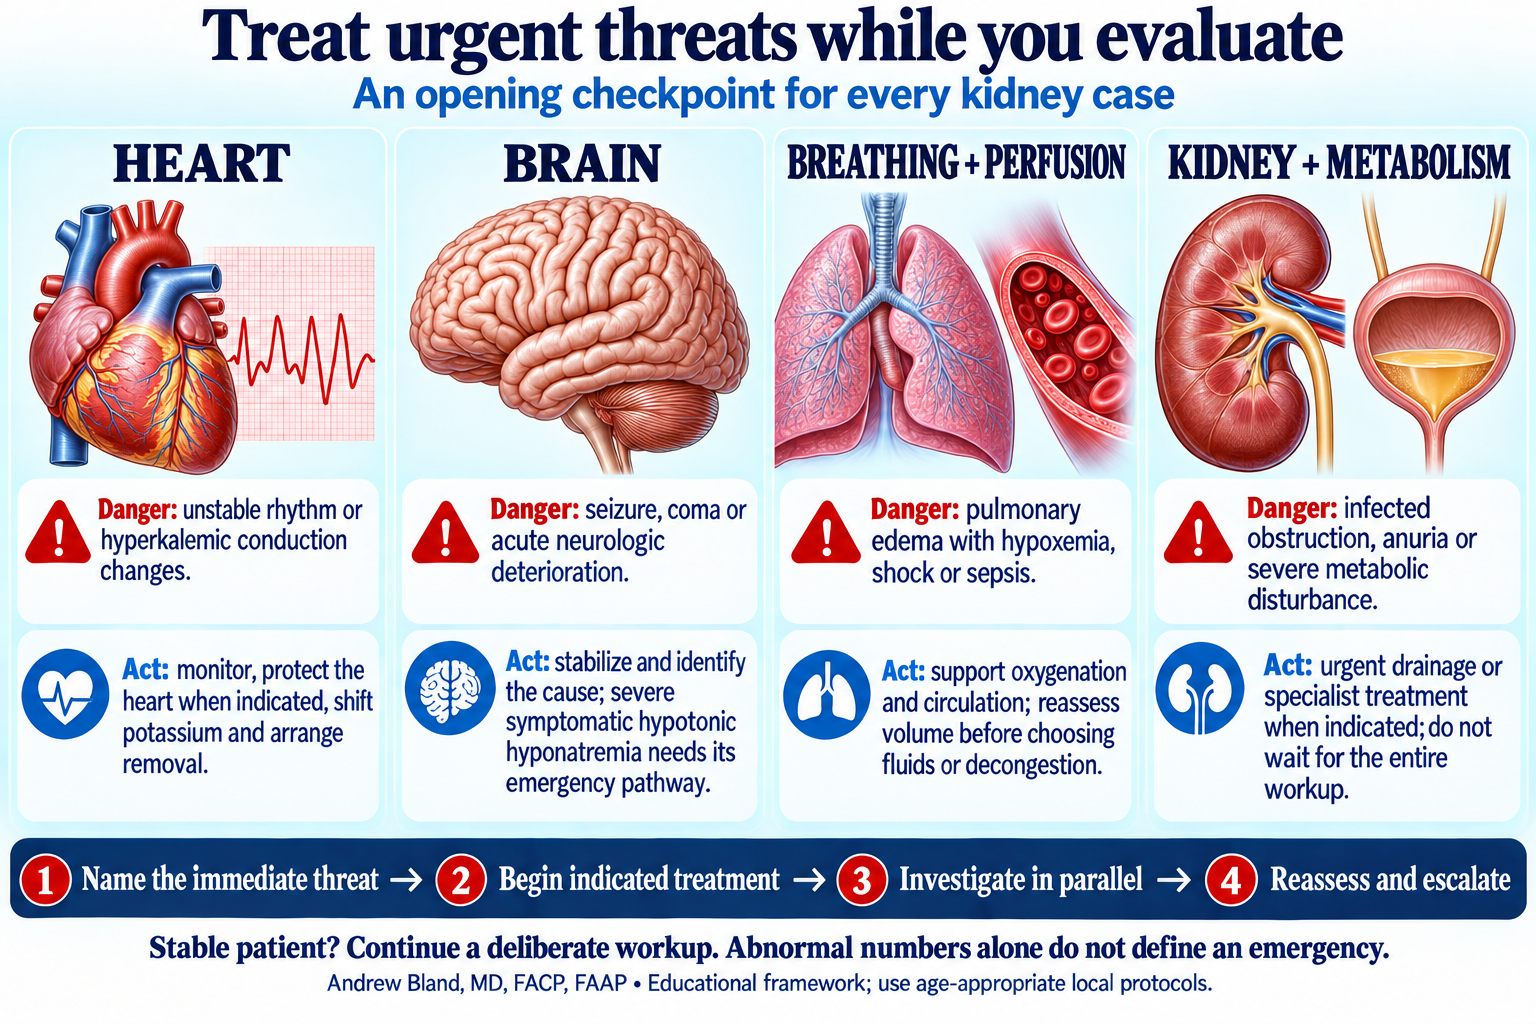
Name the threat, begin indicated treatment, investigate in parallel, then reassess.
Identify whether the patient is unstable, needs prompt escalation, or can proceed through a deliberate workup. An abnormal creatinine, blood pressure or urinalysis alone does not establish an emergency. Revisit this decision when new findings arrive.
Look for dangerous arrhythmia or hyperkalemic conduction changes, seizures, coma or acute neurologic deterioration. Use the relevant emergency pathway while clarifying the cause; not every neurologic symptom in a patient with low sodium is caused by hyponatremia.
Hypoxemic pulmonary edema, shock and sepsis change the pace of care. Support oxygenation and circulation, assess volume and reassess the response. Edema does not automatically mean intravascular volume is adequate; an elevated creatinine does not automatically call for IV fluid.
Infected obstruction needs urgent drainage and antibiotics. Anuria or a severe metabolic disturbance requires urgent evaluation. Dialysis decisions depend on the clinical problem and response to treatment, not a creatinine threshold alone.
This is a recognition framework, not a dosing protocol. Pediatric cases require pediatric blood-pressure interpretation, age-appropriate treatment and specialist escalation. Stable patients still need a clear investigation and follow-up plan.
Look for hyperkalemic cardiac toxicity, hypoxemic pulmonary edema and uremic complications. A stable CKD stage or an isolated office BP value calls for context and follow-up, not reflex emergency treatment.
Look for sepsis, rapidly progressive kidney dysfunction, pulmonary–renal features, dangerous hypertension and nephrotic complications. Distinguish contaminated urine or asymptomatic bacteriuria from a clinical infection.
Look for severe electrolyte disturbance, shock, rhabdomyolysis, tumor lysis and an infected obstructed kidney. Treat the threat while deciding whether AKI is prerenal, intrinsic, postrenal or mixed.
Look for transplant-related deterioration, hypertensive emergency, symptomatic severe hypercalcemia and other acute threats. Reconnect electrolytes, kidney reserve, urine protein and structural disease before choosing a treatment.
Day 1: heart, brain and ketoacidosis pathways · Day 5: The Calcium Connection · AKI lecture · Hypercalcemia lecture and chart