🌟 Featured Module: Systemic Lupus Erythematosus & Lupus Nephritis
Comprehensive guide featuring the latest treatment advances including voclosporin (Lupkynis), emerging biologics, and evidence-based protocols for young women
📊 2019 EULAR/ACR Criteria Calculator
🔬 ISN/RPS Classification
🎆 Voclosporin 2021 FDA Approved
👩 Young Women Focus
⚠️ Emergency Recognition
RPGN is a nephrology emergency! Rapidly worsening kidney function with suspected glomerular inflammation needs immediate nephrology assessment. Hemoptysis or hypoxemia raises concern for a pulmonary–renal emergency. Do not wait for a 50% fall in GFR.
📚 Chapter Overview
Glomerular diseases represent a complex group of disorders affecting the kidney's filtering units. This comprehensive chapter covers both nephritic and nephrotic syndromes, their pathophysiology, diagnostic approaches, and evidence-based treatments essential for PA practice.
Learning Objectives
- Differentiate nephritic from nephrotic syndromes clinically
- Interpret complement patterns and serological testing
- Recognize and manage rapidly progressive glomerulonephritis
- Understand modern treatment approaches and prognosis
- Identify secondary causes of glomerular disease
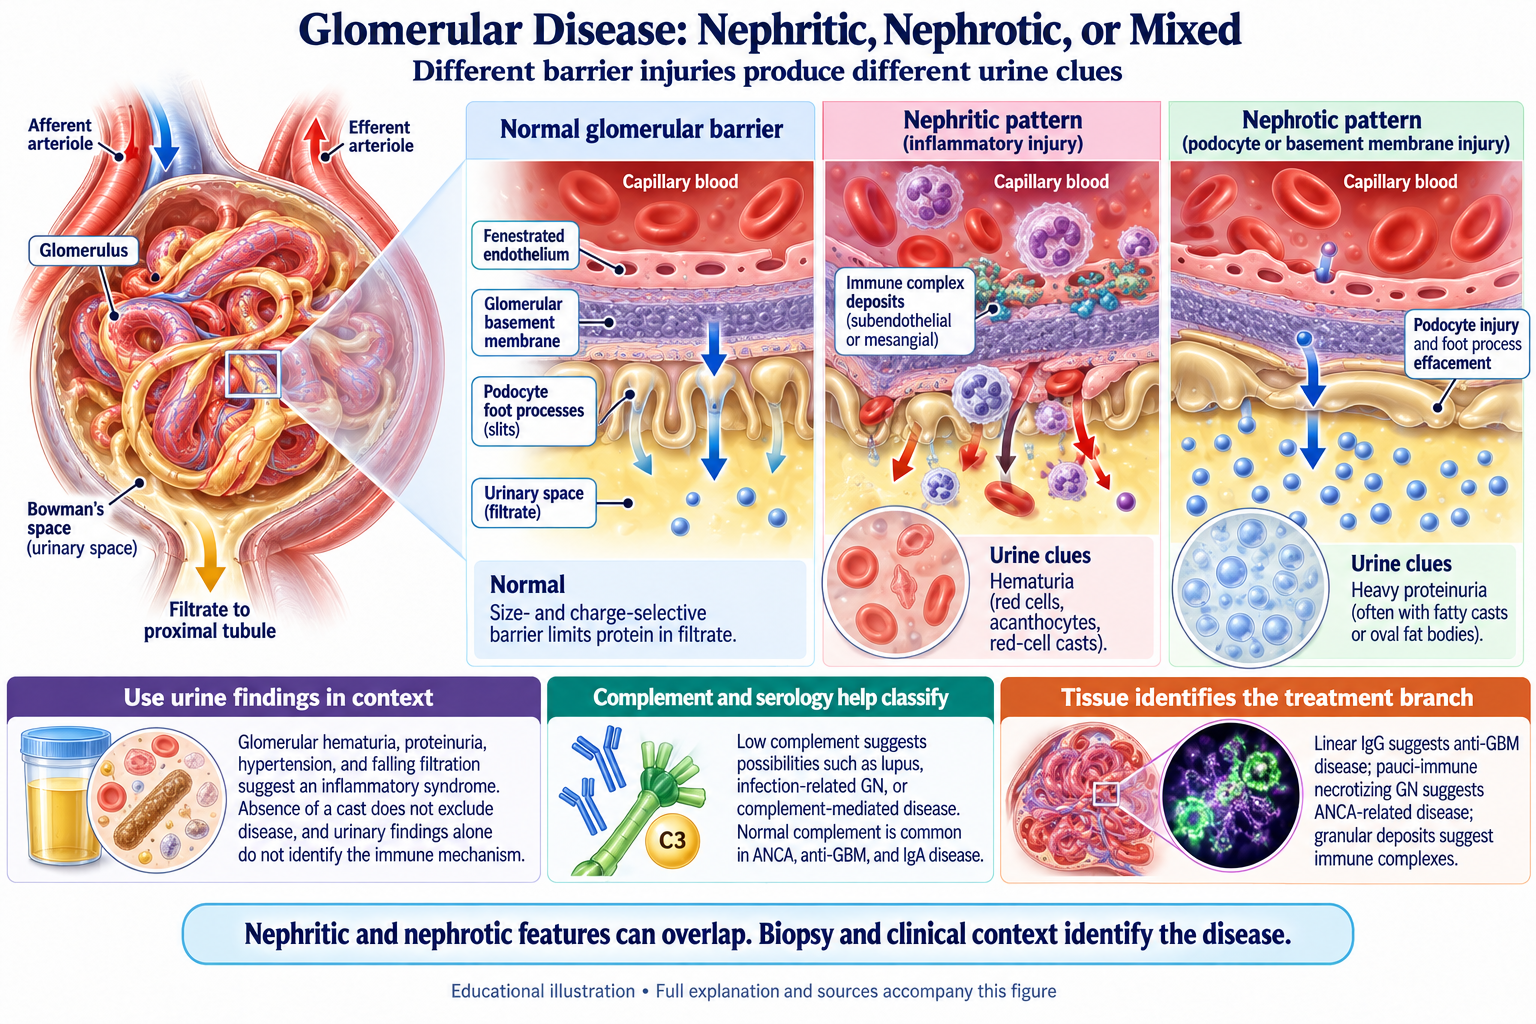
🧬 Serological Evaluation of Glomerular Disease
📊 Complement System Evaluation
Measuring C3 and C4 simultaneously helps narrow the differential diagnosis. These are typical, nonexclusive patterns: normal levels do not exclude active GN, and low levels do not identify its cause.
Complement Patterns and Associated Diseases
| Complement Pattern |
Pathway |
Renal-Limited Diseases |
Systemic Diseases |
% of Cases |
| Low C3 & C4 |
Classical Pathway Activation |
• Idiopathic MPGN Type I
• Dense deposit disease (rare)
|
• SLE nephritis
• Cryoglobulinemia
• Subacute bacterial endocarditis
• Shunt nephritis
• Hepatitis C-associated GN
|
~30% |
| Low C3, Normal C4 |
Alternative Pathway Activation |
• Post-infectious GN
• C3 glomerulopathy
• Dense deposit disease
|
• Atypical HUS
• Partial lipodystrophy
|
~25% |
| Normal C3 & C4 |
No detectable serum depletion; complement activation may still occur |
• IgA nephropathy
• Thin basement membrane
• Renal-limited vasculitis
• Anti-GBM nephritis
|
• ANCA-associated vasculitis
• Goodpasture syndrome
• Henoch-Schönlein purpura
• Alport syndrome
• Polyarteritis nodosa
|
~45% |
🎯 ANCA Testing Clinical Correlation
High Positive Predictive Value
C-ANCA with sinusitis + pulmonary infiltrates + active urinary sediment = 98% PPV for GPA
However, C-ANCA with sinusitis alone has only 7-16% PPV
Combined Testing Approach
Use both immunofluorescence pattern AND antigen-specific ELISA (MPO/PR3) for optimal sensitivity and specificity
Clinical Context is Key
ANCA results must always be interpreted in the clinical context. PPV >95% in patients with classic RPGN features
ANCA Patterns and Associated Diseases
P-ANCA/MPO
Microscopic Polyangiitis (MPA)
- Perinuclear staining pattern
- Directed against myeloperoxidase (MPO)
- More likely renal involvement (80%)
- Pulmonary-renal syndrome common
- Diffuse capillaritis
C-ANCA/PR3
Granulomatosis with Polyangiitis (GPA)
- Cytoplasmic staining pattern
- Directed against proteinase 3 (PR3)
- Upper respiratory tract involvement
- Pulmonary nodules
- Necrotizing granulomatous inflammation
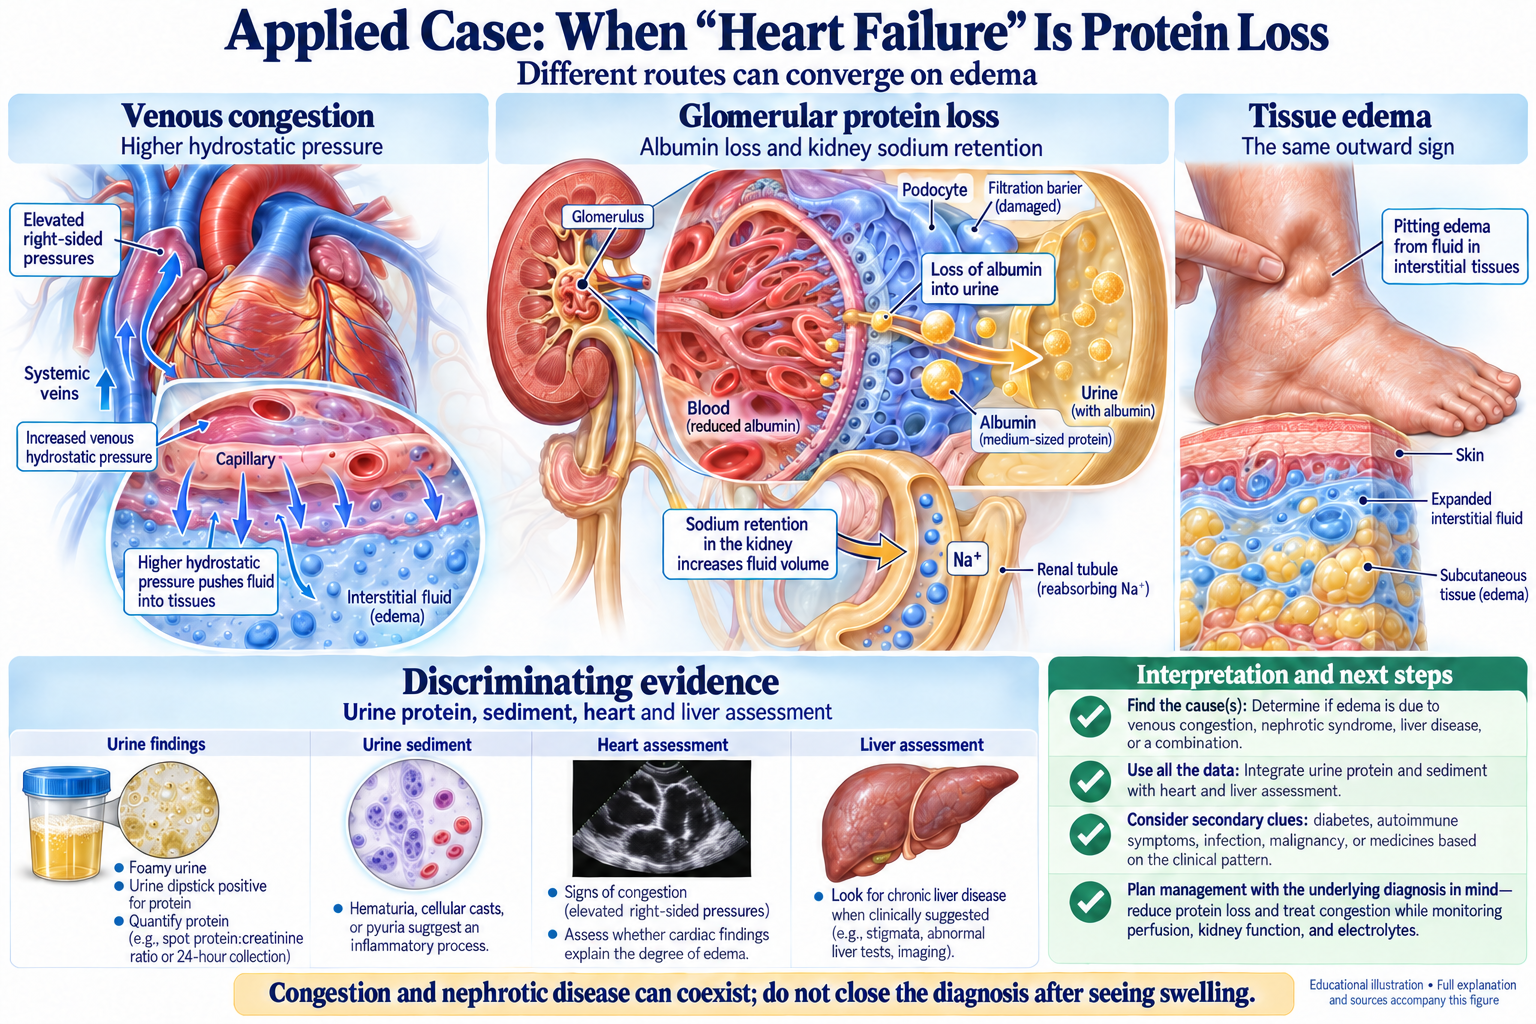
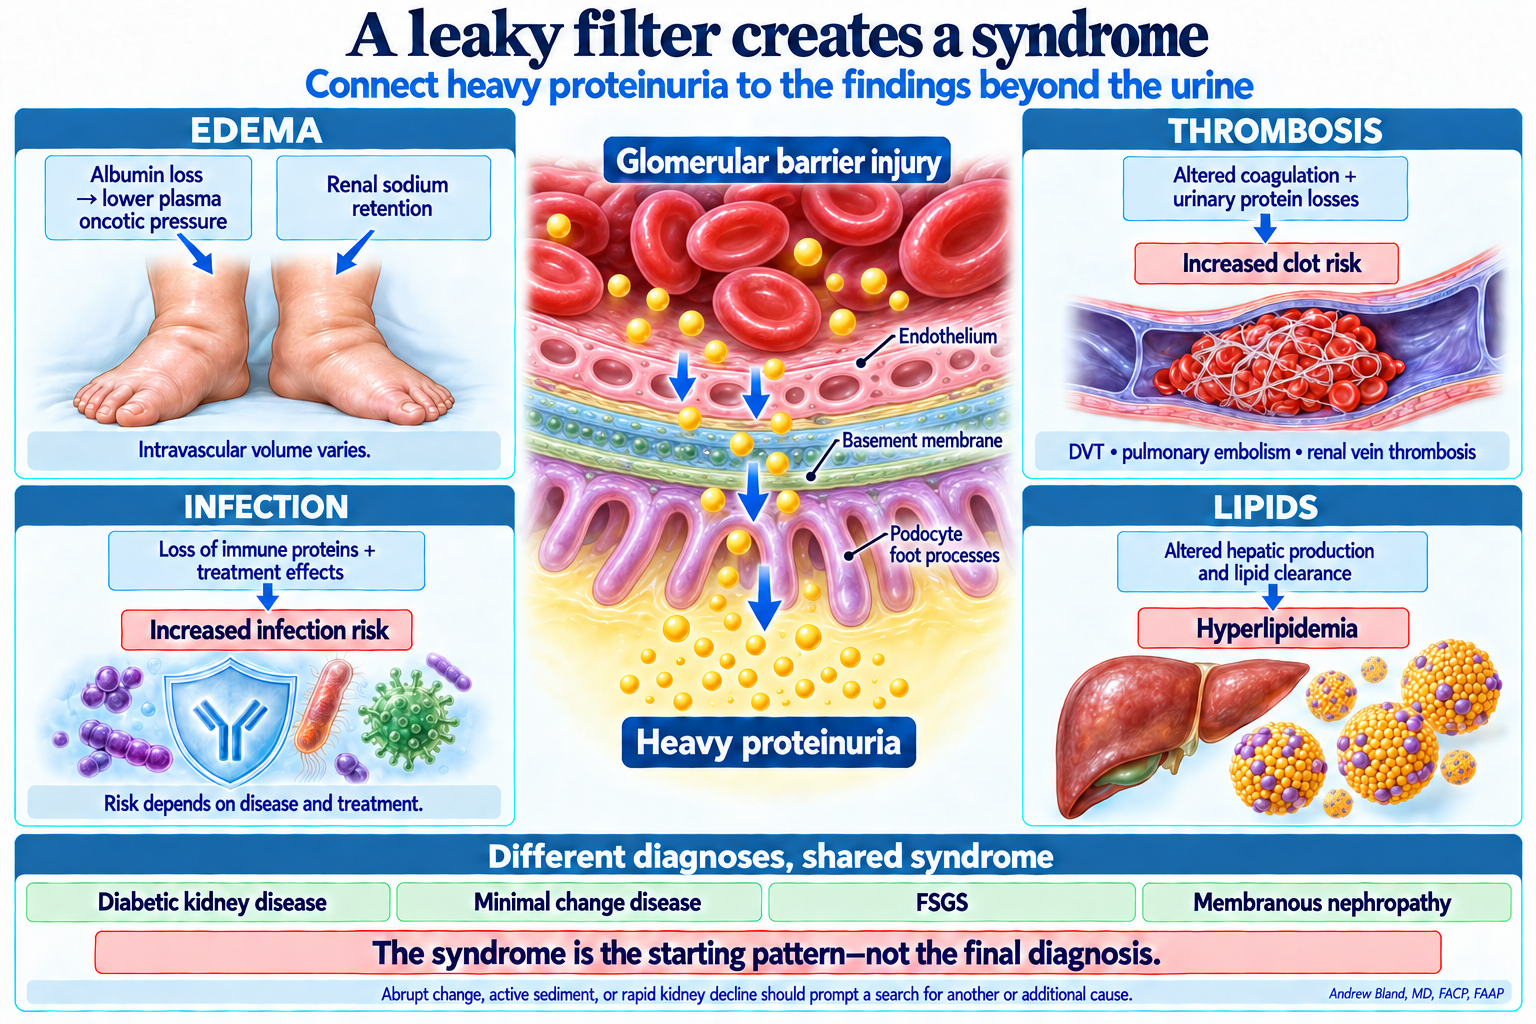
💧 Nephrotic Syndrome - Detailed Review
Pathophysiology Flow
1
Glomerular Basement Membrane Damage - Loss of charge selectivity and size selectivity
2
Massive Proteinuria - Primarily albumin loss (>3.5 g/day)
3
Hypoalbuminemia - Decreased plasma oncotic pressure
4
Fluid Retention - Edema formation and volume expansion
5
Compensatory Liver Synthesis - Increased protein and lipid production
🔬 Urine Microscopy in Nephrotic Syndrome
Oval Fat Bodies
- Tubular epithelial cells containing lipid droplets
- Highly characteristic of nephrotic syndrome
- Result from reabsorption of filtered lipoproteins
- Appear refractile under polarized light
Fatty Casts
- Casts containing lipid droplets
- Show "Maltese cross" appearance under polarized light
- Pathognomonic for significant proteinuria
- May persist even after treatment
Waxy Casts
- Broad, homogeneous casts
- May indicate chronic kidney disease
- Non-specific finding
- Can be seen with prolonged proteinuria
Minimal Hematuria
- Usually <5 RBCs per high-power field
- RBC casts are typically absent
- Contrasts with nephritic syndrome
- If significant hematuria present, consider mixed picture
Primary Causes of Nephrotic Syndrome
Minimal Change Disease (MCD)
Epidemiology
- Most common cause in children (90%)
- 20-25% of adult nephrotic syndrome
- Male predominance in children
- Peak incidence: 2-6 years old
Clinical Features
- Sudden onset of edema and proteinuria
- Normal blood pressure typically
- Normal renal function
- Minimal hematuria
Treatment
1
Initial Treatment: Prednisone 1 mg/kg/day (max 80 mg) for 4-16 weeks
2
Frequently Relapsing/Steroid-Dependent: Cyclophosphamide, Calcineurin inhibitors, Mycophenolate mofetil, or Rituximab
Focal Segmental Glomerulosclerosis (FSGS)
Epidemiology
- Most common primary cause in adults
- Higher prevalence in African Americans
- 40% of adult nephrotic syndrome
- Increasing incidence over past decades
Clinical Features
- Often presents with hypertension
- Microscopic hematuria common
- May have reduced GFR at presentation
- More resistant to treatment than MCD
Treatment
1
Initial Treatment: Prednisone 1 mg/kg/day for at least 8-16 weeks
2
Steroid-Resistant FSGS: Calcineurin inhibitors (first-line), Mycophenolate mofetil, or Sirolimus
Note: African Americans and patients with collapsing FSGS are generally unresponsive to treatment and progress to kidney failure.
Membranous Nephropathy
Epidemiology
- Most common cause in older adults
- Male predominance (2:1)
- Peak incidence: 40-60 years
- 30-40% of adult nephrotic syndrome
Non-Invasive Diagnosis
Anti-PLA2R Antibodies
- Sensitivity: 78%
- Specificity: 99%
- Positive in 70-80% of primary MN cases
- Kidney biopsy not required if positive with appropriate clinical context
- Antibody levels correlate with disease activity
Risk Stratification (KDIGO 2021)
| Risk Category |
Criteria |
Management |
| Low Risk |
Normal eGFR, Proteinuria <3.5 g/day, Serum albumin >3.0 g/dL |
Supportive care only |
| Moderate Risk |
Proteinuria 3.5-8 g/day, Stable eGFR, Albumin 2.5-3.0 g/dL |
Rituximab or calcineurin inhibitors |
| High/Very High Risk |
Proteinuria >8 g/day, Declining eGFR, High anti-PLA2R levels (>150 RU/mL) |
Immunosuppressive treatment required |
Treatment Options
1
Rituximab (First-Line, KDIGO 2021): 375 mg/m² weekly × 4 doses or 1g × 2 doses
2
Modified Ponticelli Regimen: Alternating months of steroids and cyclophosphamide
3
Calcineurin Inhibitors: Cyclosporine 3-5 mg/kg/day (trough 125-175 ng/mL)
Complications of Nephrotic Syndrome
Thromboembolism (Critical)
Pathophysiology: Loss of antithrombin III and protein S, increased fibrinogen and platelets, hemoconcentration from diuretic use
- Deep vein thrombosis
- Pulmonary embolism
- Renal vein thrombosis
Management: Consider prophylactic anticoagulation if albumin <2.0 g/dL
Infections
Pathophysiology: Loss of immunoglobulins in urine, complement factor losses, immunosuppressive medications
- Pneumococcal pneumonia
- Peritonitis (especially with ascites)
- Cellulitis
Protein Malnutrition
- Loss of binding proteins
- Muscle wasting
- Poor wound healing
- Growth retardation in children
Cardiovascular Disease
- Accelerated atherosclerosis
- Hypertension
- Coronary artery disease
- Increased mortality risk
🚨 MEDICAL EMERGENCY
Rapidly Progressive Glomerulonephritis
Risk of irreversible kidney injury without prompt treatment
Time is kidney function
Immediate nephrology consultation required
Emergency Definition & Recognition
RPGN is a clinical syndrome of rapidly worsening kidney function with suspected glomerular inflammation, often over days to weeks. Evaluate urgently while excluding other causes of AKI; do not wait for a specified percentage GFR loss or biopsy crescent burden.
Recognition Criteria
Rapid GFR Decline
Rapid creatinine rise or falling filtration with a compatible clinical presentation; a 50% decline is not a referral threshold
Nephritic Urine
Hematuria, dysmorphic RBCs, RBC casts, proteinuria
Biopsy Activity and Chronicity
Crescents and necrosis support active injury; assess viable glomeruli and chronic scarring. A fixed crescent percentage is not required before urgent evaluation
Systemic Features
Constitutional symptoms, fever, malaise, arthralgias
RPGN Classification by Immunofluorescence Pattern
Type I: Linear Pattern (Anti-GBM Disease) - 10% of RPGN
Pathophysiology: Autoantibodies against NC1 domain of α3 chain of type IV collagen in glomerular and alveolar basement membranes
Clinical Presentations
- Anti-GBM nephritis: Kidney involvement only
- Goodpasture syndrome: Kidney plus lung involvement (pulmonary hemorrhage)
Emergency Treatment
1
Plasmapheresis: Daily exchanges for 14 days or until anti-GBM antibodies undetectable. Start immediately, do not wait for biopsy results
2
IV Methylprednisolone: 1g daily for 3 days, then oral prednisone 1 mg/kg/day
3
Cyclophosphamide: 2 mg/kg/day oral or IV monthly pulses
Type II: Granular Pattern (Immune Complex Disease) - 40% of RPGN
Associated Conditions
Systemic Lupus Erythematosus
- Most common cause in this category
- Class IV lupus nephritis
- Requires aggressive immunosuppression
IgA Nephropathy
- Crescents alone do not define rapidly progressive IgAN
- Rapid functional decline requires urgent biopsy and specialist selection of treatment
- Monitor for progression
Post-Infectious GN
- Usually self-limiting
- Prioritize infection treatment and kidney supportive care; routine immunosuppression is generally inadvisable
- Supportive care in most cases
Other
- Cryoglobulinemia
- Endocarditis
- MPGN
Type III: Pauci-Immune (ANCA-Associated) - 50% of RPGN
ANCA Patterns and Associated Vasculitides
P-ANCA/MPO - Microscopic Polyangiitis (MPA)
- More likely renal involvement (80%)
- Pulmonary-renal syndrome
- Diffuse capillaritis
C-ANCA/PR3 - Granulomatosis with Polyangiitis (GPA)
- Upper respiratory tract involvement
- Pulmonary nodules
- Necrotizing granulomatous inflammation
Emergency Treatment Protocol
1
Corticosteroids: IV methylprednisolone 0.5-1 g/day for 3 days, followed by oral prednisone 1 mg/kg for 1 month
2
Induction Immunosuppression: Cyclophosphamide (IV 15 mg/kg or oral 1.5-2 mg/kg daily) OR Rituximab (375 mg/m² weekly for 4 doses)
3
Plasmapheresis Indications: Serum creatinine >4 mg/dL, dialysis dependence, pulmonary hemorrhage, concomitant anti-GBM antibodies
4
Avacopan — historical evidence update: The pivotal ADVOCATE report (
PMID 33596356; RETRACTED) was retracted in 2026 (
retraction notice). Its efficacy claims should not guide treatment. FDA proposed withdrawal on April 27, 2026; this proposal is not a completed withdrawal. Review current status and alternatives with the treating specialist (
FDA notice).
Maintenance Therapy
- Azathioprine: 2 mg/kg/day
- Mycophenolate mofetil: 1g twice daily
- Rituximab: 500mg every 6 months
- Duration: Minimum 18-24 months
Emergency Action Plan for PA Students
1
Recognition: Rapidly worsening kidney function with active sediment or systemic features needs immediate evaluation; do not wait for a 50% GFR loss
2
Immediate Actions: STAT nephrology consultation, fresh urine microscopy for RBC casts, STAT labs (creatinine, CBC, ANCA, anti-GBM), assess for systemic features
3
Stabilization: Manage fluid balance and electrolytes, control blood pressure, prepare for possible dialysis, consider empiric treatment if high suspicion
4
Definitive Care: Follow nephrology recommendations, monitor for treatment complications, coordinate multidisciplinary care, long-term follow-up planning
🔄 Diagnostic Algorithm for Glomerular Disease
1
Suspect and Evaluate Glomerular Disease: Hematuria + proteinuria ± hypertension ± reduced GFR; quantify protein and assess the clinical trajectory
2
Urine Microscopy: Look for RBC casts and acanthocytes as clues to glomerular bleeding, plus oval fat bodies and fatty casts for lipiduria; sediment alone does not identify the immune mechanism
3
Classify Syndrome: Nephritic (inflammatory) vs Nephrotic (proteinuric) vs Mixed
4
Complement Testing: Measure C3 and C4 simultaneously to determine pathway activation
5
Targeted Serological Testing: Based on complement pattern and clinical presentation (ANCA, anti-GBM, ANA, anti-PLA2R)
6
Assess Urgency: Rapid kidney-function decline with suspected GN or pulmonary–renal features requires immediate nephrology assessment; do not wait for 50% GFR loss
7
Arrange Renal Biopsy: Promptly when suspected RPGN or when histology will change management; review activity and chronicity, and investigate infection before immunosuppression