N13 — Nutrition at the Chair FRONT
Front · at the chair
When: every weigh-in, snacks and meal trays, diet questions, and the monthly lab review.
Do this
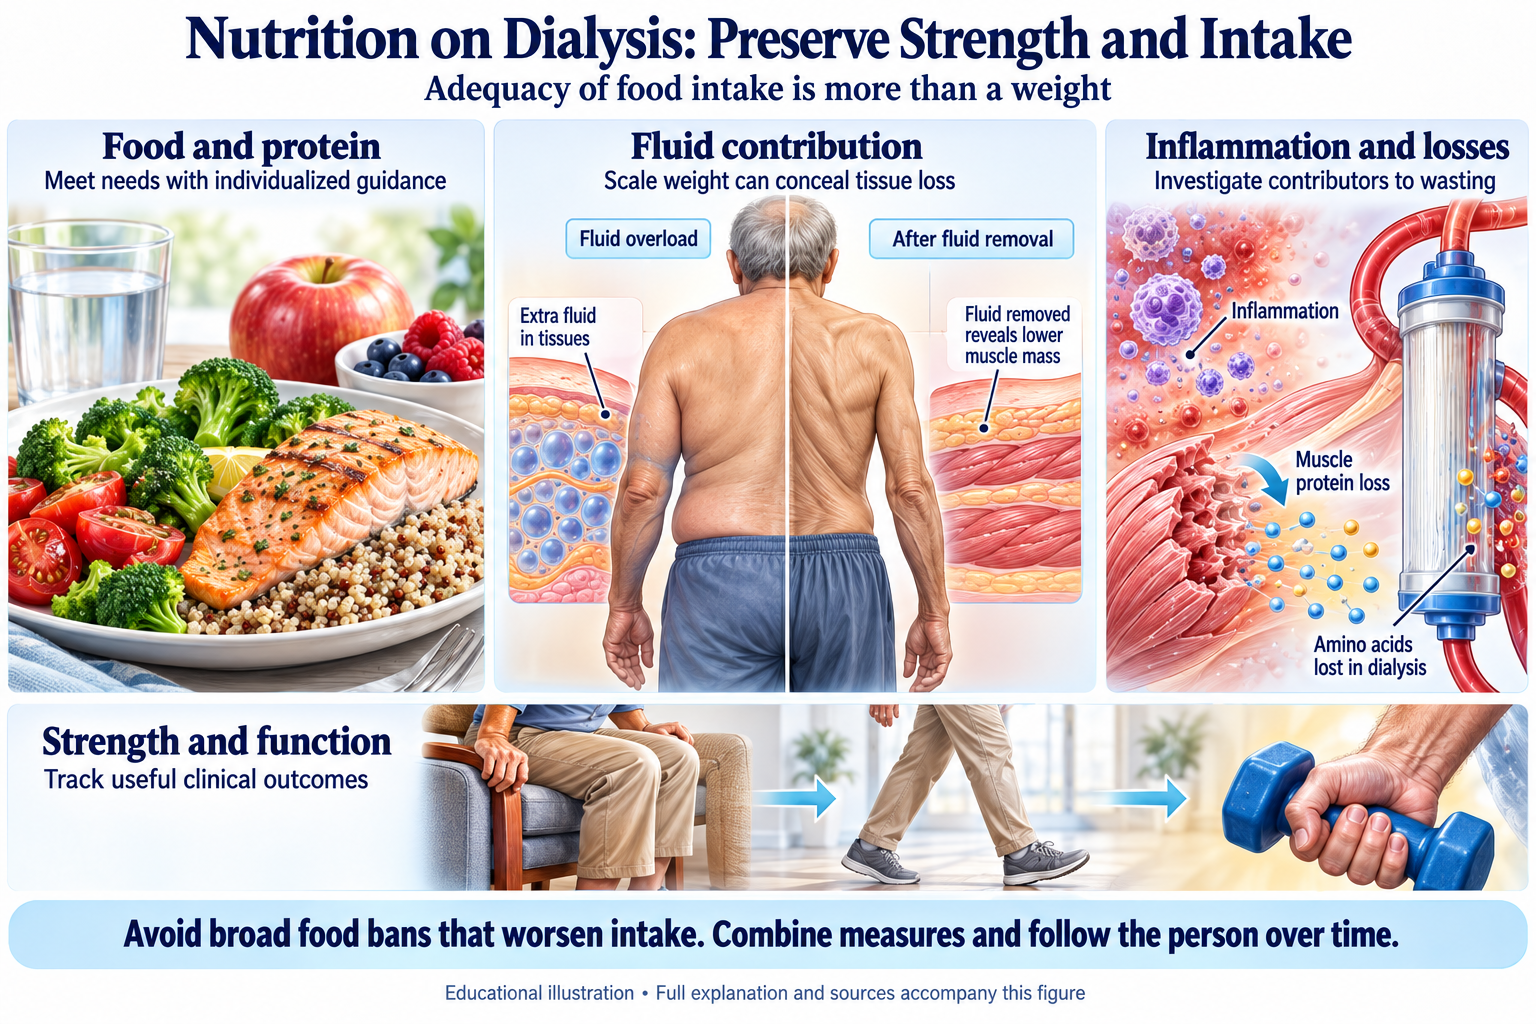
- Weigh accurately before and after every treatment. Repeatedly finishing below target may reflect tissue loss, fluid change, or a measurement/target issue. Report the trend and assess appetite, function, and volume; it is not proof of tissue loss [11].
- Ask weekly: appetite? eating on dialysis days? nausea, trouble chewing or swallowing, mouth pain? groceries? Document it for the dietitian [9].
- Eating on treatment — stable patients only: a small, protein-focused snack early in the run (timing per your unit protocol), upright and fully awake, away from lines and access [5].
- Patients whose BP drops on treatment: eat before arrival or after treatment — not on the machine [4]. See N5: Intradialytic Hypotension: Chair-Side Response.
- Reinforce the dietitian’s plan: protein at every meal; less salt to control thirst; avoid foods with “PHOS” in the ingredient list; don’t cut out fruits and vegetables without the dietitian [9].
- Fish oil (product per your unit protocol): confirm it is on the medication list and ask how many capsules a day. Dose by the EPA + DHA on the label — about 2.4 g/day is the PISCES dose [6].
Call the nephrologist (and tell the dietitian) when
- Unintentional weight loss of 5% over 3 months or 10% over 6 months, or the post-weight keeps landing below target [11].
- Albumin falls below 3.5 g/dL or drops noticeably from the patient’s usual — think infection or inflammation first, intake second [3].
- Eating poorly for more than 2 weeks, trouble swallowing, or mouth pain; or signs of infection (fever, exit-site redness, old-graft tenderness, foot wounds).
- nPCR below 0.8 g/kg/day, or phosphorus, potassium, or BUN suddenly “better” — the patient may have stopped eating [10].
- Symptomatic low BP after eating on the machine [4].
- On fish oil: black stools, needle-site bleeding that won’t stop, new palpitations or an irregular pulse, or a newly found fish or shellfish allergy [12].
Don’t
- Don’t treat a low albumin as only a diet problem [3].
- Don’t feed a patient who is dropping BP, drowsy, or struggling to swallow [4,5].
- Don’t tell patients to eat less protein to control phosphorus — binders and additive avoidance do that, and low protein intake is associated with death on dialysis [9,10].
- Don’t remove fruits and vegetables from the diet without the dietitian.
- Don’t count “fish oil 1,000 mg” as the dose; count EPA plus DHA [6].
- Don’t expect fish oil to raise albumin; it is for cardiovascular protection [7,8].
N13 — Nutrition at the Chair BACK
Back · why, and the evidence
Why
- Protein-energy wasting affects 28% to 54% of dialysis patients across studies [1], and malnutrition raises the risk of death about 1.5-fold on hemodialysis [2].
- Albumin tracks inflammation: blocking IL-6 raised albumin 0.21–0.28 g/dL in 12 weeks with no change in food [3].
- Eating on the machine is a trade: it caused 13 versus 2 symptomatic low-BP episodes in a small study [4], yet experts support it for patients without contraindications [5].
- In PISCES, fish oil cut serious cardiovascular events from 33.7% to 20.8% of patients over about 2 years, with less serious bleeding (4.8% vs 7.6%); survival did not change [6].
- Fish oil does not meaningfully raise albumin: 14 pooled trials showed no change (0.00 g/dL) [7], and the only trial sized for albumin found +0.1 versus 0.0 g/dL (P = 0.295) [8].
Go deeper
- Mastery page: Nutrition and Protein-Energy Wasting on Hemodialysis
- Mastery page: Inflammation and Fish Oil (PISCES) in Hemodialysis
- All dialysis nursing reference cards
References
- Carrero JJ, et al. Global prevalence of protein-energy wasting in kidney disease: a meta-analysis (ISRNM). J Ren Nutr. 2018;28:380-392. PubMed 30348259
- Rashid I, et al. Malnutrition as a potential predictor of mortality in CKD patients on dialysis: a systematic review and meta-analysis. Clin Nutr. 2024;43:1760-1769. PubMed 38852509
- Chertow GM, et al. IL-6 inhibition with clazakizumab in patients receiving maintenance dialysis: a randomized phase 2b trial. Nat Med. 2024;30:2328-2336. PubMed 38796655
- Sherman RA, et al. Postprandial blood pressure changes during hemodialysis. Am J Kidney Dis. 1988;12:37-39. PubMed 3389352
- Kistler BM, et al. Eating during hemodialysis treatment: a consensus statement from the ISRNM. J Ren Nutr. 2018;28:4-12. PubMed 29249295
- Lok CE, et al. Fish-oil supplementation and cardiovascular events in patients receiving hemodialysis (PISCES). N Engl J Med. 2026;394:128-137. PubMed 41201837
- Liu R, et al. Effects of omega-3 fatty acid intake in patients undergoing dialysis: a systematic review and meta-analysis of RCTs. J Am Nutr Assoc. 2022;41:697-712. PubMed 34635026
- Daud ZA, et al. Effects of protein and omega-3 supplementation, provided during regular dialysis sessions, on nutritional and inflammatory indices in hemodialysis patients. Vasc Health Risk Manag. 2012;8:187-195. PubMed 22536073
- Ikizler TA, et al. KDOQI clinical practice guideline for nutrition in CKD: 2020 update. Am J Kidney Dis. 2020;76(3 Suppl 1):S1-S107. PubMed 32829751
- Shinaberger CS, et al. Longitudinal associations between dietary protein intake and survival in hemodialysis patients. Am J Kidney Dis. 2006;48:37-49. PubMed 16797385
- Fouque D, et al. A proposed nomenclature and diagnostic criteria for protein-energy wasting in acute and chronic kidney disease. Kidney Int. 2008;73:391-398. PubMed 18094682
- Gencer B, et al. Effect of long-term marine omega-3 fatty acids supplementation on the risk of atrial fibrillation in randomized cardiovascular outcome trials. Circulation. 2021;144:1981-1990. PubMed 34612056
Reviewed by Andrew Bland, MD, FACP, FAAP · v1.0 draft 2026-09-26. For education; the physician’s written order and the unit protocol always govern.
Visual reference
Browse the visual reference library · Download lesson Markdown